

Highlight
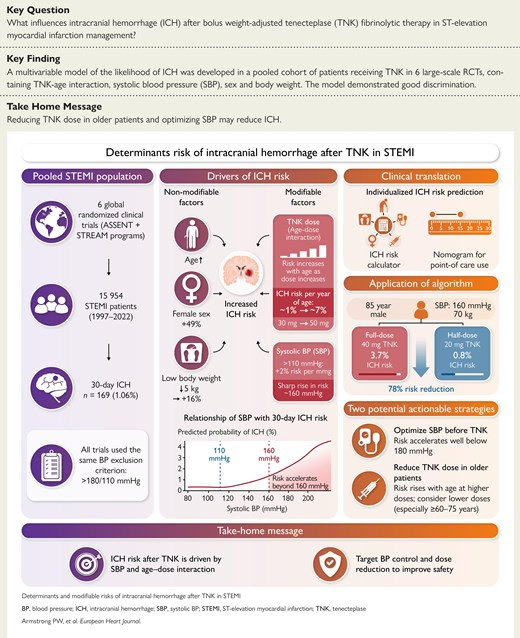
Intracranial haemorrhage (ICH) remains a serious complication of tenecteplase (TNK) fibrinolytic therapy in ST-elevation myocardial infarction (STEMI). This pooled analysis of over 15,000 patients defines key modifiable and non-modifiable risk factors for ICH, including age, systolic blood pressure (SBP), sex, body weight, and TNK dose, allowing for individualized risk prediction and dose optimization strategies.
Risk of ICH rises sharply with SBP >160 mmHg and increases exponentially with age, especially at higher TNK doses. Women and patients with lower body weight have heightened vulnerability. A clinical nomogram based on these variables demonstrates good predictive accuracy (C-index 0.718).
Study Background
Fibrinolytic therapy with tenecteplase is a cornerstone treatment for STEMI, particularly in settings without immediate access to primary percutaneous coronary intervention (PCI). However, its use is complicated by the risk of life-threatening intracranial haemorrhage, which markedly worsens prognosis. Understanding patient and treatment-related factors that heighten ICH risk is critical to improving safety and outcomes.
Previous studies identified hypertension, advanced age, female sex, and low body weight as potential risk factors, but data specific to TNK with contemporary dosing regimens and blood pressure protocols remain limited. This comprehensive analysis integrates individual patient data from six randomized controlled trials employing a consistent SBP threshold for fibrinolytic eligibility to build a robust risk prediction model.
Study Design
This pooled individual patient data analysis incorporated 15,954 STEMI patients treated with weight-adjusted TNK across six randomized clinical trials: ASSENT-2, ASSENT-3, ASSENT-3 PLUS, ASSENT-4 PCI, STREAM, and STREAM-2.
All trials enforced a uniform blood pressure exclusion criterion of SBP >180/110 mmHg before TNK administration. Patients received varying doses of TNK adjusted by weight and clinical protocol. Logistic regression modeling identified independent risk factors for ICH, and a nomogram was derived for individualized risk estimation.
The primary endpoint was incidence of intracranial haemorrhage following fibrinolytic therapy.
Key Findings
Among the 15,954 patients analyzed, 169 (approximately 1.06%) developed ICH post-TNK fibrinolysis. Key observations include:
- Systolic blood pressure: Above a threshold of 110 mmHg, incremental increases in SBP conferred a 2% relative increase in ICH risk per 1 mmHg (adjusted odds ratio [aOR] 1.02; 95% CI, 1.01–1.03; P < .0001). Notably, risk escalated sharply beyond an SBP of 160 mmHg, underscoring the need for optimal blood pressure management prior to TNK administration.
- Age and TNK dose interaction: The risk of ICH increased markedly with age and was amplified by higher TNK doses. At a dose of 30 mg TNK, risk increased by roughly 1% per year of age, whereas at 50 mg, this rise approached nearly 7% per year of increased age. This interaction highlights the necessity of dose adjustments in elderly patients.
- Sex: Female patients had a 49% higher odds of ICH (aOR 1.49; 95% CI, 1.06–2.11; P = .023) compared to males, consistent with prior observations suggesting sex-based biological or pharmacokinetic differences affecting bleeding risk.
- Body Weight: Each 5 kg decrement in body weight was associated with a 16% increase in ICH odds (aOR 1.16; 95% CI, 1.03–1.30; P = .014), emphasizing the importance of weight-based dosing and the potential vulnerability of lower-weight individuals.
The multivariable regression model, integrating age, sex, SBP, body weight, TNK dose, and the critical age-dose interaction, achieved good discrimination for predicting ICH (C index of 0.718; 95% CI, 0.68–0.76), indicating clinical utility for risk stratification.
Expert Commentary
The study by Armstrong et al. constitutes an important effort to refine risk stratification for ICH in patients receiving TNK fibrinolysis for STEMI. The large pooled dataset and consistent blood pressure eligibility criteria strengthen the validity of findings.
Clinically, the demonstration of a pronounced age-dose interaction supports current guideline trends advocating lower fibrinolytic doses in elderly patients to mitigate bleeding risks. Moreover, stringent pre-treatment blood pressure control, particularly avoiding SBP elevations beyond 160 mmHg, emerges as a modifiable factor to reduce ICH risk.
Sex-based differences, with females at higher risk, may reflect hormonal influences, vascular integrity, or pharmacodynamics of TNK that require further mechanistic elucidation.
Limitations include the secondary nature of this pooled analysis and potential heterogeneity across trial protocols not fully accounted for despite common SBP thresholds. Future prospective validation of the predictive nomogram in broader populations, including those with comorbidities and differing racial demographics, is warranted.
Conclusion
This comprehensive analysis identifies critical risk factors for intracranial haemorrhage following tenecteplase fibrinolysis in STEMI and proposes a practical clinical prediction model. The findings underscore the importance of individualized dosing—particularly dose reduction in older patients—and optimizing systolic blood pressure prior to treatment initiation.
Implementing these strategies could enhance the safety profile of TNK fibrinolysis, balance the benefits of timely reperfusion, and reduce catastrophic hemorrhagic complications. Further refinement and validation of prediction tools may ultimately inform guideline recommendations and clinical decision-making algorithms.
Funding and ClinicalTrials.gov
The study is a pooled analysis of previously conducted trials, which were sponsored by multiple academic and industry stakeholders associated with each original trial. Individual trial registrations are available on ClinicalTrials.gov under their respective titles (e.g., ASSENT trials, STREAM trials).
References
- Armstrong PW, Danays T, Westerhout CM, et al. Intracranial haemorrhage following tenecteplase fibrinolysis for acute myocardial infarction. Eur Heart J. 2026 Sep 21. PMID: 42766418.
- White HD, Chew DP. Acute myocardial infarction. Lancet. 2008;372(9638):570-84.
- Antman EM, Anbe DT, Armstrong PW, et al. ACC/AHA guidelines for the management of patients with ST-elevation myocardial infarction—executive summary. Circulation. 2004;110(5):588-636.
- Tarantini G, Fraccaro C, Agrifoglio M, et al. The evolving role of tenecteplase in STEMI: efficacy and safety considerations. Eur Heart J Suppl. 2018;20(Suppl E):E43–E48.


