

Highlights
- Distinct gut phageome dynamics precede early-onset NEC, characterized by lysogenic prophage signatures stabilizing pathobionts.
- Bacterial resistome profiles, particularly antimicrobial resistance gene patterns, robustly predict late-onset NEC risk.
- Integrated metagenomic-metatranscriptomic and machine learning approaches enable early, non-invasive NEC risk stratification.
- These findings reveal polymicrobial etiologies with clinical implications for targeted prevention and microbiome-modulating therapies.
Background
Necrotising enterocolitis (NEC) remains one of the most severe gastrointestinal emergencies in preterm infants, with a multifactorial pathogenesis involving aberrant microbial colonization, immature intestinal barriers, and dysregulated host immune responses. Despite decades of research, reliable early clinical or laboratory predictors for NEC remain elusive, hindering timely interventions. Emerging evidence implicates the gut microbiome, not only bacterial communities but also their viral constituents (particularly bacteriophages prophages), as critical determinants in NEC development. The neglect of the virome and oversimplified models focusing solely on bacterial dysbiosis have limited progress in predictive biomarker discovery and mechanistic understanding. This review synthesizes recent high-quality evidence, emphasizing the roles of gut phages (prophageomes) and bacterial resistomes in NEC pathogenesis and prediction, aiming to inform clinical risk stratification and novel therapeutic strategies.
Key Content
Evolution of Microbiome Research in NEC
Initial studies focusing on bacterial taxonomic shifts identified associations between NEC and blooms of specific taxa such as Proteobacteria, but lacked reproducibility and causality. More refined approaches incorporated functional metagenomics, revealing microbial metabolic disruptions implicated in mucosal injury. However, the role of resident gut phages, particularly temperate prophages integrated into bacterial genomes, emerged only recently as studies utilizing metagenomic sequencing uncovered complex phage-bacteria interactions influencing microbial community stability and pathogenic potential.
Role of Gut Phages in NEC: Insights from Integrated Metagenomics and Metatranscriptomics
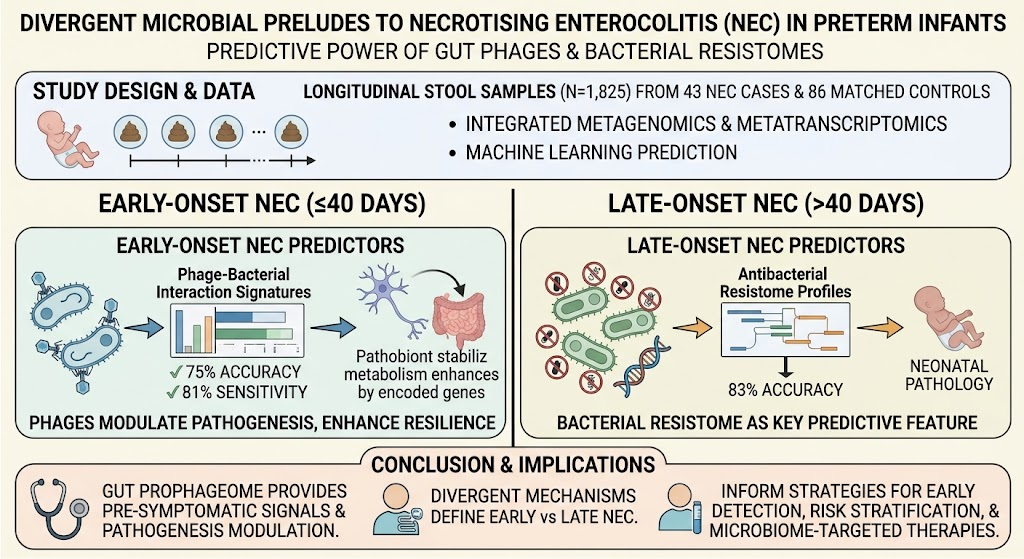
The landmark study by Zhang et al. (2026) conducted longitudinal, integrated metagenomic and metatranscriptomic analyses of 1825 stool samples from 129 preterm infants across three US NICUs, including 43 NEC cases and matched controls. They demonstrated distinct viral diversity trajectories pre-NEC onset, especially in early-onset cases (≤40 days), where signatures of phage-bacterial interactions predicted NEC with 75% accuracy and 81% sensitivity.
Metatranscriptomic data revealed a paradoxical increase of phage DNA abundance concurrent with low phage gene expression prior to NEC episodes, suggesting a lysogenic phage lifecycle predominance. This lysogeny may confer fitness advantages to pathobionts by encoding auxiliary metabolic genes that enhance resilience under antibiotic exposure and inflammatory stress. These prophage-encoded functions potentially stabilize virulent bacteria, facilitating mucosal injury. Such insights elucidate phages as active modulators, not mere bystanders, in NEC pathogenesis.
Bacterial Resistomes and Late-Onset NEC Prediction
Late-onset NEC (>40 days postnatal age) was best predicted by antibacterial resistome profiles, with machine learning models achieving 83% accuracy. This underscores the role of antibiotic resistance gene carriage and potential microbiome perturbations driven by antimicrobial exposure in selecting pathogenic bacterial communities.
This finding aligns with observational studies linking prolonged or broad-spectrum antibiotic use to NEC risk, likely mediated via selection pressure promoting expansion of resistant pathobionts. Resistome profiling thus emerges as a clinically relevant biomarker to identify infants at heightened risk and guide antibiotic stewardship policies.
Polymicrobial Aetiologies and Stratified Disease Mechanisms
The divergent microbial preludes—phage-driven early NEC versus resistome-associated late NEC—highlight polymicrobial etiologies with distinct temporal mechanistic pathways. Early disease pathogenesis involves phage-mediated modulation of bacterial communities, possibly influencing initial mucosal barrier compromise. Late disease relates more to antibiotic resistance and dysbiosis-driven inflammation.
Considering disease heterogeneity by onset timing enables refined risk stratification and tailored interventions, diverging from the earlier one-size-fits-all prevention approaches such as universal probiotic administration.
Methodological Advances and Machine Learning Integration
Zhang et al.’s approach combining longitudinal multi-omic data with robust machine learning classifiers exemplifies methodological progress that overcomes challenges of ecological complexity and temporal dynamics in NEC microbiome research. These analytic frameworks allow integration of prenatal, perinatal and postnatal exposures (antibiotics, nutrition, pharmacotherapies) with microbial ecosystem changes, enhancing predictive model performance and interpretability.
The study also highlights the potential of metatranscriptomics to distinguish phage lifecycle states, an innovative biomarker dimension previously unexplored in NEC.
Expert Commentary
NEC prediction and prevention remain high priorities in neonatology. This emerging evidence redefines the microbial framework contributing to NEC, emphasizing the importance of considering the virome and resistome alongside classical bacteriome analyses. The demonstration of prophages as active modulators regulating pathobiont dynamics offers a paradigm shift with significant translational implications.
Clinically, early identification of infants with pre-symptomatic phage signatures may enable targeted surveillance and judicious immunomodulatory interventions. For late-onset NEC, resistome-informed antibiotic stewardship could reduce risk by preserving microbial ecosystem balance.
Nevertheless, challenges persist. The complexity of virome detection, standardization of multi-omic techniques, and generalizability across diverse neonatal populations require further validation. Also, it remains to be determined whether manipulating prophage dynamics or resistomes can be safely achieved through therapeutics such as phage therapy, fecal microbiota transplantation, or selective antibiotic regimens.
Current neonatal practice guidelines (e.g., American Academy of Pediatrics, European Society for Paediatric Gastroenterology Hepatology and Nutrition) have yet to integrate virome or resistome markers due to limited clinical validation. Ongoing prospective multicenter studies incorporating multi-omic platforms and real-time analytics promise to fill these gaps.
Conclusion
Recent integrated metagenomic and metatranscriptomic research with machine learning delineates divergent microbial preludes to NEC, defined by gut phages in early-onset disease and bacterial resistomes in late-onset cases. These findings enrich understanding of NEC’s polymicrobial etiologies and present promising avenues for early, non-invasive prediction and microbiome-targeted preventive strategies.
Future research priorities include standardizing virome-resistome profiling, validating predictive biomarkers in larger cohorts, and assessing therapeutic interventions targeting the prophageome and resistome. Translation of these insights into clinical protocols could ultimately reduce NEC incidence, severity, and lifelong morbidity in vulnerable preterm infants.
References
- Zhang K, Gorelik MG, Sullivan JE, Radmacher P, Escobedo M, Warner BB, Tarr PI, Dantas G. Divergent microbial preludes to necrotising enterocolitis defined by gut phages and bacterial resistomes. Gut. 2026 Sep 16. PMID: 42749360.
- Pammi M, Cope J, Tarr PI, Warner BB, Morrow AL, Mai V, Gregory KE, McMurtry V, Ferris MJ, Saiman L. Intestinal dysbiosis in preterm infants preceding necrotizing enterocolitis: a systematic review and meta-analysis. Microbiome. 2017;5(1):31. PMID: 28399984.
- Mai V, Young CM, Ukhanova M, Wang X, Sharma R, Hudak M, George JR, Li N, Neu J. Fecal microbiota in premature infants prior to necrotizing enterocolitis. PLoS One. 2011;6(6):e20647. PMID: 21647457.
- Norman JM, Handley SA, Baldridge MT, Droit L, Liu CY, Keller BC, Kambal A, Monaco CL, Zhao G, Fleshner P, et al. Disease-specific alterations in the enteric virome in inflammatory bowel disease. Cell. 2015;160(3):447-460. PMID: 25594194.
- Rea MC, Dobson A, O’Sullivan O, Crispie F, Fouhy F, Cotter PD, Ross RP, Hill C. Microbial-mediated protection against intestinal infection: mount a good offense to protect the gut. J Physiol. 2016;594(17):4849-4861. PMID: 27301836.


