

Highlight
- Clinically significant arrhythmias occur commonly in cardiac amyloidosis (CA) and are often asymptomatic.
- Arrhythmic burden differs significantly between transthyretin amyloid cardiomyopathy (ATTR-CM) and light-chain cardiac amyloidosis (AL-CA).
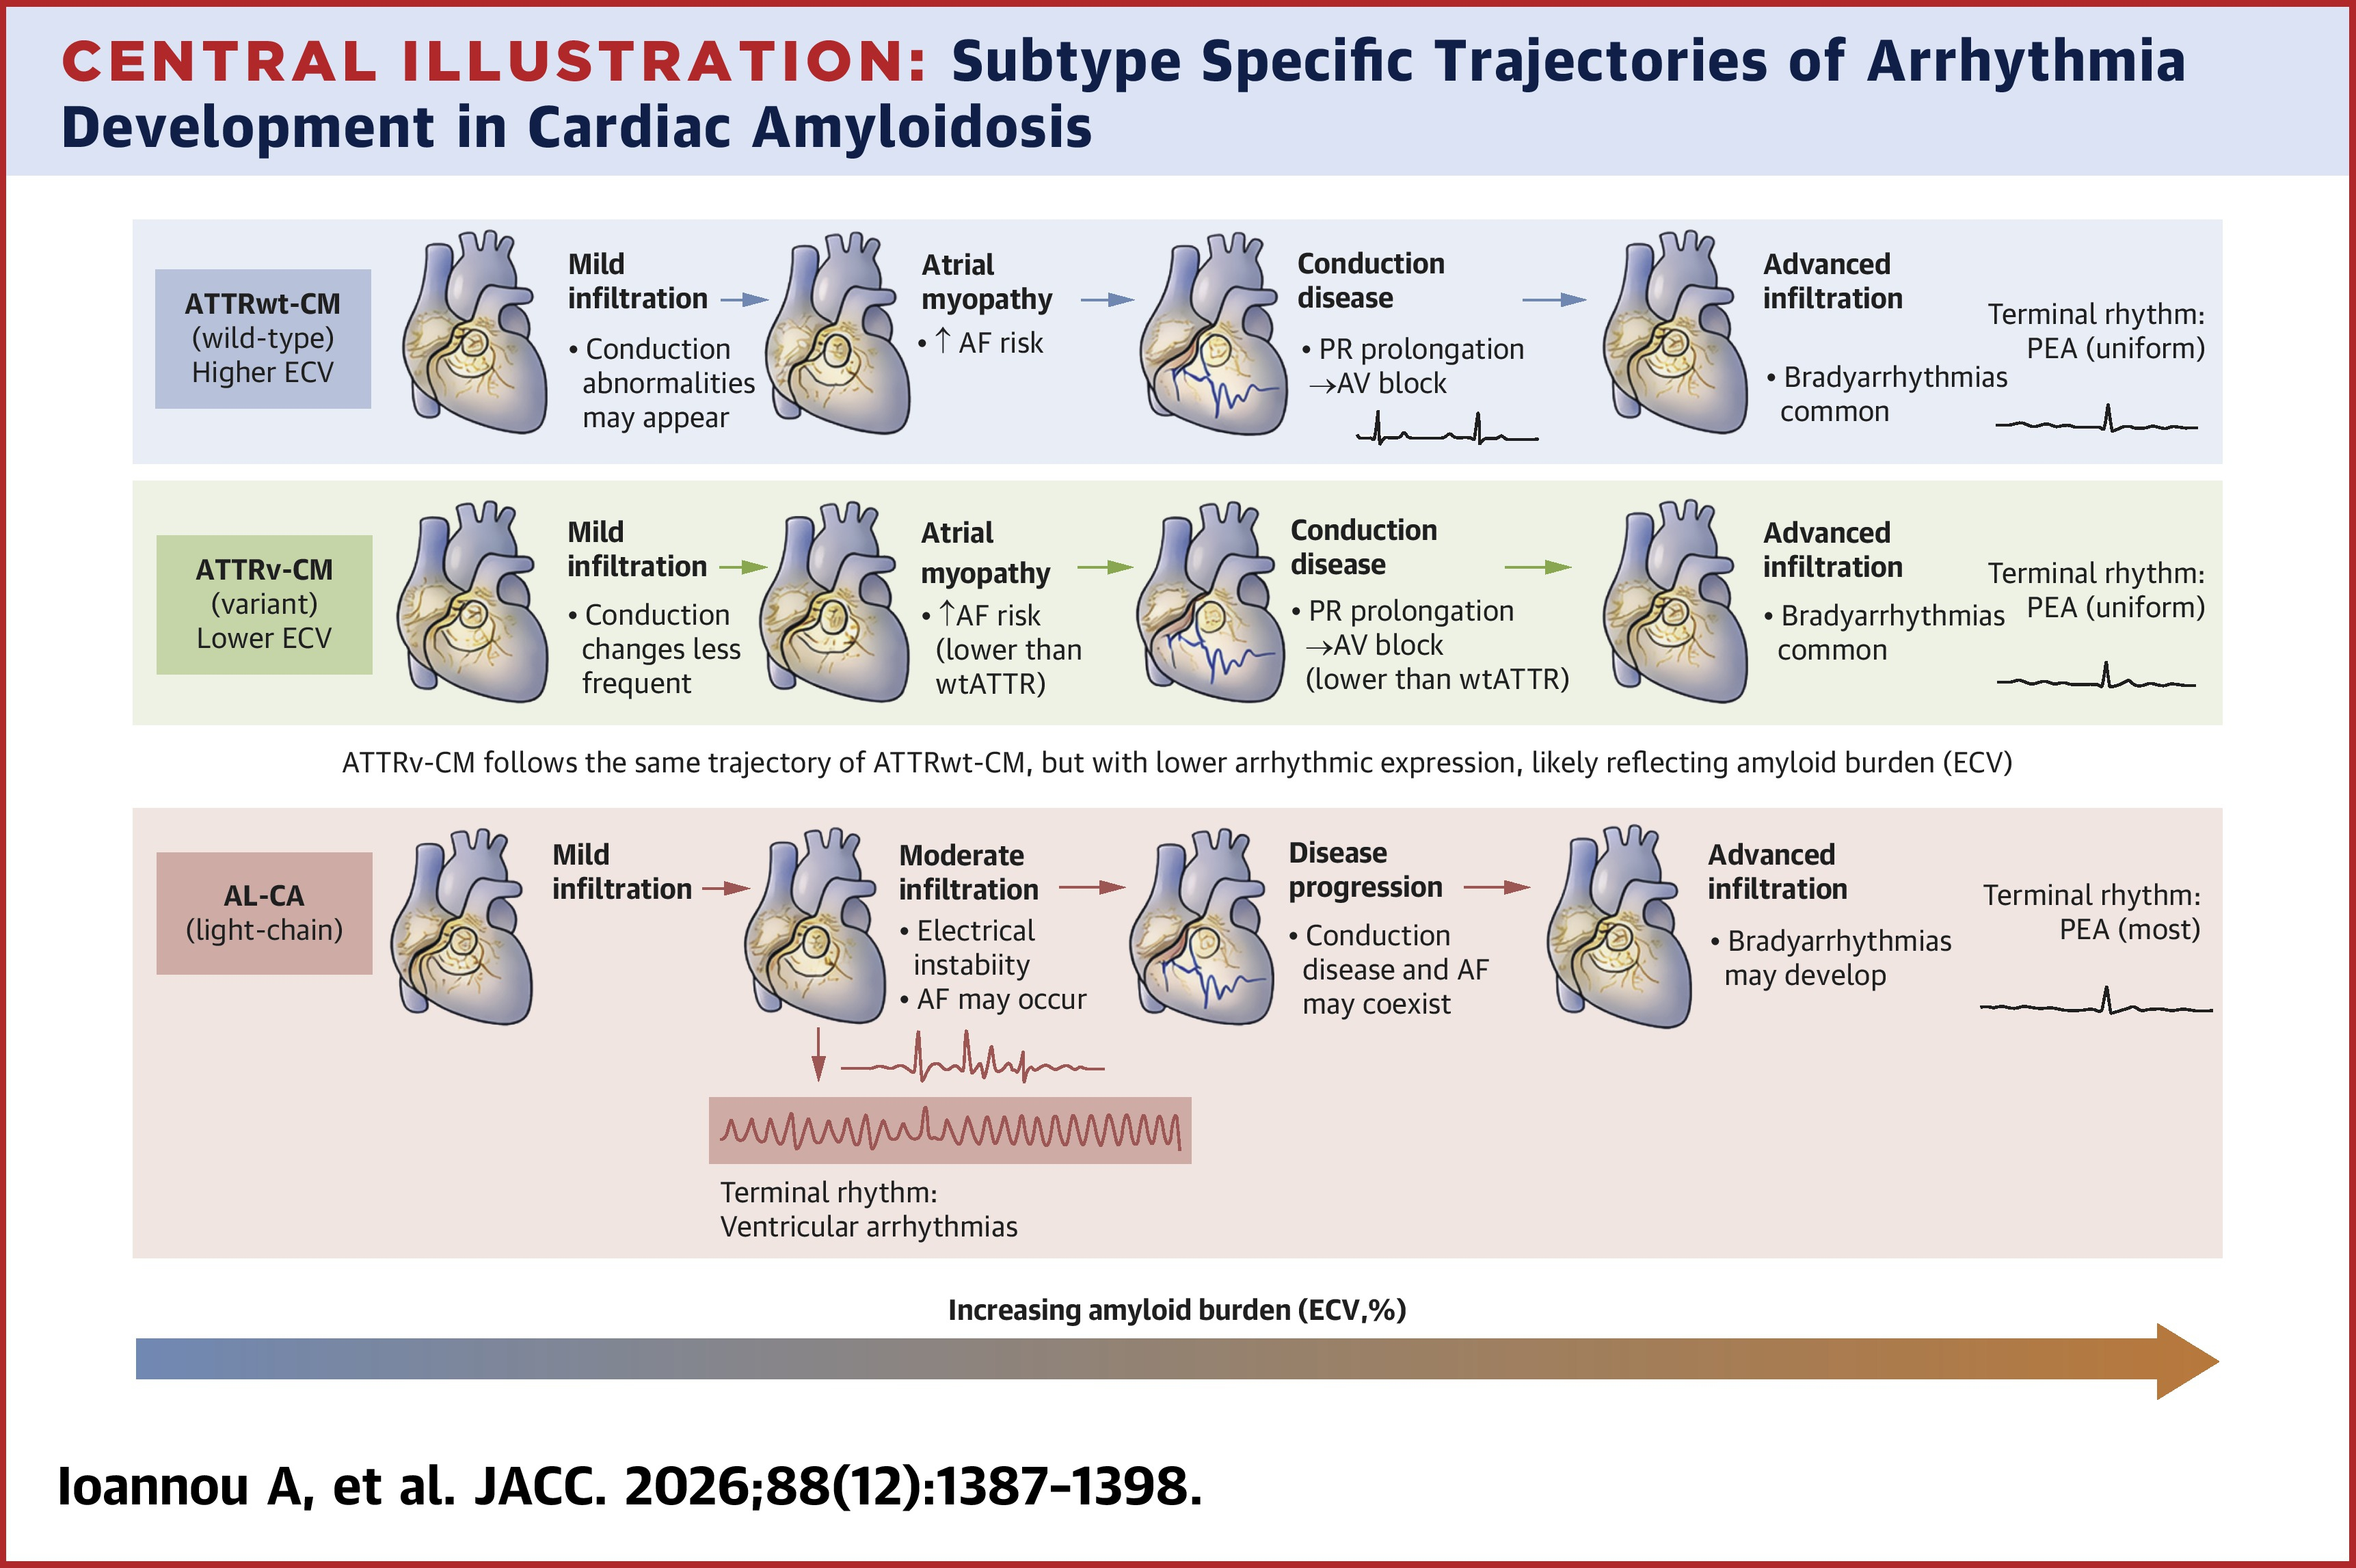
- Bradyarrhythmias and atrial fibrillation correlate strongly with myocardial amyloid burden and baseline conduction abnormalities.
- Terminal cardiac rhythms differ by amyloid subtype, with pulseless electrical activity predominating in ATTR-CM and AL-CA.
Study Background
Cardiac amyloidosis (CA) constitutes a progressive infiltrative cardiomyopathy caused by extracellular deposition of misfolded amyloid fibrils in myocardial tissue, resulting in diastolic dysfunction, restrictive cardiomyopathy, and progressive heart failure. The major subtypes are transthyretin amyloid cardiomyopathy (ATTR-CM), divided further into wild-type (ATTRwt) and hereditary variant (ATTRv), and light-chain cardiac amyloidosis (AL-CA). Arrhythmias and conduction system disease are frequently observed in CA and contribute significantly to morbidity and mortality. Nonetheless, the true burden and natural history of arrhythmias in CA remain poorly characterized, as most data derive from retrospective cohorts and intermittent monitoring methods. Improved understanding of arrhythmogenesis in CA subtypes is crucial to better risk stratify patients and optimize management strategies, including indications for device therapy.
Study Design
The EXCALIBUR trial was a prospective, single-center observational study enrolling 110 treatment-naïve patients newly diagnosed with CA, including ATTRwt-CM (n=43), ATTRv-CM (n=20), and AL-CA (n=47). Comprehensive phenotyping employed cardiac magnetic resonance imaging (CMR) to quantify myocardial amyloid burden via extracellular volume fraction (ECV). Following baseline evaluation, patients underwent implantation of implantable loop recorders (ILRs) to enable continuous, long-term cardiac rhythm monitoring. Study endpoints included incident clinically significant arrhythmias, such as bradyarrhythmias meeting indications for permanent pacemaker implantation and new-onset atrial fibrillation (AF). Associations between arrhythmic events, amyloid subtype, myocardial amyloid burden, and baseline conduction abnormalities were analyzed. The study collected survival and terminal rhythm data during follow-up.
Key Findings
Among the 110 subjects, bradyarrhythmias warranting Class I pacemaker implantation occurred in 17.3% overall, with a higher frequency in ATTR-CM (23.8%) compared to AL-CA (8.5%), indicating subtype-dependent conduction system vulnerability (P=0.036). Quantitative analyses revealed that prolonged baseline QRS duration was independently associated with increased risk of bradyarrhythmias (subdistribution hazard ratio [sHR] 1.03 per ms increase; 95% CI 1.01-1.04; P<0.001). Similarly, elevated myocardial amyloid burden as measured by ECV on CMR correlated with subsequent bradyarrhythmic events (sHR 1.06 per percent ECV increase; 95% CI 1.02-1.10; P=0.002), underscoring the pathophysiologic role of amyloid infiltration in conduction abnormalities.
Newly detected atrial fibrillation occurred in 28.2% of patients without prior AF, with notably higher incidence in ATTR-CM (50%) than AL-CA (12.2%) (P<0.001). Increased amyloid infiltration was also linked with higher risk of incident AF (sHR 1.04 per percent ECV increase; 95% CI 1.00-1.08; P=0.038). These findings implicate amyloid cardiomyopathy as a strong substrate for atrial arrhythmogenesis, especially in transthyretin-related disease.
During the median follow-up, 19.1% of patients died. The terminal cardiac rhythm in ATTR-CM patients was consistently pulseless electrical activity (PEA). In contrast, AL-CA patients predominantly exhibited PEA (81.8%), but 18.2% had sustained ventricular arrhythmias preceding death, suggesting differences in arrhythmia-mediated mortality between subtypes.
Expert Commentary
The EXCALIBUR study provides compelling prospective evidence on arrhythmia prevalence and subtype-specific patterns in CA, addressing a critical knowledge gap. The use of ILRs enabled sensitive detection of asymptomatic, clinically relevant arrhythmias that intermittent ambulatory monitoring would likely miss. The observed association between amyloid infiltration and conduction abnormalities aligns with established pathological data showing amyloid fibrils disrupt conduction tissue integrity and autonomic innervation.
These findings substantiate the clinical need for individualized arrhythmia surveillance, particularly in ATTR-CM where bradyarrhythmias and AF are prevalent and may herald progressive conduction system disease. The high incidence of new AF also raises considerations for anticoagulation strategies in this vulnerable population. The observation of differential terminal rhythms suggests mechanistic heterogeneity in sudden death pathways, warranting further investigation.
Limitations encompass the single-center design and relatively small cohort size, which may affect generalizability. Longer follow-up is required to elucidate the prognostic impact of detected arrhythmias and evaluate the outcomes of device interventions. Nonetheless, the incorporation of advanced phenotyping and continuous monitoring represents a significant strength.
Conclusion
The EXCALIBUR study elucidates the high burden and distinct patterns of arrhythmias in newly diagnosed cardiac amyloidosis, influenced by amyloid subtype and myocardial infiltration extent. These results highlight the critical importance of continuous rhythm monitoring and comprehensive phenotyping to inform personalized risk stratification and guide therapeutic decisions aiming to improve outcomes in CA patients. Future larger multi-center studies should validate these findings and optimize management algorithms incorporating arrhythmia surveillance and prevention strategies.
Funding and ClinicalTrials.gov
This study was conducted as part of the EXCALIBUR (Exploration of Arrhythmia Burden in Cardiac Amyloidosis Using Implantable Loop Recorders) trial, registered under NCT04856267. Funding sources were not explicitly stated in the primary report.
References
- Ioannou A, Patel R, Mansell J, et al. Exploration of Arrhythmia Burden in Cardiac Amyloidosis Using Implantable Loop Recorders: The EXCALIBUR Study. J Am Coll Cardiol. 2026 May 10;88(12):1387-1398. PMID: 42201646.
- Kotecha T, Martinez-Naharro A, Hawkins PN. Cardiac Amyloidosis. Circulation. 2021;143(14):1604-1618.
- Gilotra NA, Wan EY, Givertz MM. Cardiac Amyloidosis and Arrhythmias: Diagnosis and Management. J Am Coll Cardiol. 2020;75(13):1545-1557.
- Rapezzi C, Quarta CC, Riva L, et al. Disease Profile and Clinical Course of Patients with Wild-Type Transthyretin Cardiac Amyloidosis. Circulation. 2015;132(15):1560-1570.


