

Highlight
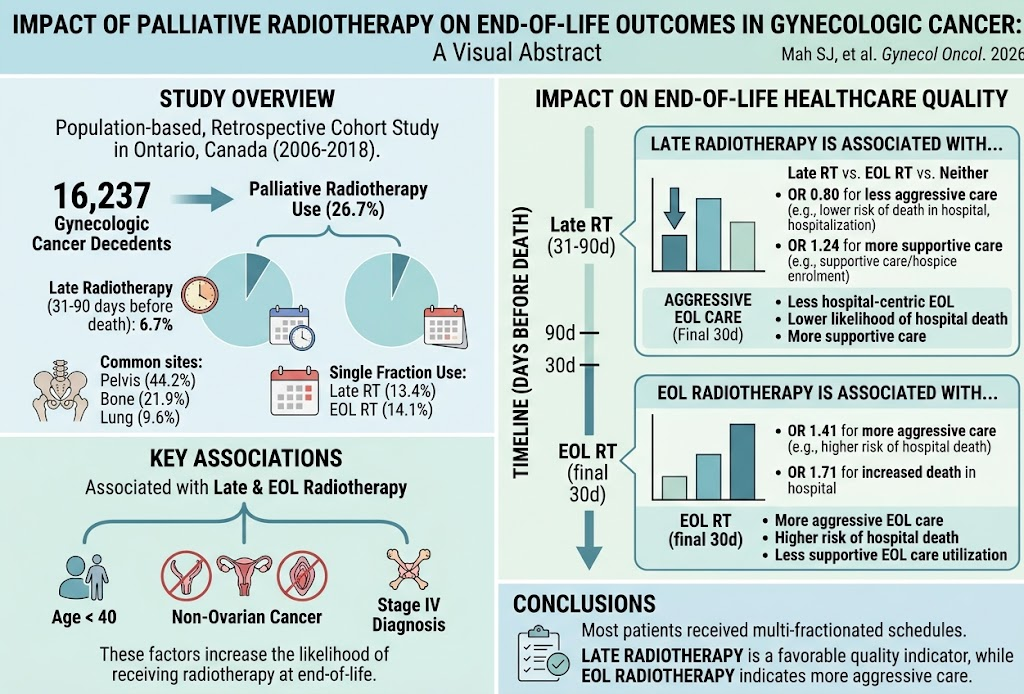
This retrospective population-based study of over 16,000 gynecologic cancer decedents in Ontario identifies that 26.7% received palliative radiotherapy near end of life (EOL). Patients receiving late radiotherapy (31–90 days before death) exhibited less aggressive EOL healthcare use, whereas radiotherapy in the last 30 days was associated with more aggressive interventions and higher rates of hospital death. Multifractionated regimens predominated across groups.
Study Background
Gynecologic malignancies, including ovarian, cervical, and uterine cancers, impose substantial morbidity and mortality worldwide. Advanced-stage disease often leads to significant symptoms such as pain, bleeding, or obstruction, which may be alleviated by palliative radiotherapy. The role of radiotherapy near EOL remains controversial, as treatment timing and intensity may affect quality of life, use of healthcare resources, and place of death. Current clinical guidelines emphasize balancing symptom relief with avoidance of aggressive, potentially burdensome care close to death. However, data specifically examining the timing of palliative radiotherapy and its impact on EOL care quality indicators in gynecologic cancers are limited.
Study Design
This population-based retrospective cohort study used linked administrative health data from ICES in Ontario, Canada, including 16,237 gynecologic cancer decedents from 2006 to 2018. The study classified palliative radiotherapy as either late radiation (31 to 90 days before death) or EOL radiation (within 30 days of death). Analysis included evaluation of radiation intent, fractionation schedules, treatment sites, patient demographics (age, cancer type, and stage), and their associations with EOL healthcare utilization metrics such as hospitalization rates, aggressive care indicators, and place of death. Multivariable regression models adjusted for confounders evaluated odds ratios (ORs) for aggressive care and supportive care outcomes.
Key Findings
Among the study cohort, 26.7% received palliative radiotherapy near EOL. Specifically, 6.7% received late radiation and 5.3% underwent radiation in the final 30 days of life. The pelvis was the predominant site treated (44.2%), consistent with local symptomatology. Most regimens involved multiple fractions; however, single-fraction schedules were utilized in 13.4% of late and 14.1% of EOL radiation cases.
Multivariable analyses identified that patients younger than 40 years, those with non-ovarian gynecologic cancers (such as cervical or uterine), and those presenting with stage IV disease were more likely to receive both late and EOL radiotherapy.
Importantly, late radiation (31-90 days before death) was associated with the lowest rate of aggressive EOL care indicators in the last 30 days compared to those receiving EOL radiation or no radiotherapy (15.6% vs. 27.7% vs. 21.0%, respectively). This included lower rates of hospitalization and death within hospital settings.
On adjusted regression analysis:
- Late radiation was significantly associated with reduced aggressive EOL care (OR 0.80, 95% CI 0.67-0.96) and increased supportive care (OR 1.24, 95% CI 1.07-1.44).
- Late radiation lowered risk of death in hospital (OR 0.86, 95% CI 0.75-0.98).
- Conversely, EOL radiation correlated with increased aggressive care (OR 1.41, 95% CI 1.16-1.73) and a markedly increased risk of hospital death (OR 1.71, 95% CI 1.44-2.02).
These findings suggest that timing of palliative radiotherapy plays a critical role in modulating healthcare utilization patterns and end-of-life experiences in this population.
Expert Commentary
This robust population-level study provides important insights into optimizing palliative radiotherapy timing in gynecologic cancers to enhance quality of EOL care. The observed benefits of late radiation suggest that earlier integration of palliative radiotherapy—before the final month of life—may facilitate better symptom control, reduce the need for aggressive interventions, and support death outside the hospital setting. The observed predominance of multifractionated regimens, despite increasing evidence supporting single-fraction approaches for symptom palliation, indicates a potential area for clinical practice improvement focused on convenience and resource stewardship.
Potential study limitations include reliance on administrative data, which may lack granular clinical details such as symptom burden or patient preferences. Additionally, the observational design cannot establish causality, and residual confounding may exist despite adjustments. Different cancer types and stages among patients may have heterogeneous treatment needs, and findings might not fully generalize beyond the Ontario healthcare context.
Conclusion
This study highlights the nuanced impact of palliative radiotherapy timing on end-of-life outcomes in gynecologic malignancies. Administering palliative radiation earlier in the trajectory of terminal illness (31 to 90 days before death) is associated with less aggressive end-of-life healthcare utilization, more supportive care measures, and a decreased likelihood of dying in hospital. Conversely, radiation delivered very close to death correlates with increased aggressive care and hospital death, potentially reflecting late treatment initiation or clinical urgency. These findings reinforce the importance of timely palliative care integration and individualized treatment planning to enhance quality of life and align care with patient-centered goals at end of life.
Future prospective studies are warranted to confirm causality, evaluate symptom control outcomes, and explore optimization of radiotherapy regimens to balance efficacy and convenience in this vulnerable population.
Funding and Clinical Trials
The cited study was supported by institutional and provincial health research organizations associated with ICES. No clinical trial registration was specified for this retrospective analysis.
References
- Mah SJ, Seow H, Carter Ramirez DM, et al. Impact of palliative radiotherapy in patients with gynecologic malignancies on end-of-life outcomes. Gynecol Oncol. 2026 Sep 21;213:82-88. PMID: 42767170.
- Harrington SE, Smith TJ. Palliative Radiotherapy at the End of Life: Balancing Potential Benefits and Burdens. JAMA Oncol. 2018;4(9):1287-1288.
- Chan KKW, et al. Single-fraction versus multiple-fraction radiotherapy for bone metastases: a systematic review and meta-analysis. Radiother Oncol. 2019;141:144-152.
- National Comprehensive Cancer Network (NCCN) Guidelines for Palliative Care. Version 2.2023.

