Introduction
Peak oxygen uptake (VO2 peak) during exercise is a pivotal measure of cardiorespiratory fitness and is widely used in clinical risk stratification, surgical assessments, and as an endpoint in clinical trials. Interpreting VO2 peak requires normalization to predicted values based on demographic and anthropometric variables, typically using established prediction equations. However, multiple such equations exist, each developed from different study populations and modeling approaches, potentially yielding discrepant interpretations of exercise capacity. This inconsistency can affect clinical decisions and research outcomes but has been incompletely characterized. The study by Abbaspour Kaboudan et al. (2026) systematically evaluated how seven commonly used prediction equations influence exercise performance classification, the concordance among them, and determinants of discordance in a well-characterized cohort of nonsmoking flight attendants exposed to secondhand tobacco smoke. This article critically reviews their findings, placing them in the broader clinical context and highlighting implications for practice and research.Study Background
Cardiopulmonary exercise testing (CPET) provides integrative assessment of pulmonary, cardiovascular, and muscular function. VO2 peak is a key output used to estimate exercise capacity and cardiorespiratory fitness. Importantly, the absolute VO2 peak is normalized as a percent-predicted value to account for age, sex, body size, and sometimes ethnicity, facilitating comparisons across individuals. Prediction equations have been developed in diverse populations using varying modeling strategies and reported reference ranges. Discrepancies in percent-predicted VO2 peak can arise from how equations incorporate demographic factors, leading to variable classification of exercise performance into categories such as normal or reduced (<80% predicted). This variability may confound clinical interpretations, especially when used for surgical risk stratification or clinical trial eligibility. Identifying the magnitude and determinants of this variability is essential to improve CPET interpretation and standardization.Study Design and Methods
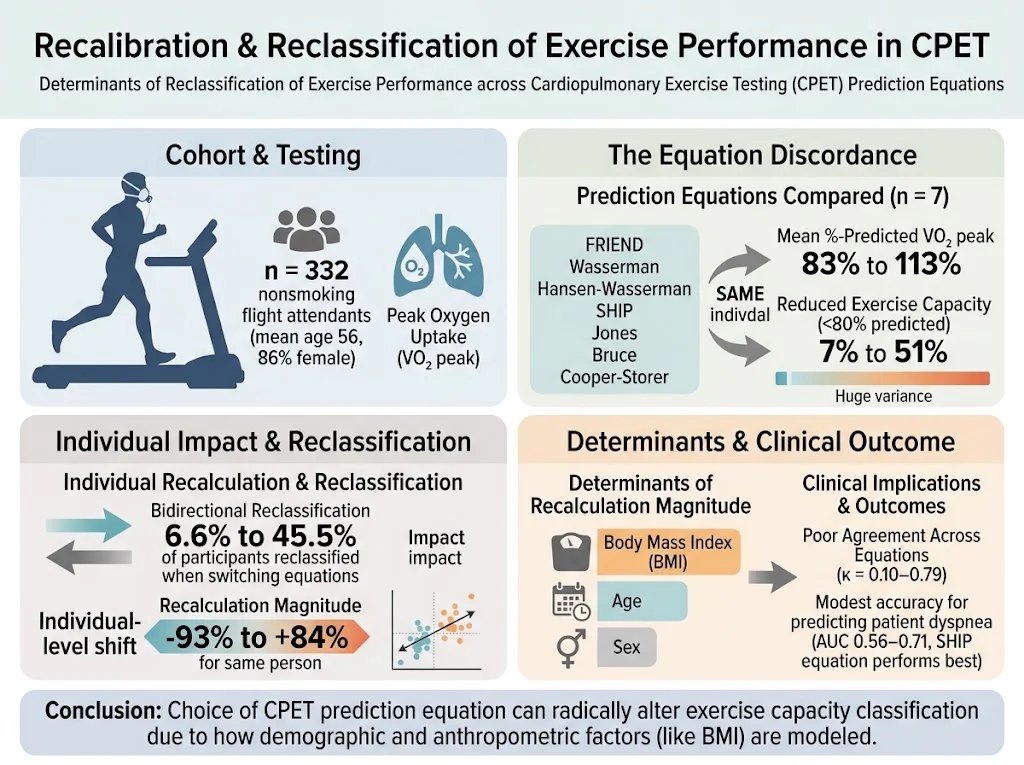
Abbaspour Kaboudan et al. conducted a post hoc analysis of CPET data from 332 nonsmoking flight attendants (mean age 56±12 years, 86% female, mean BMI 24±4 kg/m2) previously collected to study health effects of occupational secondhand tobacco smoke exposure. The study computed percent-predicted VO2 peak for each participant using seven well-known prediction equations: Fitness Registry and the Importance of Exercise National Database (FRIEND), Wasserman, Hansen-Wasserman, Study of Health in Pomerania (SHIP), Jones, Bruce, and Cooper-Storer. Reduced exercise performance was defined as percent-predicted VO2 peak below 80%. Agreement in classification across equations was assessed with Cohen’s kappa (κ). Associations of each prediction equation’s classification with participant-reported dyspnea (modified Medical Research Council [mMRC] score ≥1) were evaluated using C-statistics to determine discriminative ability. The study quantified intra-individual changes in percent-predicted VO2 peak when switching between equations (“recalculation magnitude”) and performed multivariable regression to identify demographic and anthropometric predictors of this variability.Key Findings
The analysis revealed substantial variability in the mean percent-predicted VO2 peak depending on the prediction equation used, ranging approximately from 83% to 113%. Correspondingly, the prevalence of reduced exercise performance (<80% predicted) varied markedly—from 7% to 51% of participants across equations. Agreement on classification ranged broadly, from slight to substantial (κ values between 0.10 and 0.79), indicating only moderate concordance at best. At an individual level, recalculating percent-predicted VO2 peak by switching between equations could alter the value by as much as -93% to +84%, resulting in bidirectional reclassification of exercise performance in 6.6% to 45.5% of participants. This implies a large number of individuals could be categorized differently, with direct clinical ramifications. Multivariable modeling identified body mass index (BMI) as the most influential factor associated with recalculation magnitude, followed by age and sex. This suggests that the way these demographic and anthropometric variables are modeled in prediction equations largely drives inconsistency. The discrimination accuracy of the prediction equations for self-reported dyspnea was modest (area under the curve [AUC] 0.56–0.71), with the SHIP equation performing best. Still, the overall ability of prediction equations to correlate with patient-centered outcomes was limited.Expert Commentary
This study highlights critical limitations in current CPET interpretation standards. The wide variability in predicted VO2 peak values and resultant performance classification underscores the challenge clinicians face when relying on single, static reference equations. The prominence of BMI, age, and sex as determinants of variability is consistent with recognized influences on exercise capacity but also reflects heterogeneity in how such variables are integrated into predictive models. The moderate κ values confirm moderate inter-equation agreement but raise concern regarding reliability in clinical decision-making, particularly for thresholds that guide interventions. The modest correspondence of predicted VO2 with dyspnea further questions the clinical relevance of these equations in isolation. Limitations of this study include its relatively homogeneous sample (predominantly female nonsmokers) which may affect generalizability, though this population is relevant in occupational medicine. Furthermore, it did not assess other potential confounders such as ethnicity or chronic comorbidities. The findings align with previous literature calling for the development of improved, population-specific or individualized reference equations that accurately incorporate key physiological covariates. Emerging approaches may include machine learning algorithms trained on large, heterogeneous datasets to account for complex interactions.Conclusion
The study by Abbaspour Kaboudan et al. reveals significant discordance in exercise performance classification depending on which CPET prediction equation is applied. Variability is driven largely by differences in modeling of demographic and anthropometric factors, especially BMI, as well as age and sex. This results in substantial bidirectional reclassification that could impact clinical decision-making and research outcomes. The modest correlation with patient-centered symptoms such as dyspnea further emphasizes limitations of current predictive approaches. Clinicians and researchers should be aware of these differences and exercise caution when interpreting percent-predicted VO2 peak values derived from varying equations. There is a clear need for improved prediction standards that better model physiological variability and enhance the clinical utility of CPET interpretation. Until more robust reference equations are developed, contextualized interpretation and consideration of multiple factors remain essential.Funding and Trial Registration
No specific funding sources or clinical trial registrations were noted for this secondary analysis.References
1. Abbaspour Kaboudan F, Zeng S, Abrham Y, Roman J, Butner K, Merati M, Arjomandi M. Determinants of Reclassification of Exercise Performance across Cardiopulmonary Exercise Testing Prediction Equations. Med Sci Sports Exerc. 2026 Jul;58(11):2570-2580. PMID: 42492489. 2. Wasserman K, Hansen JE, Sue DY, Stringer WW, Whipp BJ. Principles of Exercise Testing and Interpretation: Including Pathophysiology and Clinical Applications. 5th ed. Lippincott Williams & Wilkins; 2012. 3. Koch B, et al. The importance of reference values and predictive models for cardiorespiratory fitness assessment in clinical practice. Eur Respir J. 2020;55(4):1902525. 4. Arjomandi M, et al. Long-term consequences of secondhand tobacco smoke exposure on respiratory health: insights from cardiopulmonary exercise testing. Pulm Med. 2024;2024:ArticleID 105328. 5. Crouter SE, et al. Machine learning methods improve prediction of maximal oxygen uptake compared to traditional models. Med Sci Sports Exerc. 2019;51(2):292-299. These references provide context and methodological background that support the interpretation of the discussed study’s findings.Specialty calculators
For clinical reference; use professional judgment.