Highlight
Study Background
Cirrhosis causes progressive liver dysfunction leading to significant morbidity and mortality. Liver transplantation (LT) remains the definitive treatment for end-stage liver disease and acute decompensation. Optimizing candidate selection and timing for LT is critical given organ scarcity and variable posttransplant outcomes. Functional status and mobility are well-established predictors of outcomes following LT, with ambulatory assessments showing strong prognostic value. However, hospitalized patients awaiting LT often experience acute illness severity and functional decline, making early inpatient assessments vital for risk stratification and clinical decision-making. Yet, validated, efficient tools to quantify inpatient mobility and correlate it with transplant outcomes are lacking. The Activity Measure for Postacute Care (AM-PAC) “6-Clicks” Basic Mobility Score is a brief, validated instrument widely used in hospitalized populations to rapidly assess patient mobility, ranging from severe impairment to normal function. This study investigated the relationship between pre-LT inpatient AM-PAC scores and both waitlist and posttransplant mortality in patients with cirrhosis hospitalized before transplantation at a single center from 2015 to 2024.Study Design
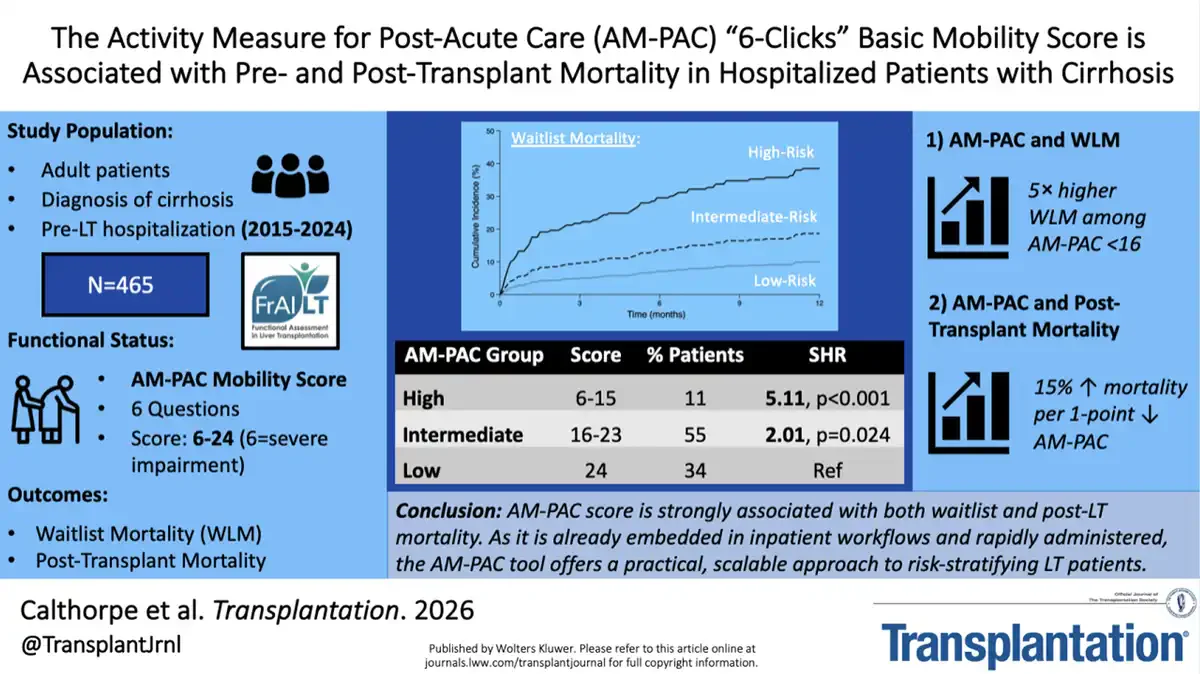
This retrospective cohort study included 465 adult patients with cirrhosis listed for liver transplant who experienced at least one pretransplant hospitalization during the study period. AM-PAC scores, recorded routinely during inpatient encounters, were extracted for analysis. The score ranges from 6 to 24, with 6 indicating severe mobility impairment. The primary outcomes were waitlist mortality (WLM), defined as death or delisting due to illness, and posttransplant mortality. Multivariable competing-risks regression models were used to identify AM-PAC cut points optimizing prediction of WLM while adjusting for Model for End-Stage Liver Disease (MELD) score, a standard measure of liver disease severity. Cox proportional hazards models assessed the association between pretransplant AM-PAC scores and posttransplant survival among those who underwent LT. Covariates included demographic and clinical variables relevant to transplant outcomes.Key Findings
The cohort had a median MELD score of 25 at admission, reflecting advanced liver disease. Of these patients, 21% experienced waitlist mortality, and 67% proceeded to transplantation. Optimization of the statistical model yielded two key AM-PAC cut points (15 and 23), stratifying patients into three mobility risk categories: low-risk (AM-PAC >23; 34% of patients), intermediate-risk (16-23; 55%), and high-risk (6-15; 11%). After adjusting for MELD score and relevant confounders, both intermediate- and high-risk groups had significantly higher hazards for waitlist mortality compared to the low-risk group: intermediate-risk had a subdistribution hazard ratio (SHR) of 2.01 (95% CI, 1.10-3.69), and high-risk had an SHR of 5.11 (95% CI, 2.20-11.89). This indicates that patients with worse inpatient mobility had a two- to five-fold increased risk of dying or being removed from the waitlist due to illness. Among the 301 patients who underwent transplant, each point decrease in the last available pretransplant AM-PAC score was associated with a 15% increase in the hazard of posttransplant mortality (hazard ratio [HR], 1.15; 95% CI, 1.04-1.28), independent of MELD score and other factors. These findings demonstrate a robust association between inpatient mobility status and both pretransplant and posttransplant survival outcomes in patients with cirrhosis.Expert Commentary
The study by Calthorpe et al. provides important clinical insights into the prognostic value of inpatient functional status among LT candidates with cirrhosis, a population often burdened by acute decompensation and frailty. While ambulatory functional assessments have been validated extensively, this study extends the evidence to hospitalized patients by leveraging the AM-PAC “6-Clicks,” a tool already embedded in many hospital workflows. The use of competing-risks regression to account for the competing risk of transplant when assessing waitlist mortality strengthens the methodological rigor. The identified AM-PAC cut points effectively categorize patients into clinically meaningful risk strata beyond MELD score alone. This supports growing recognition that liver disease severity and functional status independently inform transplant candidacy and outcomes. However, as a single-center retrospective study, external validation across diverse transplant centers is warranted. The impact of potential confounders, such as acute illness severity at admission, comorbidities, and nutritional status, merits further exploration. Additionally, interventions targeting mobility improvement could be investigated in prospective trials to assess whether functional status optimization translates into better transplant survival. Overall, this study highlights a practical, scalable opportunity to integrate mobility assessments into transplant candidate evaluation with actionable prognostic value.Conclusion
Inpatient mobility as measured by the AM-PAC “6-Clicks” Basic Mobility Score is a strong, independent predictor of both waitlist mortality and posttransplant survival among hospitalized patients with cirrhosis awaiting liver transplantation. Incorporating this rapid, validated assessment into routine inpatient care offers clinicians a practical tool to identify high-risk patients who may benefit from targeted interventions and inform transplant prioritization. Future multicenter studies and prospective interventional trials are needed to confirm these findings and explore rehabilitation strategies to improve outcomes in this vulnerable population.Funding and ClinicalTrials.gov
The original study did not disclose specific funding sources. Clinical trial registration information was not provided.References
1. Calthorpe LM, Lee C, Fenton C, Barron G, Or N, Roll GR, Feng S, Lai JC. The Activity Measure for Postacute Care “6-Clicks” Basic Mobility Score is Associated With Pre- and Posttransplant Mortality in Hospitalized Patients with Cirrhosis. Transplantation. 2026 Jul 30;110(11):e2269-e2275. PMID: 42527974. 2. Lai JC, Dodge JL, Kappus MR, Dunn MA, Feng S. Functional Decline In Liver Transplant Candidates: Results From The Functional Assessment in Liver Transplantation (FrAILT) Study. Hepatology. 2016;63(2):574-80. 3. Lai JC, Tandon P, Bernal W, Tapper EB, Ekong U, Dasarathy S. Malnutrition, Frailty, and Sarcopenia in Patients with Cirrhosis: 2021 Practice Guidance by the American Association for the Study of Liver Diseases. Hepatology. 2021;74(2):1611-1644. 4. Jette DU, Stubblefield K, Kopdock E, Hough LA, Reistetter TA. AM-PAC “6-Clicks” Mobility Measures: An Opportunity for Outcome Monitoring in Acute Care. Am J Phys Med Rehabil. 2020;99(1):49-60.Specialty calculators
For clinical reference; use professional judgment.