

Highlight
– Titin-truncating variants (TTNtv) are the leading genetic cause of dilated cardiomyopathy (DCM), yet routine screening of at-risk relatives yields low diagnostic yield.
– A large multicenter cohort identified key risk factors—age ≥30 years, male sex, and partial DCM phenotype—that stratify relatives into distinct risk profiles.
– A tailored screening algorithm recommends personalized intervals of 1, 3, or 5 years, balancing early detection with resource optimization.
– Implementation of this risk-based stratification promises to improve clinical care and minimize unnecessary surveillance burden.
Background and Clinical Context
Dilated cardiomyopathy (DCM) is a major cause of heart failure characterized by left ventricular dilatation and systolic dysfunction. It often results in significant morbidity, sudden cardiac death, or the need for transplantation. Genetics plays a pivotal role, with titin-truncating variants (TTNtv) constituting the most prevalent pathogenic cause among familial DCM cases. Guidelines currently advocate for regular screening of at-risk relatives carrying pathogenic variants; however, the diagnostic yield is often modest, and optimal screening intervals remain undefined. This leads to potential overuse of healthcare resources and patient anxiety from unnecessary procedures.
This imperative to tailor screening has motivated efforts to develop safe, evidence-based, gene-specific algorithms that consider individual risk factors to optimize surveillance frequency and resource allocation.
Study Design and Methods
This multicenter, longitudinal cohort study analyzed relatives carrying likely pathogenic or pathogenic TTN truncating variants from seven specialized centers. Inclusion criteria required relatives to be genotype-positive with or without initial phenotypic abnormalities. Baseline clinical phenotypes were classified as genotype-positive/phenotype-negative (no left ventricular dysfunction or dilatation) or partial DCM (meeting only one diagnostic criterion for DCM).
Participants underwent serial cardiac screening including echocardiography to detect left ventricular dilatation and dysfunction. The cohort was followed with a median duration of 5.7 years. The primary endpoint was development of DCM, defined by combined echocardiographic criteria, while secondary endpoints included major adverse cardiac events (MACE) such as arrhythmias, heart failure hospitalization, or cardiac death.
Predictors of DCM emergence were identified through statistical analyses of longitudinal follow-up data. Age, sex, and baseline partial DCM criteria emerged as significant factors. These aided stratification into three risk profiles. A multistate Markov model was constructed to inform the proposed screening interval algorithm balancing safety (early disease detection) and efficiency (reducing unnecessary screening).
Key Findings and Results
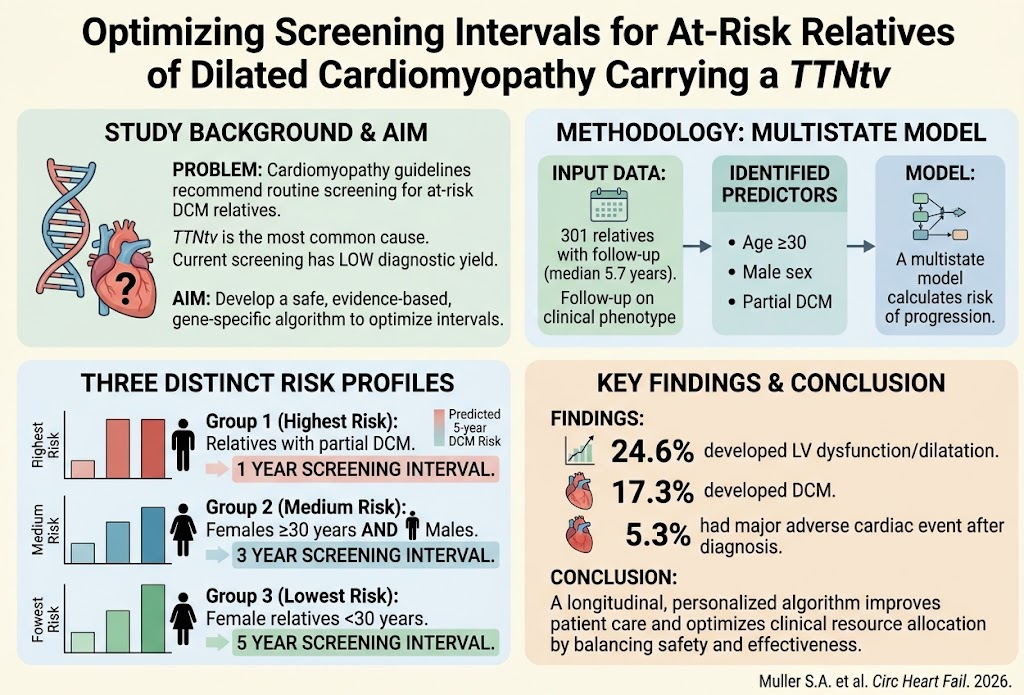
The study enrolled 413 TTNtv relatives, with follow-up data available for 301. Over this median 5.7-year follow-up, 24.6% of relatives developed left ventricular dysfunction or dilatation, and 17.3% progressed to overt DCM. Among those diagnosed with DCM, 5.3% (16 individuals) experienced major adverse cardiac events.
Three distinct risk profiles were delineated based on age, sex, and partial DCM presence at baseline:
- High-risk group: Relatives with partial DCM phenotype at baseline, irrespective of age or sex, exhibiting the highest progression rate.
- Intermediate-risk group: Males of any age and females aged ≥30 years without partial DCM at baseline.
- Low-risk group: Females younger than 30 years without partial DCM.
Using these profiles, the authors recommended personalized screening intervals as follows:
- Annual screening for high-risk relatives (partial DCM phenotype).
- Screening every 3 years for intermediate-risk subjects (males and older females without partial phenotype).
- Screening every 5 years for low-risk younger female relatives (<30 years) without partial signs.
This stratified approach was shown to optimize early disease detection while minimizing screening frequency and resource use in lower-risk groups, potentially reducing patient burden and healthcare costs.
Expert Commentary
The study robustly addresses an important clinical gap in managing relatives with TTNtv at risk for DCM. Strengths include a sizable cohort with long-term follow-up, comprehensive phenotyping, and use of advanced modeling techniques to integrate multiple risk factors into practical recommendations.
While the genotype-specific approach aligns with precision medicine paradigms, some limitations warrant acknowledgement. The cohort was derived from specialized centers, potentially limiting generalizability. Ethnic and environmental factors influencing penetrance were not deeply analyzed. Furthermore, the definition of partial DCM phenotype might vary across practices, necessitating standardization. External validation in broader populations will be critical.
Mechanistically, TTNtv lead to impaired sarcomeric function and myocardial vulnerability, more pronounced under stress or with age. The identification of age and sex as modifiers is consistent with known biological influences on DCM expression, supporting the biological plausibility of stratified surveillance.
Conclusion and Future Directions
This study presents a compelling evidence-based, gene-specific algorithm for longitudinal cardiac screening of relatives harboring TTN truncating variants. By incorporating age, sex, and echocardiographic intermediate phenotypes, the algorithm efficiently balances patient safety and resource allocation.
Implementing such a stratified strategy in clinical practice could refine the care of TTNtv carriers, enabling early intervention in high-risk individuals while reducing unnecessary investigations in low-risk groups. Future investigations should aim to validate these findings prospectively, explore genotype-environment interactions, and assess patient-centered outcomes and health economics impacts.
Ultimately, this work exemplifies the movement toward precision cardiogenetics, underscoring that personalized risk stratification can optimize screening and improve clinical management in inherited cardiomyopathies.
Reference
Muller SA, Beelen NJ, Paldino A, Gonzalez-Maniega C, Bundgaard H, Christensen AH, Vissing CR, Johnson R, Kramarenko DR, Venner MFGHM, Del Mestre E, Ellenbroek GHJM, Dominiquez F, Dal Ferro M, Merlo M, Stroeks SLVM, Sinagra G, Amin AS, Fatkin D, Garcia-Pavia P, Te Riele ASJM, Verdonschot JAJ. Optimizing Screening Intervals for At-Risk Relatives of Dilated Cardiomyopathy Carrying a TTNtv. Circ Heart Fail. 2026 Sep 21:e013822. doi: 10.1161/CIRCHEARTFAILURE.125.013822. Epub ahead of print. PMID: 42765307.


