

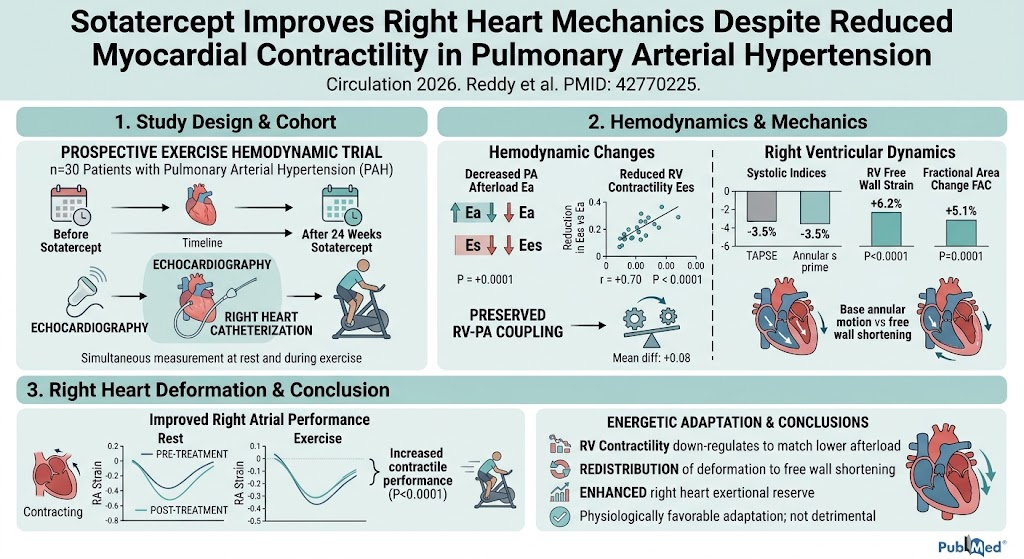
Highlight
Sotatercept reduces pulmonary arterial afterload and proportionally decreases right ventricular (RV) contractility, preserving RV-PA coupling.
Systolic function shifts from annular to RV free wall mechanics, improving global right heart deformation.
Right atrial filling and contractile performance improve under sotatercept, both at rest and during exercise.
This reflects an energetically favorable adaptation with improved exertional right heart reserve in pulmonary arterial hypertension (PAH).
Study Background and Disease Burden
Pulmonary arterial hypertension (PAH) is a progressive disease characterized by elevated pulmonary vascular resistance leading to increased RV afterload. The RV’s ability to adapt to pressure overload strongly influences clinical outcomes and survival in PAH. Current PAH therapies primarily target vasodilation but have limited direct, consistent effects on RV function. Sotatercept, a novel fusion protein acting through the transforming growth factor-beta superfamily pathway, has demonstrated efficacy in reducing pulmonary vascular resistance and improving clinical status. However, its effects on intrinsic RV contractility and RV-arterial coupling under resting and stress conditions remain unclear. Understanding how sotatercept modulates right heart mechanics is crucial to optimize therapeutic strategies in PAH.
Study Design
This prospective exercise hemodynamic trial enrolled 30 patients with diagnosed PAH (70% female; mean age 49.3 years) between July 2024 and May 2025. Participants underwent combined echocardiography and invasive pressure measurements during rest and incremental exercise before and after 24 weeks of sotatercept treatment. Key parameters measured included end-systolic elastance (Ees) as a load-independent index of RV contractility, pulmonary arterial elastance (Ea) representing afterload, and their ratio (Ees/Ea) as a measure of RV-PA coupling. Additional assessments comprised RV and right atrial deformation indices via strain imaging, tricuspid annular plane systolic excursion (TAPSE), systolic velocity of the lateral tricuspid annulus, RV free wall strain, and fractional area change. Mixed-effects statistical models were used to analyze changes over time and during exercise.
Key Findings
After 24 weeks of sotatercept, patients exhibited a significant reduction in pulmonary arterial elastance (Ea), indicating decreased RV afterload. This reduction correlated strongly with a proportional decline in RV contractility (Ees) (r=+0.70, p<0.0001), resulting in preserved RV-PA coupling (Ees/Ea ratio change not statistically significant). Although conventional systolic markers at the tricuspid annulus (TAPSE and lateral annular systolic velocity) decreased, RV free wall systolic function demonstrated marked improvement. Resting and exercise RV free wall strain increased by an average of 6.2% (p<0.0001) with increased fractional area change (p=0.0001). Enhanced deformation suggests a shift from annular motion to free wall shortening, reflecting improved intrinsic myocardial mechanics. Right atrial function also improved significantly, with better filling and contractile performance during both rest and exertion (p<0.0001). Importantly, the maximal rate of RV pressure rise over time (dP/dtmax) decreased alongside contractility, consistent with reduced myocardial energy expenditure.
Expert Commentary
This study elucidates sotatercept’s nuanced effects on right heart mechanics in PAH. The proportional decrease in RV contractility alongside afterload reduction prevents ventricular-arterial uncoupling, a critical determinant of RV failure. The shift in systolic mechanics from annular motion to enhanced free wall contraction suggests compensatory myocardial remodeling supporting efficient RV performance. Improved right atrial function likely contributes to optimized RV preload and cardiac output, particularly during exertion. These findings align with evolving concepts that therapeutic targets in PAH should address both vascular and ventricular components. Limitations include the relatively small sample size and short-term follow-up; larger studies are needed to confirm clinical impact on long-term RV function and outcomes. The preserved RV-PA coupling despite lower contractility underlines the importance of matching myocardial contractile energy to reduced afterload, which may translate to improved energetic efficiency in the failing RV.
Conclusion
Sotatercept provides a clinically favorable modulation of right heart mechanics in PAH by decreasing pulmonary arterial afterload and RV contractility in a balanced manner, preserving RV-PA coupling, and enhancing right ventricular free wall and right atrial function. This energetic optimization likely supports improved right heart reserve and exercise capacity without adversely affecting systolic performance. The results highlight the therapeutic potential of sotatercept beyond vascular remodeling by directly influencing cardiac mechanics, opening avenues for comprehensive management of right heart dysfunction in PAH.
Funding and ClinicalTrials.gov Registration
This study was registered at ClinicalTrials.gov (NCT06409026). Further details regarding funding were not disclosed.
References
1. Reddy YNV, Kazui S, Miranda WR, et al. Sotatercept Improves Right Heart Mechanics Despite Reduced Myocardial Contractility in Pulmonary Arterial Hypertension: A Prospective Exercise Hemodynamic Study. Circulation. 2026 Sep 22. PMID: 42770225.
2. Galiè N, Humbert M, Vachiery JL, et al. 2015 ESC/ERS Guidelines for the diagnosis and treatment of pulmonary hypertension. Eur Heart J. 2016 Jan 1;37(1):67-119.
3. Kawut SM, Widlitz AC, Bagiella E, et al. Right ventricular function and pulmonary hypertension: concepts and challenges. Circulation. 2005 Oct 11;112(15):2094-9.
4. Humbert M, Coghlan JG, Ghofrani HA. The evolving landscape of pulmonary arterial hypertension therapies. Eur Respir J. 2019 Mar 7;53(3):1801904.


