

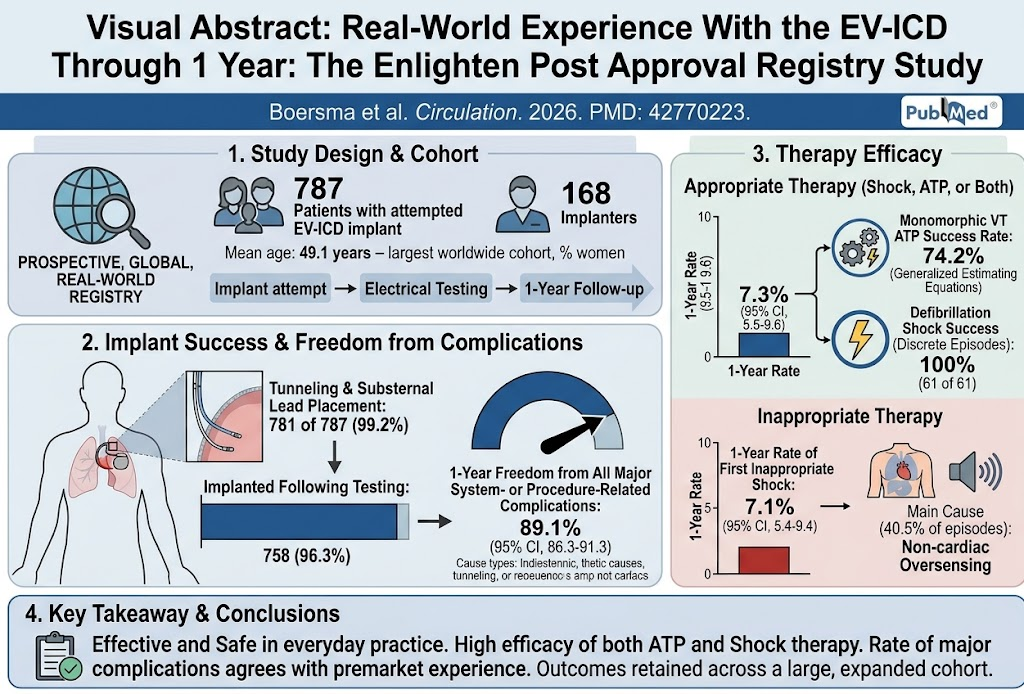
Highlight
- The EV-ICD provides effective defibrillation and antitachycardia pacing without intravascular leads, reducing lead-associated risks.
- In a prospective global registry of 787 patients, EV-ICD implantation succeeded in 99.2% of attempts with a 1-year major complication-free survival rate of 89.1%.
- Shock therapy demonstrated 100% success in terminating discrete spontaneous ventricular arrhythmias; antitachycardia pacing succeeded in 74.2% of monomorphic ventricular tachycardia episodes.
- The rate of inappropriate shocks within 1 year was 7.1%, primarily due to noncardiac oversensing, highlighting areas for device optimization.
Study Background
Implantable cardioverter defibrillators (ICDs) are cornerstone therapies for preventing sudden cardiac death in patients at risk of life-threatening ventricular arrhythmias. Conventional transvenous ICDs involve leads implanted within intravascular spaces, which can be associated with complications such as lead fracture, infection, venous occlusion, and cardiac perforation. The extravascular implantable cardioverter defibrillator (EV-ICD) was developed to mitigate these risks by avoiding intravascular lead placement. Instead, the EV-ICD lead is implanted in the substernal space, outside the vasculature, potentially offering a safer therapeutic option while providing both defibrillation and antitachycardia pacing capabilities. Although premarket trials have demonstrated promising efficacy and safety outcomes up to 3 years, real-world data reflecting diverse patient populations, broader implanter experience, and novel device sensing algorithms remain essential to validate these findings. The Enlighten Post Approval Registry addresses this gap by systematically collecting prospective, global data from clinical practice on the Aurora EV-ICD system.
Study Design
The Enlighten study is a prospective, multicenter, global post-approval registry designed to evaluate the safety and effectiveness of the EV-ICD through 1 year following implantation. A total of 787 patients across multiple centers underwent attempted EV-ICD implantation by 168 physicians, reflecting an expanded and heterogeneous user base. Patients had a mean age of 49.1 years (±15.2), with 28.7% female representation and 34.1% receiving devices for secondary prevention of ventricular arrhythmias. The main safety endpoint was freedom from major complications related to the EV-ICD system or implantation procedure within the first year. Effectiveness endpoints included rates of appropriate therapies (both shock and antitachycardia pacing) for ventricular arrhythmias, as well as inappropriate shock incidence. The Kaplan-Meier method was employed to estimate event rates at 1 year, and generalized estimating equations accounted for multiple arrhythmic episodes per patient in efficacy analyses.
Key Findings
Implantation Success and Safety: The EV-ICD lead was successfully tunneled and placed substernally in 781 of 787 patients, yielding a high procedural success rate of 99.2%. Defibrillation and electrical testing confirmed adequate system function in 758 patients (96.3%), who remained implanted thereafter. The freedom from major system- or procedure-related complications rate at 1 year was 89.1% (95% confidence interval [CI], 86.3%-91.3%), indicating an acceptable safety profile consistent with premarket data. The most common serious complications were not detailed but would traditionally include infection, lead dislodgement, and procedural adverse events.
Therapy Effectiveness: During 1 year of follow-up, the first appropriate therapy rate was 7.3% (95% CI, 5.5%-9.6%). Shock therapy was 100% successful in terminating discrete spontaneous ventricular arrhythmias, with all 61 detected episodes effectively treated. Antitachycardia pacing (ATP), designed to terminate monomorphic ventricular tachycardia (VT) without shocks, demonstrated a success rate of 74.2% after statistically adjusting for multiple episodes within patients, affirming ATP’s utility in the EV-ICD system.
Inappropriate Shocks: The 1-year incidence of first inappropriate shock was 7.1% (95% CI, 5.4%-9.4%), comparable to rates reported in traditional ICD cohorts. The predominant mechanism was noncardiac oversensing, accounting for 40.5% of inappropriate shock episodes, highlighting an area for improvement in signal discrimination and device programming.
Expert Commentary
The Enlighten Registry’s real-world data provide reassuring evidence supporting the clinical adoption of the EV-ICD system. Its substernal lead placement avoids many of the complications inherently linked with transvenous leads, potentially reducing long-term morbidity related to lead failure and infection. The high procedural success rate underlines that with proper training and experience, broad deployment by implanters is feasible. The 100% shock efficacy validates the device’s lifesaving capability, while meaningful ATP success offers patients reduced exposure to shocks, which are known to impact quality of life negatively.
Nonetheless, the 7.1% inappropriate shock rate, predominantly due to oversensing of noncardiac signals, highlights a persistent challenge. Advances in sensing algorithms and device software updates will be pivotal to minimize this burden. Limitations include the observational nature of the registry, lack of a control arm, and potential variations in implanter technique or patient selection. Comprehensive long-term follow-up beyond 1 year is warranted to confirm durability and chronic safety, as well as comparative studies with transvenous and subcutaneous ICDs.
Conclusion
The Enlighten Post Approval Registry establishes that the EV-ICD maintains favorable safety and efficacy profiles seen in earlier trials when applied in routine clinical practice worldwide. Its extravascular configuration offers an effective alternative for ventricular arrhythmia management, combining shock and antitachycardia pacing therapies without intravascular leads. Continued innovation to reduce inappropriate therapies and further long-term studies are needed, but the EV-ICD represents a significant advancement in device-based sudden cardiac death prevention.
Funding and ClinicalTrials.gov
The registration for this study is listed on ClinicalTrials.gov (Identifier: NCT06048731). Details regarding study funding are not specified in the provided data.
References
1. Boersma LVA, Amin A, Murgatroyd F, et al. Real-World Experience With the Extravascular Implantable Cardioverter Defibrillator Through 1 Year: The Enlighten Post Approval Registry Study. Circulation. 2026 Sep 22; PMID: 42770223.
2. Knops RE, Olde Nordkamp LRA, de Groot JR, et al. Substernal lead placement for the extravascular implantable cardioverter defibrillator: Surgical techniques and initial results. Heart Rhythm. 2020;17(9):1509-1516.
3. Poole JE, Johnson GW, Hellkamp AS, et al. Prognostic importance of defibrillator shocks in patients with heart failure. N Engl J Med. 2008;359(10):1009-1017.
4. Gold MR, Theuns DA, Knight BP. Review of the subcutaneous implantable defibrillator system. Circ Arrhythm Electrophysiol. 2017;10(11):e005588.


