

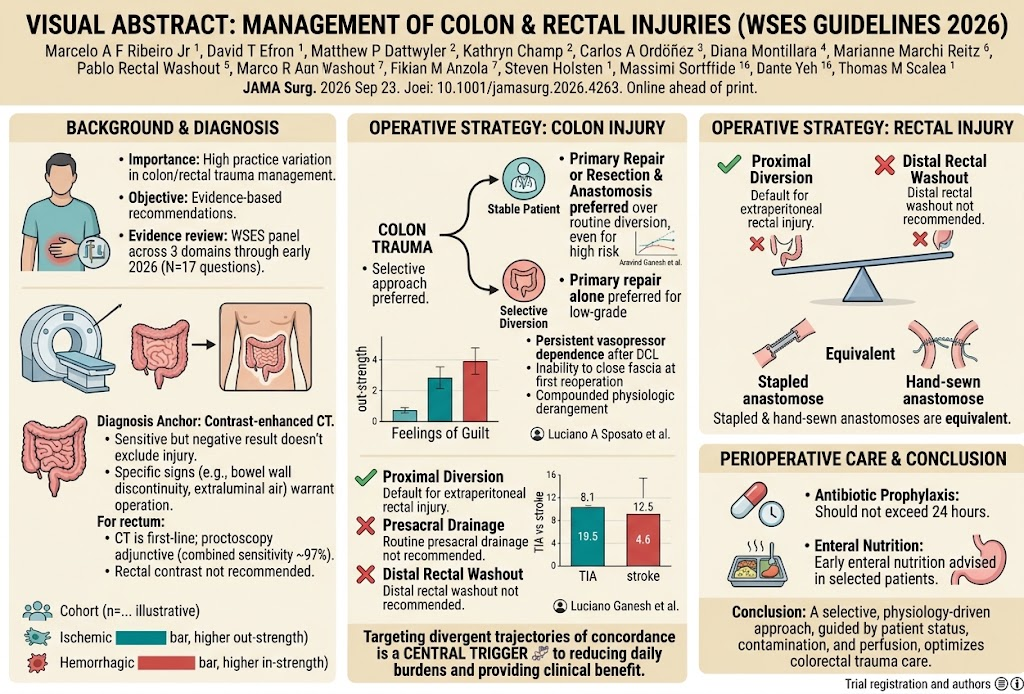
Introduction and Context
Traumatic injuries of the colon and rectum—whether from penetrating wounds (gunshots, stabbings) or blunt mechanisms (motor vehicle collisions, crush injuries)—present acute management challenges and historically have yielded wide variation in surgical practice. For decades, fecal diversion (colostomy) was commonly performed to avoid septic complications. Over recent decades, however, growing observational evidence and evolving surgical practice have shifted toward selective primary repair and anastomosis when patient physiology permits.


