

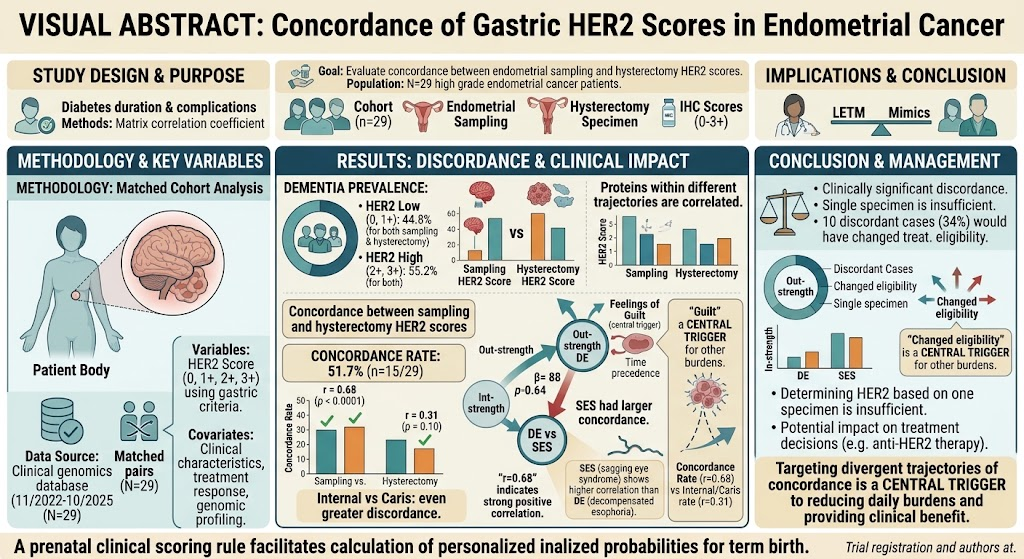
Highlight
- Significant discordance exists between gastric HER2 scores in endometrial biopsy (sampling) and hysterectomy specimens in high-grade endometrial cancer.
- About half of patients had discordant HER2 scores with potential treatment eligibility implications.
- Current standards relying on either sampling or hysterectomy HER2 assessment alone may lead to suboptimal therapeutic decision-making.
- Only a minority of tumors harbor ERBB2 amplification, underscoring complexity beyond gene amplification in HER2 scoring.
Study Background
Endometrial cancer represents one of the most common gynecologic malignancies, with high-grade subtypes such as serous carcinoma exhibiting aggressive behavior and poorer prognosis. Human epidermal growth factor receptor 2 (HER2) targeted therapies have emerged as promising options in this group, necessitating accurate HER2 status determination. Unlike breast cancer, where HER2 testing criteria are well-established, endometrial cancer HER2 assessment often extrapolates gastric cancer gastric HER2 scoring guidelines, which differ for biopsy and resection specimens.
Given the practical reliance on diagnostic endometrial sampling (biopsy or curettage) to guide treatment, understanding the concordance of HER2 scores between biopsy and definitive hysterectomy specimens is critical. A mismatch could affect eligibility for HER2-targeted treatments like trastuzumab and influence clinical outcomes.
Study Design
This retrospective study analyzed patients with high-grade endometrial cancer who had matched endometrial sampling and hysterectomy specimens, collected between November 2022 and October 2025 from a clinical genomics database at a single institution. HER2 status was scored using gastric cancer HER2 immunohistochemistry (IHC) criteria, separately calibrated for biopsy and resection specimens, with scoring categories 0, 1+, 2+, and 3+. Clinical data, response to HER2-targeted therapies, and genomic profiling results, including ERBB2 gene amplification, were collected.
The primary endpoint was the concordance between HER2 scores of the endometrial sampling specimens versus hysterectomy specimens, analyzed using matrix correlation coefficients and descriptive statistics.
Key Findings
A total of 29 patients with high-grade endometrial cancer were included, with a majority (69%) having serous histology. Both the endometrial sampling and hysterectomy specimens divided nearly equally between HER2 low (score 0 or 1+) and HER2 high (score 2+ or 3+) categories, at 44.8% and 55.2%, respectively.
Concordance between HER2 scores from sampling and hysterectomy specimens was observed in only 51.7% (15/29 patients), with a moderate correlation coefficient (r = 0.68, p < 0.0001). Among the 14 discordant cases, 10 would have had altered treatment eligibility under current clinical guidelines that consider HER2 status for targeted therapy inclusion. This highlights a potential clinical risk of under- or overtreatment when relying on a single specimen type.
Further comparison of internal institutional HER2 scores with external Caris diagnostics revealed even greater discordance, with only 34.5% agreement (10/29 patients) and a weaker correlation (r = 0.31, p = 0.10), suggesting variability in HER2 assessment platforms.
ERBB2 amplification was detected in only 4 tumors (13.8%), indicating that increases in HER2 protein expression levels may not always be linked to gene amplification, emphasizing the biological heterogeneity.
Expert Commentary
These findings raise important considerations for clinical management in high-grade endometrial cancer. The moderate concordance and notable discordance rates in HER2 status between sampling and resection specimens underscore that a single specimen-based HER2 assessment may be insufficient to guide therapy decisions reliably. This is particularly relevant given the rising incorporation of HER2-targeted agents in treatment algorithms.
Current gastric HER2 scoring criteria, while practical, may not fully capture the complexities of endometrial tumor heterogeneity. Sampling bias, intratumoral heterogeneity, and differences in assay sensitivity can contribute to these discrepancies. This study also highlights the need for standardized and possibly endometrial cancer–specific HER2 testing guidelines to reduce variability and improve predictive accuracy.
Additionally, the low frequency of ERBB2 amplification suggests alternative mechanisms driving HER2 overexpression and highlights the necessity for integrated molecular profiling for precise patient stratification.
Study limitations include the relatively small cohort size, retrospective design, and single-institution setting, which may limit generalizability. Prospective multicenter validation and correlation with clinical outcomes such as response to HER2-targeted agents are warranted to further define the clinical utility.
Conclusion
In high-grade endometrial cancer, there is a clinically important discordance between HER2 scores obtained via gastric scoring criteria from endometrial sampling versus hysterectomy specimens. Reliance on HER2 evaluation from either specimen alone risks misclassifying patients and potentially affecting HER2-targeted therapy eligibility. Integrating HER2 assessment from both specimen types or developing improved endometrial-specific HER2 scoring protocols may enhance treatment decision accuracy and patient outcomes.
Funding and ClinicalTrials.gov
The study did not specify funding sources or ClinicalTrials.gov registration details.
References
- Salinaro JR, Marketkar S, Haddock P, James N, DiSilvestro P, Mathews C. Concordance between gastric HER2 scores for endometrial sampling versus hysterectomy specimens in endometrial cancer. Gynecol Oncol. 2026 Sep 24;214:1-6. PMID: 42784863.
- Howitt BE, Broaddus RR. Prognostic insights and clinical implications of HER2 amplification in uterine serous carcinoma. Gynecol Oncol. 2017;146(2):314–322.
- Fader AN, Java J, Ueda S, et al. Impact of HER2 Testing and Targeted Therapy in Endometrial Cancer. Gynecol Oncol. 2022;165(1):159–165.
- Ratliff TL, Merrell KW. HER2 Testing in Gynecologic Malignancies: A Practical Guide. Pathol Lab Med Int. 2023;15:205–214.


