

Highlight
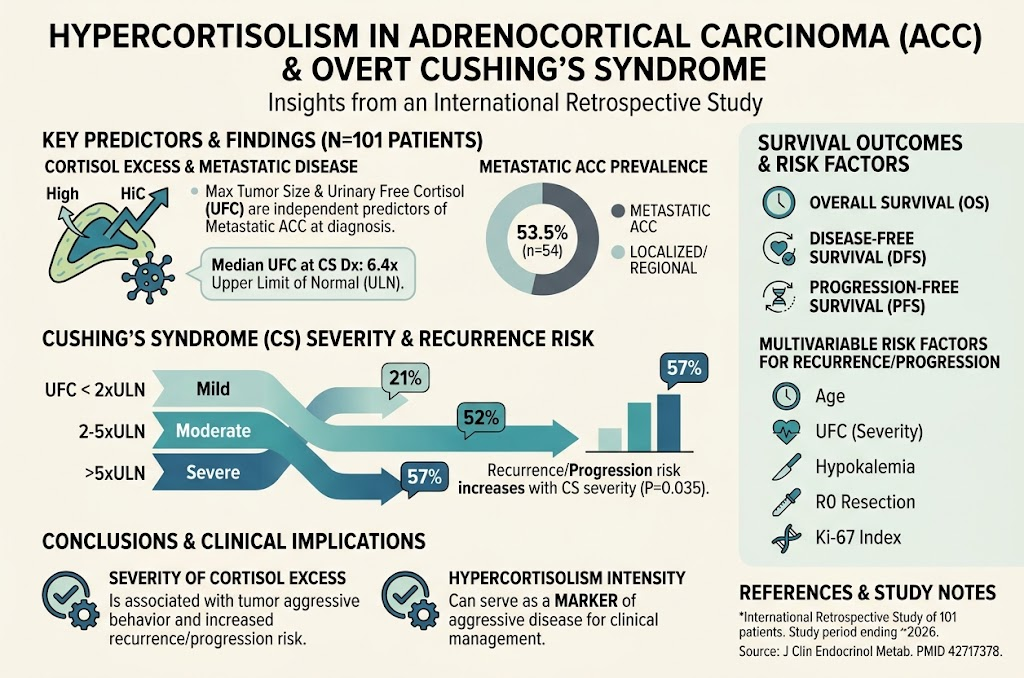
- Severity of hypercortisolism independently predicts metastatic adrenocortical carcinoma (ACC) at diagnosis.
- Higher urinary free cortisol (UFC) levels correlate with increased risk of tumor recurrence and progression.
- Adrenal tumor size and biochemical markers such as UFC and hypokalemia serve as prognostic indicators for survival outcomes.
- Multifactorial predictors including age, Ki-67 index, and surgical margins complement cortisol levels in assessing disease aggressiveness.
Study Background
Adrenocortical carcinoma (ACC) is a rare but aggressive malignancy of the adrenal cortex often associated with hormonal excess, notably hypercortisolism manifesting as Cushing’s syndrome (CS). CS due to ACC poses a significant clinical challenge owing to the dual burden of tumor aggressiveness and systemic metabolic derangements driven by cortisol excess. Although previous studies have focused on prognostic markers related to tumor pathology and stage, the relationship between cortisol levels at diagnosis and patient outcomes remains incompletely understood. Establishing whether the intensity of hypercortisolism correlates with tumor aggressiveness and survival could improve risk stratification and therapeutic decision-making in this population.
Study Design
This international retrospective cohort study analyzed 101 patients diagnosed with ACC-induced overt Cushing’s syndrome. The severity of hypercortisolism was primarily assessed by urinary free cortisol (UFC) levels relative to the upper limit of normal (ULN). Patients were stratified into mild (5x ULN) hypercortisolism groups. Metastatic status was recorded at diagnosis along with tumor size, hypokalemia presence, Ki-67 proliferation index, and surgical outcomes (R0 resection status). The primary endpoints included overall survival (OS), progression-free survival (PFS), and disease-free survival (DFS). The study further explored combined recurrence/progression outcomes in localized and metastatic ACC subgroups.
Key Findings
The median urinary free cortisol at diagnosis was 6.4 times the ULN, reflecting substantial cortisol excess. Over half of the patients (53.5%) presented with metastatic disease. Multivariate analysis identified both adrenal tumor size (odds ratio 1.02; 95% CI 1.01–1.03) and UFC levels (odds ratio 1.62; 95% CI 1.03–2.57) as independent predictors of metastatic ACC at diagnosis.
Median survival outcomes were limited, with OS at 19.4 months, DFS at 12.3 months, and PFS at 5.6 months, indicating the aggressive nature of ACC with CS. Importantly, the risk of recurrence or progression increased significantly with the severity of hypercortisolism, occurring in 21% of mild cases, 52% of moderate cases, and 57% of severe cases (P = 0.035). Although the hazard ratio for UFC predicting progression approached statistical significance (HR 1.48; 95% CI 0.97–2.24; P = 0.057), it suggests a trend that warrants further prospective study.
For the combined outcome of progression in metastatic ACC and recurrence in localized ACC, five independent predictors emerged: older age, elevated UFC, hypokalemia, complete (R0) resection status after surgery, and higher Ki-67 index. This constellation underscores the complex interplay between tumor biology, cortisol physiology, and clinical outcomes.
Expert Commentary
This comprehensive retrospective analysis provides strong evidence supporting the prognostic value of cortisol excess severity in ACC-related Cushing’s syndrome. The findings align with the biological rationale that hypercortisolism not only reflects endocrine dysfunction but may directly or indirectly promote tumor aggressiveness and metastatic potential.
While tumor size and Ki-67 have been well-established as key prognostic markers, the addition of UFC levels and hypokalemia highlights the importance of biochemical evaluation in risk stratification. Hypokalemia, a frequent consequence of mineralocorticoid receptor activation secondary to cortisol excess, may further indicate disease burden and systemic effects influencing patient prognosis.
Limitations of the study include its retrospective design and potential heterogeneity in cortisol measurement and management across international centers. Additionally, causality cannot be established, and prospective validation is needed. Future research should focus on integrating cortisol dynamics with molecular tumor profiling to tailor personalized therapeutic strategies and optimize outcomes.
Conclusion
The severity of hypercortisolism in ACC patients with Cushing’s syndrome serves as a meaningful biomarker of tumor aggression and metastatic risk. Elevated UFC levels and larger tumor size independently predict worse survival outcomes and higher recurrence rates. These data advocate for rigorous biochemical assessment at diagnosis to guide prognosis and management strategies. Multidisciplinary approaches that address both oncologic control and cortisol excess hold promise for improving patient survival and quality of life.
Reference
Araujo-Castro M, Bancos I, Detomas M, Reincke M, Kastelan D, Naglic M, Nekic AB, Biagetti B, Casteras Roman A, Cardona A, Carrerra CB, Fano MP, Lu H, Kimpel O, Kroiss M, Oettle M, Pascual-Corrales E, Guerrero-Pérez F, Hanzu FA, Rodrigo-Calvo MT, Aida CL, Menendez E, García-Centeno R, Fernández LG, Pasarón M, Gimeno PG, Morreli V, Restrepo JG, Pompey NL, García Ramos AF, Alvarez M, Iglesias P, Valdes N, Moure Rodriguez MD, Rodríguez-Jiménez B, Rodríguez RO, Recio JM, Iriarte Durán MB, Calderón SC, Tapia FG, Herrera-Martínez AD, Builes Montaño CE, Terzolo M, Torchio M, Serra G, Rivera-Martínez WA. Severity and management of hypercortisolism in patients with adrenocortical carcinoma and overt Cushing´s syndrome. J Clin Endocrinol Metab. 2026 Sep 10:dgag373. doi: 10.1210/clinem/dgag373. Epub ahead of print. PMID: 42717378.


