

Highlight
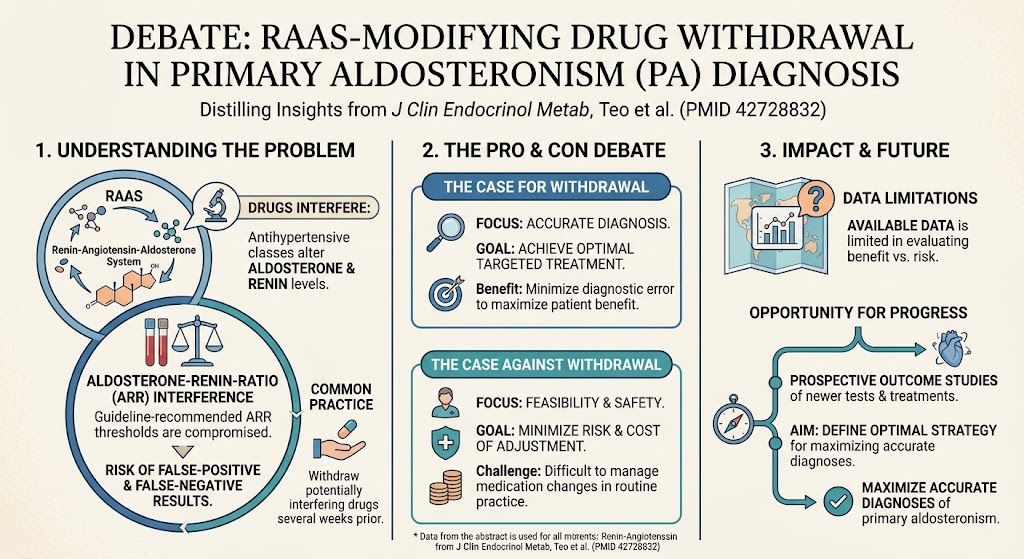
Diagnosing primary aldosteronism (PA) relies heavily on measurements affected by RAAS-modifying drugs; however, their withdrawal prior to testing remains contentious due to concerns about safety, diagnostic accuracy, and clinical feasibility.
The Pro stance advocates drug withdrawal to optimize aldosterone-renin ratio (ARR) accuracy, crucial for identifying PA and guiding targeted therapy.
The Con perspective emphasizes the risks and practical difficulties of modifying antihypertensive therapy, proposing adjusted diagnostic thresholds or alternative testing strategies.
Current evidence is limited and heterogenous, underscoring a need for prospective trials to define optimal withdrawal protocols or alternative diagnostic pathways.
Study Background and Clinical Context
Primary aldosteronism is a common cause of secondary hypertension characterized by autonomous aldosterone production leading to sodium retention, hypertension, and hypokalemia. Early and accurate diagnosis is essential because targeted treatments—surgical adrenalectomy or mineralocorticoid receptor antagonists—can significantly reduce cardiovascular morbidity and mortality compared to empiric antihypertensive therapy alone.
The first-line screening test is the aldosterone-renin ratio (ARR). It detects inappropriate aldosterone secretion by comparing plasma aldosterone concentration with plasma renin activity or concentration. However, medications that act on the renin-angiotensin-aldosterone system (RAAS)—including angiotensin-converting enzyme inhibitors (ACEi), angiotensin receptor blockers (ARBs), direct renin inhibitors, mineralocorticoid receptor antagonists (MRAs), beta-blockers, and diuretics—can alter renin and aldosterone levels, potentially confounding ARR results.
To mitigate false positives/negatives, current guidelines conventionally recommend stopping interfering medications for several weeks before testing. Despite widespread adoption, the clinical necessity and practical benefit of this approach remain debated.
Study Design and Diagnostic Considerations
The underlying debate framed here emerges from retrospective analyses, observational studies, and expert opinion rather than robust randomized controlled trials. Study populations include hypertensive subjects undergoing PA work-up, with variable inclusion criteria regarding medication use, age, comorbidities, and blood pressure control.
Key interventions under scrutiny involve withdrawing RAAS-blocking drugs for 2-6 weeks before ARR measurement versus continuing usual antihypertensive regimens with potential diagnostic adjustments. Endpoints explored include ARR diagnostic performance (sensitivity, specificity), rates of confirmed PA by confirmatory tests or adrenal vein sampling, safety outcomes (blood pressure instability, cardiovascular events during drug washout), and cost or workload implications for healthcare systems.
Key Findings and Evidence Synthesis
Impact of RAAS-Modifying Medications on ARR: RAAS inhibitors generally increase plasma renin, lowering ARR and potentially causing false-negative PA screening results. Conversely, MRAs can artificially elevate aldosterone and renin, complicating interpretation. Beta-blockers suppress renin, increasing ARR and risking false positives. Diuretics may raise renin and aldosterone variably depending on volume status.
Effect of Medication Withdrawal: Several observational studies suggest that drug withdrawal leads to ARR values that better distinguish PA from essential hypertension, improving diagnostic accuracy. For example, stopping ACE inhibitors permits renin normalization, reducing false negatives. However, no large prospective studies conclusively demonstrate that withdrawal leads to improved clinical outcomes or cost-effectiveness.
Risks and Practical Challenges: Discontinuation of antihypertensives poses risks including rebound hypertension, hypertensive emergencies, and patient discomfort, especially in those with severe or resistant hypertension or cardiovascular comorbidities. Logistical issues arise from prolonged drug washout periods, increased clinical visits, and patient non-adherence. Some studies report significant dropouts or adverse events during washout.
Alternatives and Adjusted Protocols: Some propose algorithms using adjusted ARR thresholds or alternative biomarkers without medication changes. Confirmatory testing and imaging strategies are sometimes prioritized. Recent guidelines note that while withdrawal remains ideal, continuing medications may be acceptable when washout is unsafe, with careful clinical judgment.
Expert Commentary and Guideline Perspectives
Experts highlight the tension between pursuing diagnostic precision and ensuring patient safety. Dr. J.W.M. Lenders and colleagues underscore that withdrawal is preferred for maximal accuracy but acknowledge real-world constraints. The 2023 Endocrine Society guideline advises individualized decisions based on patient risk.
Emerging diagnostic tools, such as novel biomarkers and imaging modalities or ambulatory ARR measurements, may reduce dependence on medication withdrawal. Randomized trials comparing diagnostic yields and outcomes with and without drug withdrawal are urgently needed.
Conclusion and Future Directions
Withdrawal of RAAS-modifying drugs improves biochemical detection of primary aldosteronism but entails safety risks and logistical burdens. Currently, the decision to stop these drugs before PA screening should be individualized, balancing the benefit of diagnostic clarity against potential harm and feasibility.
Large-scale prospective studies assessing patient-centered outcomes and cost-effectiveness of withdrawal versus continued medication with adjusted interpretation are critical. Advances in biomarker development and test standardization may ultimately permit accurate PA diagnosis without discontinuing essential antihypertensive therapy.
Clinicians should remain vigilant for PA in hypertensive patients and apply clinical guidelines pragmatically, considering patient preferences and comorbidities. Multidisciplinary collaboration and patient education are keys to optimizing care pathways in this evolving field.
Funding and ClinicalTrials.gov
Current debate and analysis derive from literature review and expert consensus; no specific funding or clinical trial registration was reported.
Reference
Teo AED, Pamporaki C, Lenders JWM, Brown MJ. Must RAAS-modifying drugs be withdrawn for the diagnosis of primary aldosteronism? J Clin Endocrinol Metab. 2026 Sep 12:dgag375. doi: 10.1210/clinem/dgag375. Epub ahead of print. PMID: 42728832.


