Highlight
- In a nationwide Korean cohort of over 200,000 adults with type 2 diabetes and metabolic dysfunction-associated steatotic liver disease (MASLD), empagliflozin and dapagliflozin showed comparable effectiveness in preventing severe liver complications.
- Empagliflozin demonstrated a marginally higher likelihood of regression of fatty liver disease as defined by fatty liver index (FLI) criteria compared to dapagliflozin.
- The risk of decompensated hepatic events such as ascites, variceal bleeding, hepatic failure, or liver transplantation was similar between the two agents.
- Dose stratified analyses confirmed these findings across low- and high-dose subgroups for both outcomes.
Study Background
Metabolic dysfunction-associated steatotic liver disease (MASLD), previously referred to as non-alcoholic fatty liver disease (NAFLD), has emerged as a leading cause of chronic liver disease worldwide, particularly among individuals with type 2 diabetes mellitus (T2DM). MASLD encompasses a range of liver pathologies from simple steatosis to steatohepatitis and fibrosis, which can progress to cirrhosis and hepatic decompensation. T2DM significantly increases the risk and severity of MASLD, complicating management and prognosis.
Pharmacological options directly targeting MASLD remain limited. Sodium-glucose cotransporter 2 (SGLT2) inhibitors, a class of antidiabetic agents, have shown promising effects in improving liver steatosis and biochemical markers of liver injury. Among them, dapagliflozin has phase 3 clinical trial data supporting benefit in steatohepatitis and fibrosis improvement, whereas empagliflozin’s efficacy in this context is less well-established. Given the growing use of these agents, direct comparative effectiveness data are invaluable for clinicians managing patients with coexisting T2DM and MASLD.
Study Design
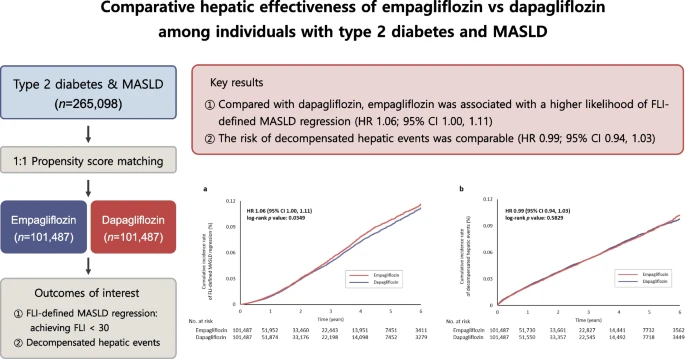
This observational study utilized a nationwide Korean claims database to form a new-user cohort of adults with type 2 diabetes and MASLD, defined by fatty liver index (FLI) values of 60 or higher, indicative of hepatic steatosis. The study identified patients initiating empagliflozin or dapagliflozin therapy between May 2016 and December 2023.
A propensity score matching approach (1:1) was applied to balance baseline demographic and clinical characteristics across treatment groups, resulting in 101,487 matched pairs with a mean age of 54.3 years and 71.3% male.
The primary outcomes were:
– Regression of MASLD defined as FLI falling below 30.
– Occurrence of decompensated hepatic events, specifically ascites, variceal bleeding, hepatic failure, or liver transplantation.
Cox proportional hazards models estimated hazard ratios (HRs) with 95% confidence intervals (CIs) comparing outcomes between empagliflozin and dapagliflozin users. Dose stratification analyses further evaluated effects in low and high dose subgroups.
Key Findings
Empagliflozin was associated with a slightly increased likelihood of MASLD regression compared to dapagliflozin, with an HR of 1.06 (95% CI 1.00 to 1.11), indicating marginal statistical significance. This suggests a subtle but potentially meaningful advantage of empagliflozin in reversing hepatic steatosis as measured by FLI.
Regarding severe liver outcomes, the risk of decompensated hepatic events was comparable between empagliflozin and dapagliflozin users (HR 0.99; 95% CI 0.94 to 1.03), indicating no significant difference in preventing or delaying advanced liver decompensation.
Dose-stratified analyses reinforced these findings. For MASLD regression, low-dose empagliflozin showed HR 1.19 (95% CI 0.77 to 1.83) and high-dose HR 1.14 (95% CI 1.01 to 1.28) compared with dapagliflozin. For decompensated hepatic events, HRs remained near unity across doses.
These results highlight that while empagliflozin may offer a modest benefit in improving hepatic fat content, both SGLT2 inhibitors are equivalently safe and effective in preventing severe hepatic complications over the study period.
Expert Commentary
This large-scale real-world study contributes important comparative data to guide treatment decisions in a population with dual metabolic and hepatic disease burden. The comparable safety profiles regarding severe liver events are reassuring given concerns about hepatic adverse effects.
The marginally better MASLD regression with empagliflozin merits further mechanistic investigation, considering possible differences in drug pharmacodynamics, metabolic effects, or hepatic tissue distribution.
Limitations include reliance on FLI as a surrogate for liver fat rather than direct imaging or biopsy, and potential residual confounding despite rigorous matching. Long-term outcomes, including fibrosis progression or cardiovascular events, warrant further scrutiny.
Current clinical guidelines recognize SGLT2 inhibitors as beneficial for patients with T2DM and MASLD, but no preferential recommendation exists between different agents based on hepatic outcomes. This study supports the clinical equivalence of empagliflozin and dapagliflozin in this regard.
Conclusion
In patients with type 2 diabetes and MASLD, both empagliflozin and dapagliflozin demonstrate similar effectiveness in preventing decompensated liver events, with a slight edge for empagliflozin in promoting fatty liver regression. These findings support flexibility in SGLT2 inhibitor selection based on overall clinical profile, tolerability, and patient preference, without compromising hepatic safety or benefit.
Further prospective, randomized trials with histological endpoints are needed to confirm these observational data and elucidate whether subtle differences in hepatic outcomes translate into meaningful clinical benefits.
Funding and Trial Registration
The study was supported by nationwide Korean healthcare data infrastructure. Further funding details were not specified.
References
Kim S, Ko HY, Hong B, Kim JH, Bea S, Bae JH, Cho YM, Chang Y, Byrne CD, Shin JY. Comparative hepatic effectiveness of empagliflozin vs dapagliflozin among individuals with type 2 diabetes and metabolic dysfunction-associated steatotic liver disease. Diabetologia. 2026 Sep 30. doi: 10.1007/s00125-026-06870-8. Epub ahead of print. PMID: 42814151.