

Highlight
1. Obstructive sleep apnea (OSA) is common in patients with type 2 diabetes (T2D), sharing key risk factors such as obesity.
2. GLP-1 receptor agonists (GLP-1RAs), known to aid weight reduction, were hypothesized to reduce the risk of developing OSA.
3. A large UK population-based study comparing GLP-1RAs with DPP-4 inhibitors (weight-neutral) found no significant difference in incident OSA risk over three years.
4. Results were consistent across multiple subgroups and sensitivity analyses, indicating no preventive effect of GLP-1RAs on OSA onset in T2D patients without prior OSA.
Study Background
Obstructive sleep apnea (OSA) is a prevalent disorder characterized by repeated upper airway obstruction during sleep, leading to intermittent hypoxia and fragmented sleep. It is highly prevalent among patients with type 2 diabetes (T2D), largely due to shared risk factors including obesity, insulin resistance, and metabolic syndrome components. OSA worsens cardiovascular risk profiles, contributing to increased morbidity and mortality in this population.
Glucagon-like peptide-1 receptor agonists (GLP-1RAs) have emerged as cornerstone therapies in T2D management for glycemic control and weight reduction. Clinical trials have shown that GLP-1RAs can reduce OSA severity in patients already diagnosed with OSA, presumably via weight loss and metabolic improvements. However, whether GLP-1RA therapy can prevent the incident development of OSA in patients with T2D remains unclear.
Study Design
This investigation utilized data from the UK Clinical Practice Research Datalink (CPRD) covering 2007–2023 in an active-comparator, new-user cohort design. Adults with T2D and a body mass index (BMI) of 30 kg/m² or higher who initiated GLP-1RA therapy were compared to those beginning dipeptidyl peptidase-4 inhibitors (DPP-4 inhibitors), chosen as an appropriate comparator due to their weight-neutral profile.
Individuals with a prior diagnosis of OSA were excluded to focus on prevention rather than treatment effects. Confounding was addressed by propensity score fine-stratification weighting within BMI strata, ensuring balance on baseline characteristics. The primary endpoint was the incidence of clinical OSA diagnosis during up to three years of follow-up, analyzed using an as-treated approach.
Key Findings
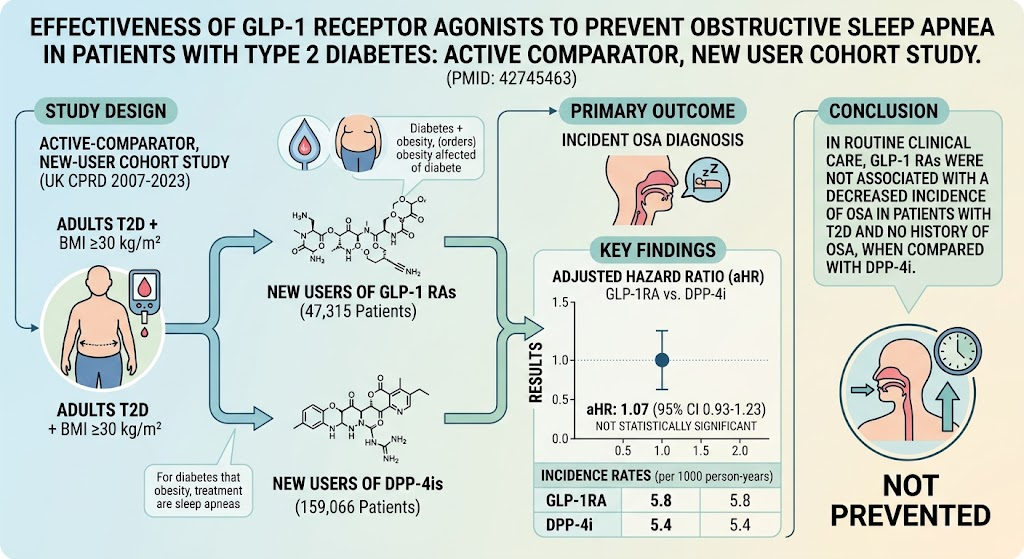
The study cohort included 47,315 GLP-1RA initiators and 159,066 DPP-4 inhibitor initiators. Baseline demographics and clinical characteristics were well balanced after weighting adjustments.
During follow-up, 612 incident cases of OSA occurred among GLP-1RA users and 1,197 cases among DPP-4 inhibitor users. The incidence rates were 5.8 and 5.4 cases per 1000 person-years, respectively.
The hazard ratio (HR) for incident OSA comparing GLP-1RA initiators to DPP-4 inhibitor initiators was 1.07 (95% confidence interval [CI] 0.93–1.23), indicating no statistically significant reduction in risk.
Importantly, subgroup analyses stratified by BMI levels, sex, and individual GLP-1RA drug types supported the primary findings, showing consistently neutral associations. Multiple sensitivity analyses also upheld the robustness of results, including those adjusting for potential unmeasured confounders and varying definitions of exposure and outcome.
Expert Commentary
This large observational study provides valuable real-world evidence concerning the potential preventive effect of GLP-1RAs on incident OSA in T2D patients with obesity. The findings suggest that despite demonstrated efficacy of GLP-1RAs in reducing OSA severity among patients already diagnosed, their initiation does not translate into primary prevention of OSA onset compared with a weight-neutral comparator.
Several considerations merit discussion. First, while GLP-1RAs induce clinically meaningful weight loss, their beneficial effects on OSA may require greater magnitude or longer duration of weight reduction, or may primarily act on symptomatic relief rather than disease prevention.
Second, incident OSA was defined by clinical diagnosis codes, which may underestimate subclinical or undiagnosed cases; however, this limitation would be expected to apply equally to both groups. Third, the study’s observational nature means residual confounding cannot be completely excluded, but rigorous propensity score methods were applied.
The findings align with current clinical guidelines that emphasize weight management and positive airway pressure therapy for OSA management but caution against expecting pharmacologic agents used in T2D treatment to prevent OSA onset.
Conclusion
In this well-powered, population-based cohort study, GLP-1 receptor agonist use in obese patients with type 2 diabetes did not reduce the risk of incident obstructive sleep apnea when compared to initiation of DPP-4 inhibitors. These findings underscore the complexity of OSA pathogenesis and suggest that GLP-1RA therapy’s benefits on OSA severity may not extend to primary prevention.
Future research should explore the biological mechanisms underpinning OSA development in T2D and evaluate whether greater or more targeted weight loss interventions could impact OSA incidence. Clinicians should continue to focus on comprehensive risk factor management and diagnostic vigilance for OSA in high-risk populations.
Funding and Clinical Trials
The study was funded by respective institutional grants; no clinical trials were registered in relation to this cohort analysis.
References
1. Peppard PE, Young T, Palta M, et al. Prospective study of the association between sleep-disordered breathing and hypertension. N Engl J Med. 2000;342:1378–1384.
2. Lam JC, Tremblay S, Brouillette RT, et al. Effect of obesity on obstructive sleep apnea syndrome risk and severity in children. Am J Respir Crit Care Med. 2015;191:1216–1220.
3. Teff KL, Grunwald GK, Gatti R, et al. Weight loss-induced improvement in obstructive sleep apnea in obese subjects is associated with decreases in leptin and insulin resistance. Diabetes. 2004;53:1859–1864.
4. Khouri C, Dell’Aniello S, Jambon Barbara C, et al. Effectiveness of GLP-1 receptor agonists to prevent obstructive sleep apnea in patients with type 2 diabetes: active comparator, new user cohort study. Am J Respir Crit Care Med. 2026 Sep 15; PMID: 42745463.
5. National Institute for Health and Care Excellence (NICE). Type 2 diabetes in adults: management. Clinical guideline [CG28]. 2022.
6. Practice guidelines for the treatment of obstructive sleep apnea. American Academy of Sleep Medicine. J Clin Sleep Med. 2016;12(11):1719-1747.


