

Highlights
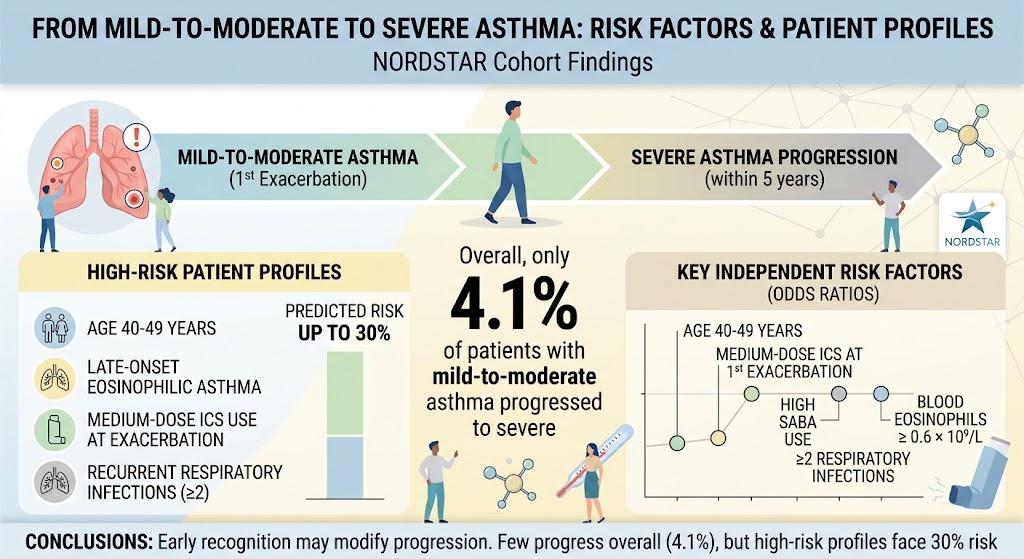
- Only 4.1% of mild-to-moderate asthma patients progress to severe asthma within 5 years after their first exacerbation, but specific high-risk profiles face up to 30% progression risk.
- Key risk factors for progression include age 40-49 years, exacerbation despite medium-dose ICS, high SABA use, recurrent respiratory infections, and elevated blood eosinophil counts.
- Biologic therapies targeting type 2 inflammation, including benralizumab, dupilumab, mepolizumab, and tezepelumab, demonstrate significant real-world efficacy in reducing exacerbations, corticosteroid use, and improving asthma control.
- Emerging evidence supports stratified treatment approaches incorporating risk assessment tools and individualized biologic therapy to modify disease trajectories and achieve multidomain remission in severe asthma.
Background
Asthma is a heterogeneous respiratory disease characterized by chronic airway inflammation, bronchial hyperresponsiveness, and varying degrees of airflow obstruction. While many patients maintain mild-to-moderate disease control, a subset progresses to severe asthma, a phenotype associated with poor quality of life, frequent exacerbations, high healthcare utilization, and corticosteroid dependence. Understanding risk factors and patient profiles that predict this progression is critical for early intervention and personalized management.
Recent advances in biologic therapies targeting type 2 (T2) inflammatory pathways have transformed severe asthma management, providing opportunities to alter disease progression and improve outcomes. However, robust population-level evidence outlining transitions from mild-to-moderate to severe asthma and integrating evolving therapeutic options remains limited.
Key Content
Progression from Mild-to-Moderate to Severe Asthma: Insights from the NORDSTAR Cohort
A landmark observational cohort study by Hansen et al. (2026) leveraged Danish national health data within the Nordic Dataset for Asthma Research (NORDSTAR) to assess progression risk following first asthma exacerbation among 99,748 adults with mild-to-moderate asthma (Am J Respir Crit Care Med 2026;212(9):1975-1987). Patients were prospectively followed for 5 years to identify development of severe asthma according to ERS/ATS criteria.
Overall, 4.1% progressed to severe asthma. Key independent baseline risk factors included:
- Age 40-49 years (OR 1.62; 95% CI 1.49–1.77), indicating a mid-life risk peak potentially reflecting late-onset asthma phenotypes
- Exacerbations despite medium-dose ICS use (OR 3.72; 95% CI 3.39–4.09), a marker of partial treatment resistance
- High short-acting beta-agonist (SABA) use (OR 1.76; 95% CI 1.64–1.90), reflecting poor symptom control or frequent bronchospasm
- ≥2 respiratory infections (OR 1.61; 95% CI 1.49–1.73), highlighting infectious triggers as progression enhancers
- Blood eosinophil count ≥0.6 × 10^9/L (OR 1.97; 95% CI 1.47–2.61), identifying a biomarker of T2 inflammation linked to airway remodeling and exacerbations
A high-risk patient profile—aged 40-49 years, with late-onset eosinophilic asthma treated with medium-dose ICS and recurrent respiratory infections—had a 30.4% 5-year progression risk.
This large-scale, real-world study provided pivotal evidence to guide risk stratification and early therapeutic interventions.
Risk Prediction Models and Biomarker Integration
In parallel, development of individualized prediction tools such as the Risk of Exacerbation in Severe Asthma (RESA) model (J Allergy Clin Immunol Pract 2026;14(7):1589-1600) offers clinicians data-driven resources incorporating age, prior exacerbations, lung function, biomarkers (blood eosinophils, FeNO), comorbidities, and treatment patterns, enhancing precision in forecasting severe exacerbations.
Advances in Therapeutic Management of Severe Asthma
Recent years have witnessed robust real-world and clinical trial evidence for biologic agents targeting key asthma inflammatory pathways, notably IL-5/IL-5R (e.g., benralizumab, mepolizumab), IL-4Rα (dupilumab), and TSLP (tezepelumab). These agents have demonstrated efficacy in reducing exacerbations, improving lung function, lowering corticosteroid burden, and achieving remission in select patient populations.
- Benralizumab: Multiple prospective and retrospective studies, including the BETREAT study (Pulmonology 2026;32(1):2702721) and BE-REAL study (Respir Med 2026;257:108854), have documented marked depletion of blood eosinophils, 70-90% reduction in annualized exacerbation rates, significant corticosteroid sparing, and improved asthma control scores in severe eosinophilic asthma (SEA) patients from diverse ethnic backgrounds (Portugal, Belgium, India, Czech Republic).
- Dupilumab: Evidence shows benefit when added to medium-dose ICS versus high-dose ICS alone, with substantial reductions in exacerbation rates and improvements in FEV1 and asthma control (Ann Allergy Asthma Immunol 2026;137(3):320-328). Real-world data also support safe de-escalation of ICS and other controllers without loss of control, facilitating personalized therapy minimization (Respir Med 2026;261:109076).
- Mepolizumab: The TYREX multicenter Spanish real-world study (Respir Med 2026;257:108849) has detailed stable clinical responses over time despite lower baseline eosinophil counts in recent biologic initiators, maintaining remission and corticosteroid reduction.
- Tezepelumab: Targeting upstream TSLP, tezepelumab has demonstrated broad efficacy across phenotypes, including non-T2 asthma, with significant exacerbation reduction, lung function improvement, and multidomain remission in real-world cohorts (Am J Respir Crit Care Med 2026;212(9):1988-1998; Respir Res 2026;27(1):157). This agent shows promise in underrepresented populations and highly refractory cases, as reported in Spanish real-world studies under early access programs.
Phenotypic Considerations and Comorbidities
Obesity, a frequent comorbidity in asthma, complicates treatment response and disease control. Recent analyses indicate that biologic therapies retain efficacy across BMI categories, with no significant difference in exacerbation reduction or treatment discontinuation rates (J Asthma 2026;63(6):723-734). Integrating comorbidity profiling is essential for holistic severe asthma management.
Optimizing Outcomes Through Multidimensional Remission
Multi-domain remission concepts, combining clinical outcomes (no exacerbations, no OCS use, ACT control), lung function, and biomarker normalization, are gaining prominence as treatment goals. Studies evaluating tezepelumab and other biologics reveal that 20-40% of patients achieve such remission states, emphasizing the feasibility and importance of deep disease control beyond symptom relief.
Expert Commentary
The NORDSTAR cohort study advances our understanding of asthma progression by quantifying absolute and relative risks in a large unselected population and identifying actionable biomarkers and clinical features. These findings underscore the necessity for early identification of high-risk patients who may benefit from intensified monitoring or early biologic intervention.
The real-world and trial-based evidence for biologics reflects a transformative era in severe asthma treatment, moving toward phenotype-endotype guided precision medicine. The integration of risk models like RESA with biomarker-driven therapeutics offers a roadmap for personalized disease modification.
Despite advances, controversies remain regarding optimal timing of biologic initiation in mild-to-moderate asthma to prevent progression, long-term impacts on airway remodeling, and cost-effectiveness in diverse healthcare settings. Furthermore, the role of infections and non-T2 pathways warrants deeper exploration to refine interventions.
Clinical guideline updates from the ERS/ATS and GINA increasingly reflect these evidences, advocating biomarker-guided approaches and multi-domain remission goals. Enhanced access to biologics and education on progression risks remain urgent for global asthma control.
Conclusion
Emerging evidence from the NORDSTAR cohort and comprehensive real-world studies clarify that progression from mild-to-moderate to severe asthma is relatively infrequent but concentrated in identifiable high-risk groups featuring age, eosinophilic inflammation, infection burden, and medication patterns. Biologic therapies targeting T2 inflammation have demonstrated substantial efficacy in improving outcomes and enabling corticosteroid reduction across phenotypes.
Enlarging the clinical toolkit to include validated risk stratification models, accessible biomarkers, and phenotypic profiling offers precision in identifying patients likely to progress and tailoring early interventions. Ongoing research is needed to determine whether early biologic therapy can arrest progression and to optimize treatment algorithms integrating patient-centric remission definitions.
This integrated approach promises to reduce asthma morbidity, enhance quality of life, and mitigate the socioeconomic burden of severe asthma.
References
- Hansen S et al. From mild-to-moderate to severe asthma: risk factors and patient profiles from the NORDSTAR cohort. Am J Respir Crit Care Med. 2026;212(9):1975-1987. PMID:42133832
- Kelly E et al. Benralizumab effectiveness in a real-world Portuguese severe eosinophilic asthma population: BETREAT study. Pulmonology. 2026;32(1):2702721. PMID:42464760
- Wechsler ME et al. Improved asthma outcomes with dupilumab plus medium-dose inhaled corticosteroids vs placebo plus high-dose inhaled corticosteroids. Ann Allergy Asthma Immunol. 2026;137(3):320-328. PMID:42178021
- Loza MJ et al. Multidomain clinical and biological remission with tezepelumab in severe asthma: a 12-month multicentre real-world study. Respir Res. 2026;27(1):157. PMID:41761198
- Chupp G et al. Tezepelumab in real-world US patients with severe asthma across phenotypes and underrepresented populations: the phase 4 PASSAGE study. Am J Respir Crit Care Med. 2026;212(9):1988-1998. PMID:42148905
- Bel EH et al. Development and Validation of the Risk of Exacerbation in Severe Asthma (RESA) Model. J Allergy Clin Immunol Pract. 2026;14(7):1589-1600. PMID:41903878
- Massanari M et al. Safety and effectiveness of benralizumab in Indian patients with severe eosinophilic asthma: results from the FAST study. Front Med (Lausanne). 2026;13:1706737. PMID:42089065
- Agusti A et al. Budesonide-glycopyrronium-formoterol fumarate dihydrate in uncontrolled asthma (KALOS and LOGOS): twin multicentre, randomised phase 3 trials. Lancet Respir Med. 2026;14(4):350-362. PMID:41692019


