

Introduction
Acute lymphoblastic leukemia (ALL) remains the most common pediatric cancer, with bone marrow transplantation (hematopoietic stem cell transplantation, HSCT) serving as a key curative approach for high-risk or relapsed cases. Despite advances, relapse following HSCT is a significant clinical challenge linked to poor prognosis. Tisagenlecleucel (tisa-cel), a CD19-directed chimeric antigen receptor T-cell (CAR-T) therapy, has emerged as a promising treatment for B-cell ALL (B-ALL) relapse after transplant. This multicenter real-world European study analyzes outcome determinants in 220 children and young adults receiving tisa-cel post-HSCT relapse, aiming to identify patient and disease factors that influence efficacy and guide clinical decision-making.
Study Population and Methods
This retrospective study includes data from 31 European pediatric oncology centers involving 220 patients with B-ALL who relapsed post-allogeneic HSCT and subsequently underwent tisa-cel CAR-T therapy. Median follow-up duration was 30 months, allowing robust assessment of long-term outcomes. Patients were stratified by donor type (matched sibling donor [MSD], mismatched donor [MMD], matched family/unrelated donor [MFD/MUD]), relapse timing post-HSCT, and disease burden at lymphodepletion measured by minimal residual disease (MRD) status or remission status.
Key Outcome Measures
The study’s primary outcomes included two-year event-free survival (EFS), overall survival (OS), and incidence of CAR-T failure—reflecting relapse or disease progression after CAR-T infusion. Secondary analyses focused on how relapse timing, donor source for transplant, and disease burden impacted these outcomes.
Results and Clinical Implications
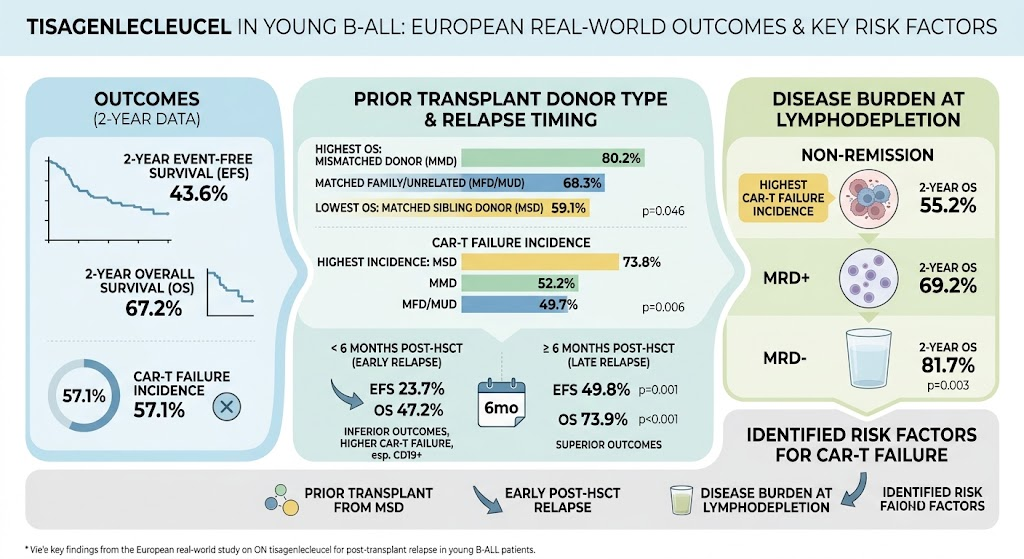
The overall two-year EFS was 43.6%, with OS at 67.2%, and a CAR-T failure incidence of 57.1%. These figures underscore the substantial risk of relapse even after advanced CAR-T therapy in this high-risk population.
Donor Type Influence: Patients initially transplanted from MSDs had a significantly lower two-year OS (59.1%) compared to those transplanted from mismatched donors (80.2%) or matched family/unrelated donors (68.3%). Additionally, CAR-T failures occurred more frequently in the MSD group (73.8%) relative to others (around 50%). The findings suggest that donor mismatch might paradoxically improve outcomes post-CAR-T, potentially due to graft-versus-leukemia effects or immunologic interplay affecting CAR-T function and disease recurrence.
Timing of Relapse: Patients relapsing early, defined as less than 6 months after HSCT, fared worse, with only 23.7% two-year EFS and 47.2% OS. In contrast, those with late relapse (≥6 months) had significantly improved survival (EFS 49.8%, OS 73.9%). Early relapse was associated with higher rates of CAR-T failure, particularly for CD19-positive relapses, indicating aggressive disease biology and poorer CAR-T response in this subgroup.
Disease Burden at Lymphodepletion: Patients’ disease status immediately prior to CAR-T infusion was a key prognostic factor. Those achieving MRD negativity had the best outcomes (81.7% two-year OS), followed by MRD-positive patients (69.2%), with the lowest survival in patients not in remission (55.2%). CAR-T failure incidence was highest among patients with active disease at lymphodepletion, highlighting the importance of minimizing residual disease to optimize CAR-T efficacy.
Discussion
This large European real-world cohort illustrates that prior transplant factors and disease characteristics critically dictate outcomes following tisa-cel therapy in pediatric B-ALL relapse post-HSCT. Early post-transplant relapse, transplantation from an MSD, and high disease burden before lymphodepletion confers increased risk of CAR-T failure. These data suggest that individualized treatment approaches, including strategies to reduce disease burden before CAR-T infusion and consideration of donor type impact, could improve survival.
Moreover, the surprisingly better outcomes observed in patients transplanted from mismatched donors may reflect immunologic mechanisms that enhance graft-versus-leukemia activity or modulate CAR-T cell persistence and function, warranting further investigation. The markedly inferior prognosis of early relapse underscores the critical need for innovative therapies and close monitoring in this group, potentially integrating CAR-T earlier or enhancing lymphodepletion protocols.
Conclusion
Tisagenlecleucel provides a valuable therapeutic option for children and young adults with B-ALL relapsing after HSCT. However, patient selection based on donor characteristics, timing of relapse, and disease burden at lymphodepletion is pivotal to optimize outcomes and reduce CAR-T failure risk. This study supports tailored treatment strategies and highlights areas requiring future research to enhance CAR-T efficacy and long-term remission rates in this vulnerable population.
Background on Tisagenlecleucel and CAR-T Therapy
Tisagenlecleucel, sold under the brand name Kymriah, is an FDA- and EMA-approved CAR-T cell therapy specifically engineered to target CD19, a surface protein expressed on B-cell leukemia cells. CAR-T therapy involves collecting patient T cells, genetically modifying them to express CARs recognizing CD19, expanding them ex vivo, and reinfusing them into the patient. These modified T cells then seek and destroy leukemia cells.
CAR-T therapy has revolutionized treatment of refractory or relapsed B-ALL, particularly in pediatric populations. However, relapse after transplant introduces complex challenges due to immune suppression, variable disease kinetics, and potential antigen loss variants.
Clinical Recommendations and Future Directions
Clinicians should carefully evaluate relapse timing and disease status before planning CAR-T therapy. Efforts to achieve MRD negativity before lymphodepletion may improve survival. Transplant donor selection, although often predetermined, should also be considered when planning post-transplant relapse management. Early relapse patients might benefit from clinical trials exploring combination immunotherapies or novel agents to overcome resistance.
Future studies should focus on uncovering mechanisms behind varied outcomes by donor type and relapse timing, optimizing conditioning regimens, and developing biomarkers predicting CAR-T response. Enhancing CAR-T cell persistence, preventing antigen loss escapes, and integrating post-CAR-T bridging therapies could further improve long-term remission.
References
Moser LM, Hutter M, Ahlmann M, Alonso-Saladrigues A, Attarbaschi A, Ayuk FA, Baldus CD, Balduzzi A, Bonig H, Bourquin JP, Buechner J, Buecklein VL, Burridge S, et al. Tisagenlecleucel for post-transplant relapse in young acute lymphoblastic leukemia patients: European real-world determinants of outcome. Leukemia. 2026 Aug 31. PMID: 42675139. Available from: https://pubmed.ncbi.nlm.nih.gov/42675139/


