Highlight
1. Left atrial appendage closure (LAAC) shows a significant reduction in nonprocedural bleeding compared to oral anticoagulation in atrial fibrillation (AF) patients at standard-to-moderate bleeding risk.
2. Despite an overall stroke rate comparable between LAAC and oral anticoagulation, ischemic stroke incidence was higher with LAAC.
3. The benefit of LAAC in bleeding risk reduction is not demonstrated in patients with high bleeding risk.
4. LAAC is positioned as a complement to, rather than an equivalent substitute for, oral anticoagulation in stroke prevention for eligible patients.
Study Background
Atrial fibrillation (AF) affects millions worldwide and significantly increases the risk of ischemic stroke. The left atrial appendage (LAA) is the predominant site of thrombus formation in nonvalvular AF, with approximately 90% of thrombi arising therein. Oral anticoagulation (OAC) with vitamin K antagonists or direct oral anticoagulants (DOACs) remains the standard prophylactic treatment to prevent stroke in AF. However, OAC carries bleeding risks, which complicates management, especially in patients with bleeding predispositions or contraindications.
Left atrial appendage closure (LAAC), a percutaneous catheter-based intervention, mechanically excludes the LAA from systemic circulation to prevent thromboembolism. Given the burden of stroke and bleeding complications associated with OAC, LAAC offers a potential alternative or adjunctive strategy for stroke prevention in selected patients.
Study Design
This systematic review and meta-analysis synthesized data from six randomized controlled trials (2014-2026), involving 7028 patients from 358 international sites across North America, Europe, and Asia. All trials compared percutaneous LAAC with oral anticoagulation in nonvalvular AF patients.
Among the six studies, two trials used warfarin as the comparator, while four trials employed direct oral anticoagulants. The patient cohorts varied, including predominantly anticoagulation-eligible populations with low prior stroke prevalence, two trials focusing on high bleeding risk patients, and one post-ablation trial assessing outcomes after catheter ablation for AF.
Primary endpoints included stroke (overall and ischemic), major bleeding (nonprocedural), and all-cause mortality. The analysis applied random-effects models pooling cumulative incidence outcomes as odds ratios with 95% confidence intervals, complemented by prediction intervals, prespecified subgroup analyses (based on bleeding risk and anticoagulation eligibility), and trial sequential analysis to appraise the sufficiency of accumulated evidence. Risk of bias was evaluated with the Cochrane Risk of Bias 2 tool.
Key Findings
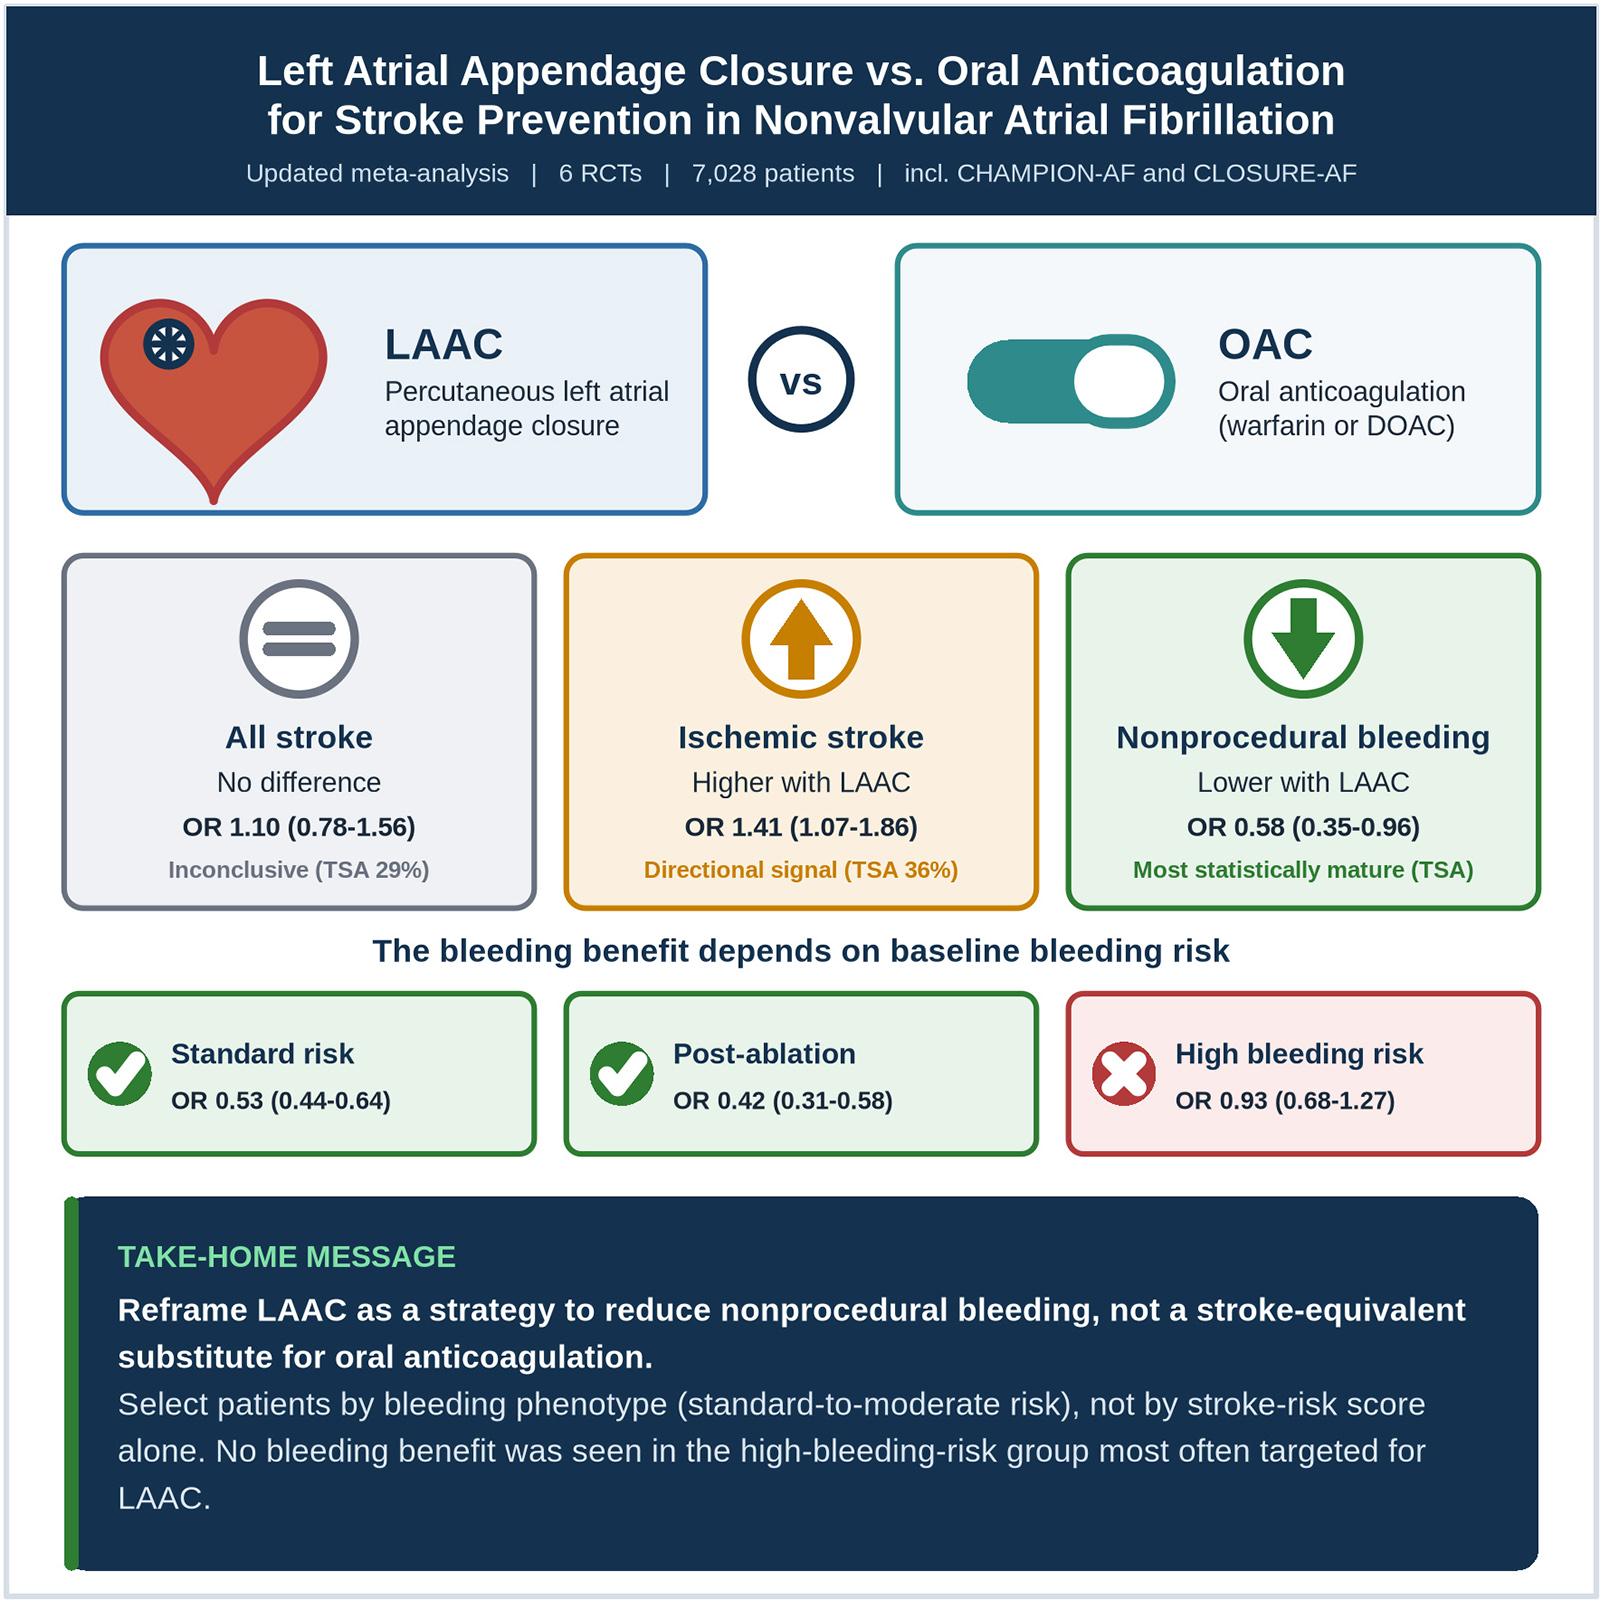
The meta-analysis revealed that the overall stroke incidence did not differ significantly between LAAC and oral anticoagulation groups (odds ratio [OR], 1.10; 95% confidence interval [CI], 0.78-1.56), indicating comparable efficacy in stroke prevention.
However, ischemic stroke was more frequent among patients undergoing LAAC (OR, 1.41; 95% CI, 1.07-1.86), though this result did not meet the required information size for definitive conclusions. This raised concerns regarding the potential ischemic stroke risk elevation associated with LAAC attributable to procedural or device-related factors and incomplete LAA sealing.
Nonprocedural (spontaneous) bleeding events occurred less frequently with LAAC compared to oral anticoagulation (OR, 0.58; 95% CI, 0.35-0.96). This safety benefit was most apparent in populations at standard-to-moderate bleeding risk and in post-ablation patients, but notably not in those characterized as high bleeding risk. The evidence for bleeding reduction was the only outcome reaching a sufficient information size, underscoring the robust benefit of LAAC regarding bleeding complications in selected patient populations.
All-cause mortality rates showed no significant difference between LAAC and OAC arms.
Subgroup analyses highlighted that the bleeding advantage of LAAC did not extend to patients at high bleeding risk, who remain a challenging group for stroke prevention optimization.
Expert Commentary
This comprehensive meta-analysis enhances the understanding of the nuanced balance between stroke prevention and bleeding risk management in AF. The finding that LAAC reduces nonprocedural bleeding without overall stroke reduction is consistent with the mechanistic principle whereby mechanical closure eliminates sources of LAA thrombus but does not influence other stroke mechanisms such as embolism from other atrial or vascular sources.
The higher ischemic stroke signal with LAAC needs consideration of procedural expertise, device selection, and patient anatomy. Notably, earlier generation devices and operators’ learning curves may have impacted results. Current guidelines continue to recommend OAC as the first-line therapy for stroke prevention in AF, with LAAC reserved for patients with contraindications or elevated bleeding risk.
Limitations of the analysis include variability in anticoagulant types (warfarin versus DOACs), heterogeneity in patient populations, and follow-up durations. Moreover, procedural complications and device-related thrombi, not fully detailed here, remain important clinical concerns warranting further research and refinement of patient selection criteria.
Conclusion
In sum, LAAC offers a compelling bleeding risk reduction advantage in anticoagulation-eligible AF patients at standard to moderate bleeding risk but does not confer a stroke prevention benefit equivalent to oral anticoagulation. These findings reinforce the role of LAAC as an adjunct or alternative strategy primarily for patients where bleeding risk or anticoagulation contraindication precludes optimal OAC use.
Future research should focus on optimizing procedural techniques, refining patient selection, and long-term comparative effectiveness to better delineate LAAC’s role in integrated stroke prevention strategies for atrial fibrillation.
Funding and Registration
The systematic review and meta-analysis were registered with PROSPERO (Unique identifier: CRD420261370546). Funding sources were not explicitly stated in the published abstract.
References
1. Pekyi-Boateng PK, Mahadevan A, Frimpong SK, et al. Updated Meta-Analysis of Left Atrial Appendage Closure Versus Oral Anticoagulation to Prevent Stroke in Atrial Fibrillation. Stroke. 2026 Oct 1; PMID: 42817893.
2. Hindricks G, Potpara T, Dagres N, et al. 2020 ESC Guidelines for the diagnosis and management of atrial fibrillation developed in collaboration with the EACTS. Eur Heart J. 2021;42(5):373-498.
3. Holmes DR Jr, Kar S, Price MJ, et al. Prospective randomized evaluation of the Watchman Left Atrial Appendage Closure device in patients with atrial fibrillation versus long-term warfarin therapy: the PROTECT AF trial. J Am Coll Cardiol. 2009;54(22):1837-1844.
4. Reddy VY, Doshi SK, Sievert H, et al. Percutaneous left atrial appendage closure vs warfarin for atrial fibrillation: a randomized clinical trial. JAMA. 2014;312(19):1988-1998.
5. January CT, Wann LS, Calkins H, et al. 2019 AHA/ACC/HRS Focused Update of the 2014 Guideline for the Management of Patients With Atrial Fibrillation. Circulation. 2019;140(2):e125-e151.
Additional references are available upon request or in full publication details linked to clinical trial data.