

Highlight
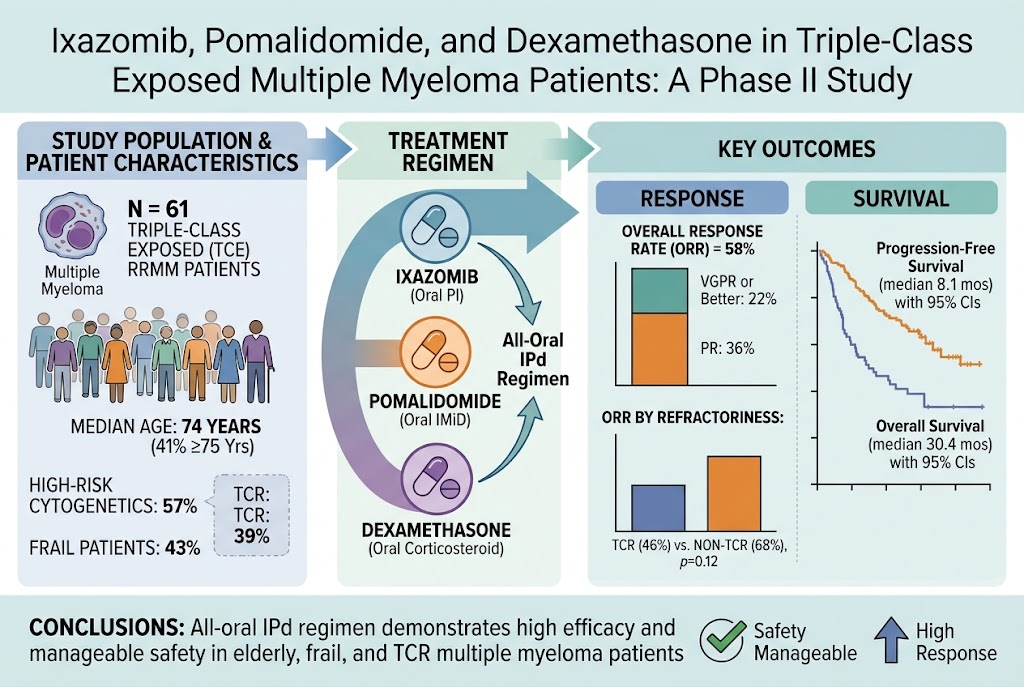
- An all-oral regimen of ixazomib, pomalidomide, and dexamethasone (IPd) was evaluated in a triple-class exposed (TCE) relapsed/refractory multiple myeloma (RRMM) patient cohort.
- The study enrolled primarily elderly and frail patients, with a high-risk cytogenetic profile and substantial refractoriness to standard agents.
- Despite the heavily pretreated population, the treatment showed an overall response rate (ORR) of 58% with a manageable safety profile.
- Median progression-free survival (PFS) was 8.1 months and overall survival (OS) was 30.4 months, suggesting meaningful clinical benefit.
Study Background
Multiple myeloma (MM) remains an incurable hematologic malignancy characterized by clonal plasma cell proliferation. Therapeutic advances employing proteasome inhibitors, immunomodulatory drugs (IMiDs), and monoclonal antibodies have significantly improved patient outcomes. However, many patients become exposed to or refractory against all three primary drug classes early in their disease course, defining the triple-class exposed (TCE) or triple-class refractory (TCR) populations. The prognosis for these heavily pretreated patients is poor, with limited effective treatment options. There is an unmet need for oral regimens that combine efficacy with tolerability, especially for elderly and frail patients who may not tolerate intensive therapies.
Study Design
This investigator-initiated, open-label, single-arm, phase II multicenter trial assessed the safety and efficacy of the all-oral regimen of ixazomib (an oral proteasome inhibitor), pomalidomide (a third-generation IMiD), and dexamethasone in TCE RRMM patients. The enrollment period spanned from March 1, 2021, to March 17, 2024, with 61 patients included. Key inclusion criteria involved prior exposure to bortezomib, lenalidomide, and daratumumab. The primary endpoint was overall response rate (ORR), with secondary endpoints including progression-free survival (PFS), overall survival (OS), and safety profile. Patients’ demographic and disease characteristics such as age, cytogenetic risk, and frailty status were collected to assess subgroup responses and tolerability.
Key Findings
The median age was 74 years (range 53–89), with 41% aged 75 or older and 43% classified as frail, reflecting a real-world high-risk population. Cytogenetic high-risk features (t(4;14), t(14;16), +1q21, del17p) were present in 57% of patients. Refractoriness rates to bortezomib, lenalidomide, and daratumumab were 51%, 85%, and 96%, respectively, with 39% exhibiting triple-class refractory disease.
Efficacy results demonstrated an overall response rate (ORR) of 58%, including 22% achieving very good partial response (VGPR) or better. The ORR among triple-class refractory patients was 46% versus 68% in non-TCR patients, which did not reach statistical significance (p=0.12). The median progression-free survival was 8.1 months (95% CI, 3.9–12.3), and median overall survival was 30.4 months (95% CI, 21.5–39.4), indicating a survival benefit despite aggressive disease biology.
Safety was manageable with 97% experiencing at least one treatment-emergent adverse event (TEAE) and 67% experiencing grade ≥3 TEAEs. Importantly, the rate of grade ≥3 adverse events was not significantly higher in frail versus non-frail patients (p=0.43), underscoring the regimen’s tolerability even in vulnerable populations.
Expert Commentary
The IPd regimen represents a significant advancement for TCE RRMM patients, particularly given the oral administration convenience and the regimen’s efficacy in a heavily pretreated cohort often underrepresented in clinical trials. This study supports the potential of combining ixazomib with pomalidomide and dexamethasone to overcome resistance mechanisms, although ORR differences between TCR and non-TCR patients suggest that refractoriness remains a clinical challenge.
Limitations of the study include its single-arm design and relatively small sample size, which preclude direct efficacy comparison with other regimens. Additionally, the open-label nature may introduce bias in toxicity reporting. Nonetheless, the inclusion of elderly and frail patients strengthens the generalizability to real-world clinical settings.
Future research should evaluate combination strategies incorporating novel agents such as CELMoDs, bispecific antibodies, or CAR T-cell therapies to further improve outcomes in triple-class refractory cohorts. Mechanistically, ixazomib’s oral proteasome inhibition complements pomalidomide’s immunomodulatory effects, potentially enhancing antitumor immune responses.
Conclusion
This phase II trial demonstrates that an all-oral combination of ixazomib, pomalidomide, and dexamethasone offers a viable and effective treatment option for TCE RRMM patients, including those with triple-class refractory disease, elderly age, and frailty. The regimen balances efficacy with a manageable safety profile, aligning with the needs of patients who are often excluded from intensive treatment modalities. These findings support the broader incorporation of oral regimens in relapsed/refractory multiple myeloma management and highlight the importance of personalized therapy based on patient fitness and disease characteristics.
Funding and Clinical Trial Registration
This investigator-initiated study was registered under NCT04790474. Specific funding sources were not disclosed in the abstract.
References
1. Shragai T, Lavi N, Vaxman I, et al. Ixazomib, pomalidomide and dexamethasone in triple-class exposed multiple myeloma patients – a phase II study. Haematologica. 2026 Sep 10. doi:10.3324/haematol.2026.42719971
2. Kumar SK, et al. Relapsed multiple myeloma: Updated therapeutic strategies and future directions. Blood Rev. 2021;47:100777.
3. Moreau P, et al. Oral Ixazomib for the Treatment of Multiple Myeloma. Expert Opin Pharmacother. 2017;18(14):1533-1545.
4. Dimopoulos MA, et al. Pomalidomide plus low-dose dexamethasone in relapsed and refractory multiple myeloma patients: A European Phase II Study. Leukemia. 2012;26(8):1914-1920.
5. Rajkumar SV. Treatment of multiple myeloma. Nat Rev Clin Oncol. 2011;8(2):71-79.


