

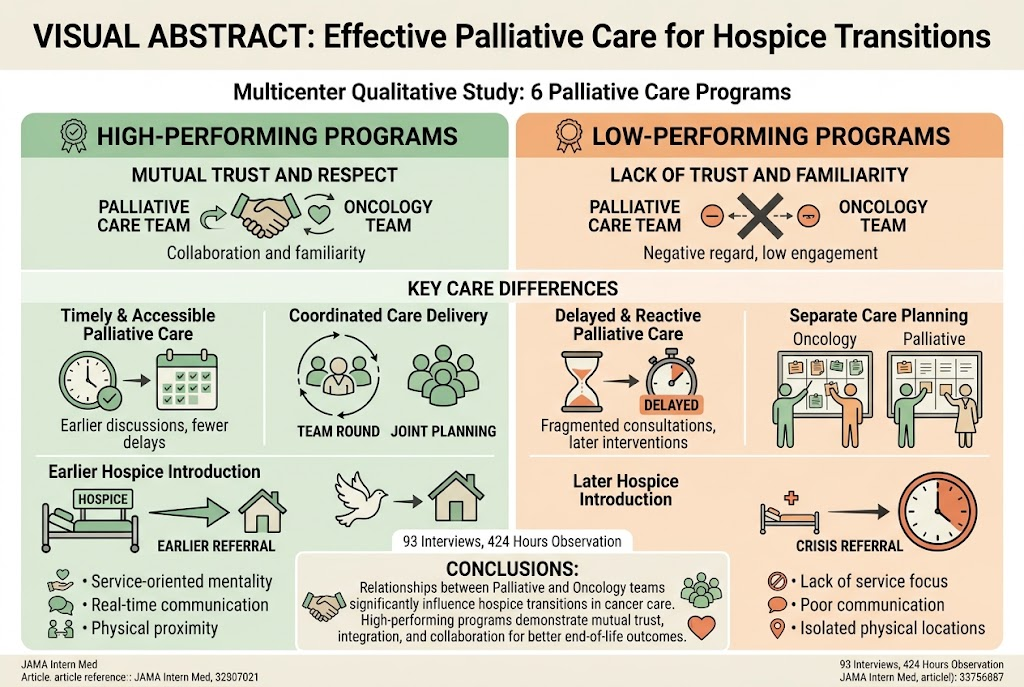
Highlights
- Mutual trust and active collaboration between palliative care and oncology teams significantly enhance timely hospice utilization among cancer patients.
- Integrated palliative care models, including structured rehabilitation, symptom monitoring, and early advance care planning, improve quality of life and end-of-life care outcomes.
- Family caregiver support interventions, grief counseling, and psychosocial therapies contribute importantly to holistic hospice care and reduce caregiver burden.
- System-level innovations such as algorithm-driven referrals and decision aids improve palliative care access and advance care documentation.
Background
Cancer remains a leading cause of morbidity and mortality worldwide, where advanced disease stages necessitate effective palliative interventions to optimize quality of life and align care with patients’ preferences. Hospice care, as a critical component of palliative management, offers a comprehensive approach focusing on symptom alleviation and psychosocial support. However, variability in hospice use among cancer patients persists, influenced by programmatic, relational, and systemic factors. Understanding these determinants is vital to ensuring equitable, high-quality end-of-life care.
Key Content
1. Programmatic and Relational Factors Affecting Hospice Transitions
A multicenter qualitative study across six U.S. palliative care programs (Hua et al., 2026) revealed that programs with high hospice utilization demonstrated collaborative, trust-based relationships between oncology and palliative care teams. These positive dynamics were characterized by intentional relationship-building, physical proximity, real-time communication, and a service-oriented mentality, leading to enhanced access and timeliness of palliative care and earlier hospice introduction. Conversely, low-performing programs exhibited mistrust and negative attitudes, impeding hospice transitions.
2. Structured Rehabilitation and Symptom Management in Terminal Cancer
Terminal cancer patients benefit from structured rehabilitation programs that maintain activities of daily living and reduce psychological distress (Ishikura et al., 2026). Randomized controlled trials (RCTs) demonstrated superior physical function preservation and quality of life with structured versus unstructured rehabilitation approaches, underscoring the importance of functional maintenance in palliative care settings.
3. Psychosocial and Spiritual Interventions
Psychological distress in patients and caregivers can be mitigated through grief counseling and meaning-centered psychotherapy. Grief counseling for family members of terminal cancer patients significantly reduces distress, depression, and anxiety (Liu et al., 2025). Brief nurse-delivered meaning-centered psychotherapy administered in home care settings shows high feasibility and efficacy in improving existential well-being and psychosocial outcomes in advanced cancer patients (Kim et al., 2025).
4. Family Caregiver Support and Role Adoption
Caregiver-focused interventions such as the “PalliActive Caregivers” program enhance role adoption, perceived social support, and quality of life among family caregivers (Martinez et al., 2025). Meta-syntheses highlight that family caregivers face emotional and logistical challenges in home-based hospice care, necessitating integrated formal and informal support systems to optimize caregiving quality and patient outcomes (Nguyen et al., 2025).
5. Integration of Patient-Reported Outcome Measures (PROMs)
PROMs such as the Integrated Palliative Care Outcome Scale (IPOS) and Edmonton Symptom Assessment Scale (ESAS) are commonly utilized to assess multidimensional palliative care outcomes. Despite implementation barriers including frailty and workflow integration challenges, these tools facilitate patient-centered quality monitoring and service improvement (Jones et al., 2026).
6. Advance Care Planning and Algorithm-Based Referral Systems
Advance care planning (ACP) interventions combining patient-facing decision aids and clinician communication training increase ACP documentation rates among older adults with advanced cancer, representing a scalable model for improving goal-concordant care (Smith et al., 2025). Similarly, embedding algorithm-driven defaults with accountable justification in electronic health records significantly enhances specialty palliative care referrals and reduces aggressive end-of-life systemic therapy (Patel et al., 2025).
7. Integrated Palliative Care Models
Randomized studies demonstrate that integrated palliative care encompassing pain management, psychological support, and family involvement leads to improved quality of life, reduced anxiety and depression, and higher family satisfaction in advanced cancer patients (Chen et al., 2025). Additionally, stepped-care models that tailor palliative care intensity based on patient-reported quality of life maintain efficacy while optimizing resource utilization (Thompson et al., 2024).
Expert Commentary
The heterogeneity in hospice utilization among palliative care programs underscores the pivotal role of interprofessional relationships and institutional cultures. Trust, respect, and familiarity foster timely hospice discussions and smoother care transitions. The integration of structured rehabilitation and psychosocial interventions addresses holistic patient needs, reinforcing the biopsychosocial framework of palliative care.
Implementation of PROMs and digital tools, alongside algorithm-based referral strategies, holds promise for standardizing and expanding access to palliative care services. However, barriers such as clinician workload, patient frailty, and technological integration need addressing through policy support and workflow redesign.
Family caregivers represent a crucial axis in hospice care delivery; interventions enhancing caregiver competence and social support are vital for sustainable home-based hospice models. Cross-cultural aspects, grief counseling acceptance, and tailored therapy approaches require further research to optimize inclusivity and efficacy.
From a mechanistic standpoint, collaborative team dynamics likely improve communication quality, patient trust, and early identification of hospice-appropriate candidates, collectively facilitating better end-of-life outcomes. The biological rationale for rehabilitation maintaining functional reserve aligns with improved psychosocial well-being, further supporting early palliative integration.
Conclusion
Effective hospice transitions in cancer care rely on multifaceted programmatic, relational, and clinical factors. Strengthening oncology-palliative care relationships, implementing structured rehabilitation and psychosocial interventions, and leveraging digital innovations and decision algorithms improve patient-centered outcomes. Supporting family caregivers enhances home hospice feasibility and experience. Future research should focus on scalable interventions, integration of PROMs into routine care, and culturally sensitive psychosocial strategies to promote equitable, high-quality hospice care for all cancer patients.
References
- Hua M, Cid M, Barshied C, Shelton RC, Hu G, Stekl N, Brill C, Carey EC, Morrison RS. Effective Palliative Care for Hospice Transitions. JAMA Intern Med. 2026 Sep 14. PMID: 42734951.
- Ishikura M, et al. Efficacy of a structured rehabilitation program for patients with terminal cancer: A multicenter randomized controlled trial. Cancer. 2026 Jun 15;132(12):e70485. PMID: 42304645.
- Liu Y, et al. Effect of grief counseling on psychological distress among family members of patients with terminal tumors: A randomized controlled trial. World J Psychiatry. 2025 Oct 19;15(10):110643. PMID: 41112630.
- Kim S, et al. A pragmatic randomized controlled pilot trial of brief meaning-centered psychotherapy in home care. Cancer. 2025 Sep 15;131(18):e70082. PMID: 40946175.
- Martinez R, et al. Efficacy of the PalliActive Caregivers intervention for caregivers of patients with cancer in palliative care: A randomized controlled trial. BMC Palliat Care. 2025 Sep 29;24(1):235. PMID: 41024054.
- Nguyen T, et al. Family experiences in home-based hospice care for patients with terminal cancer: A meta-synthesis. JMIR Cancer. 2025 Jun 19;11:e71596. PMID: 40537084.
- Jones D, et al. Patient-reported outcome measures in palliative care: A systematic review to inform health policy. Health Policy. 2026 Oct;172:105688. PMID: 42419150.
- Smith AC, et al. An intervention to increase advance care planning among older adults with advanced cancer: A randomized clinical trial. JAMA Netw Open. 2025 May 1;8(5):e259150. PMID: 40343696.
- Patel S, et al. Algorithm-based palliative care in patients with cancer: A cluster randomized clinical trial. JAMA Netw Open. 2025 Feb 3;8(2):e2458576. PMID: 39982729.
- Chen L, et al. Integrated palliative care improves quality of life among advanced cancer patients: A randomized study. BMC Palliat Care. 2025 Jun 7;24(1):162. PMID: 40483417.
- Thompson R, et al. Stepped palliative care for patients with advanced lung cancer: A randomized clinical trial. JAMA. 2024 Aug 13;332(6):471-481. PMID: 38824442.


