

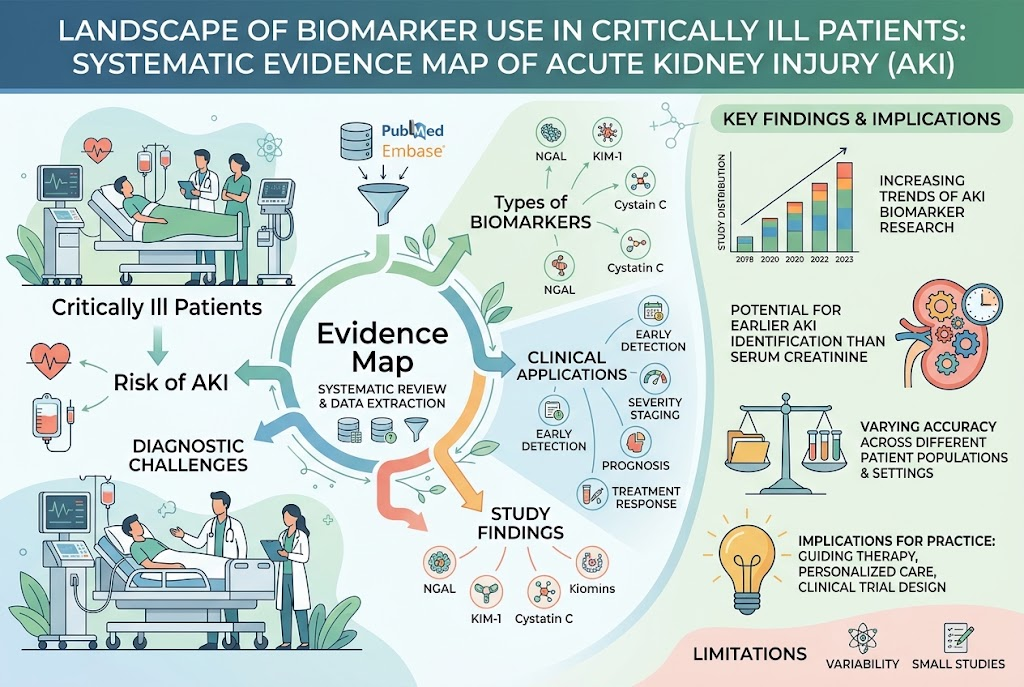
Highlight
1. Extensive clinical evidence exists for novel biomarkers predicting and diagnosing acute kidney injury (AKI) in critically ill patients, with the majority derived from cohort studies in adult populations.
2. Biomarker applications predominantly focus on mixed critical illness, cardiac surgery, and sepsis contexts, underlining key clinical scenarios for AKI risk.
3. Evidence maps reveal a gap between biomarker accuracy studies and practical interventional trials, highlighting the need for management and enrichment trials.
4. Implementation strategies are emerging, particularly for surgical patients and those receiving multiple nephrotoxic agents, to enhance early AKI detection and intervention.
Study Background
Acute kidney injury (AKI) remains a common and severe complication among critically ill patients, often leading to increased morbidity, mortality, prolonged hospital stays, and long-term renal dysfunction. Despite its clinical importance, early recognition and accurate diagnosis of AKI remain challenging due to the limitations of traditional markers such as serum creatinine and urine output. Recent advances have identified numerous novel biomarkers that reflect early kidney injury and pathophysiological changes before overt functional impairment. Mapping the landscape of evidence for these biomarkers is crucial to guide clinical adoption, optimize patient monitoring, and improve outcomes.
Study Design
The current work presents a systematic evidence mapping review based on a comprehensive literature screening of PubMed/MEDLINE and Embase databases. A total of 6805 records were screened, with 1116 eligible studies included. These studies comprise clinical trials and observational cohort studies focusing on novel kidney injury biomarkers in critically ill adult and pediatric populations. The majority (78.6%) included adults, and most studies (93.3%) employed a cohort design. The investigations span clinical contexts such as mixed critical illness, cardiac surgery, and sepsis, the three most frequently studied scenarios where AKI risk is high.
Key Findings
Nearly 850 biomarker studies related to AKI prediction were identified, supplemented by 647 studies evaluating prognostic outcomes and 109 studies focused on etiology diagnosis. A smaller number of studies address clinical trial enrichment (n=6) and direct AKI management (n=12), underscoring an important translational gap between biomarker discovery and therapeutic application.
Adult populations dominate the dataset, yet evidence also spans pediatric and mixed populations, noting a universal clinical challenge. Cohort studies prevail over randomized trials, reflecting the current emphasis on validation of predictive accuracy over interventional efficacy.
The studies predominantly evaluated biomarkers such as neutrophil gelatinase-associated lipocalin (NGAL), kidney injury molecule-1 (KIM-1), interleukin-18 (IL-18), and tissue inhibitor of metalloproteinases-2 with insulin-like growth factor-binding protein 7 ([TIMP-2]*[IGFBP7]). These biomarkers show variable but generally high sensitivity and specificity for early AKI prediction, often outperforming traditional markers.
Clinical contexts include:
– Mixed critically ill cohorts where heterogeneous insults require broad surveillance.
– Cardiac surgery, a high-risk setting due to ischemia-reperfusion injury and nephrotoxic exposures.
– Sepsis, where AKI pathophysiology is complex and multifactorial.
Practical implementation strategies are emerging for the high-risk surgical and nephrotoxin-exposed patients. Biomarkers facilitate early risk stratification and informed nephrotoxin stewardship to potentially prevent progression.
However, the paucity of clinical trials demonstrating how biomarker-guided interventions improve outcomes reflects a critical gap. Most studies focus on diagnostic accuracy rather than impact on therapeutic decision-making or AKI mitigation.
Expert Commentary
Dr. John A. Kellum, a leading authority on AKI biomarkers, notes: “While biomarkers have revolutionized our ability to detect early kidney injury, the challenge remains to translate this into actionable strategies that change patient management and improve outcomes. The current evidence mapping highlights where our strongest data exists and where future trials must focus—particularly interventional studies leveraging biomarker data to guide care.”
Clinical guidelines increasingly acknowledge biomarkers’ roles for surveillance but remain cautious regarding routine clinical use until prospective interventional evidence accrues. The biological plausibility of damage biomarkers reflecting cellular stress and injury prior to function loss is well-established, yet variability in biomarker kinetics and heterogeneity of critical illness complicate interpretation.
Conclusion
This systematic evidence map offers a comprehensive overview of the biomarker landscape in AKI among critically ill patients, demonstrating robust diagnostic and prognostic data particularly in adult and surgical populations. Nevertheless, there is a pressing need for well-designed practical trials to bridge the gap between biomarker accuracy and clinical benefit. Future research should prioritize enrichment strategies and management protocols that incorporate biomarkers to tailor early interventions, especially renal protective strategies in high-risk groups. Implementation of these approaches holds promise to improve kidney outcomes and reduce the burden of AKI in critical care settings.
Funding and ClinicalTrials.gov
No specific funding sources were reported in the original mapping review. Clinical trials on AKI biomarkers can be explored at ClinicalTrials.gov using keywords such as “acute kidney injury,” “kidney biomarkers,” and “critical illness.”
References
1. Kane-Gill SL, Boyer KM, Akcan Arikan A, et al. Landscape of Biomarker Use in Critically Ill Patients: Systematic Evidence Map of Acute Kidney Injury and Implications for Practice. Crit Care Med. 2026 Sep 11. PMID: 42725835.
2. Kellum JA, Lameire N. Diagnosis, evaluation, and management of acute kidney injury: a KDIGO summary (Part 1). Crit Care. 2013;17(1):204.
3. Bihorac A, et al. Validation of cell-cycle arrest biomarkers for acute kidney injury using clinical adjudication. Am J Respir Crit Care Med. 2014;189(8):932-9.
4. Sawhney S, Fluck N, Marks A, et al. Acute kidney injury recovery patterns and subsequent risk of CKD: an analysis of nationwide data. Am J Kidney Dis. 2020;76(2):197–205.

