

Introduction
Heart failure with reduced ejection fraction (HFrEF) is a progressive condition characterized by the heart’s diminished ability to pump blood effectively, often leading to debilitating symptoms and increased mortality.
Cardiac resynchronization therapy (CRT) has emerged as a proven intervention that can improve cardiac function and patient outcomes by coordinating the contraction of the ventricles using a specialized pacemaker. However, patients with coexisting permanent atrial fibrillation (AF)—an irregular and often rapid heart rhythm originating in the atria—derive less benefit from CRT. AF can cause irregular ventricular rates, reducing the degree of ventricular synchrony achievable by CRT devices.
One therapeutic strategy proposed to enhance CRT efficacy in this patient population is atrioventricular node ablation (AVNA). This catheter-based procedure destroys the conduction tissue between the atria and ventricles, rendering the ventricles dependent on the pacemaker for rhythm control, thus potentially maximizing CRT delivery.
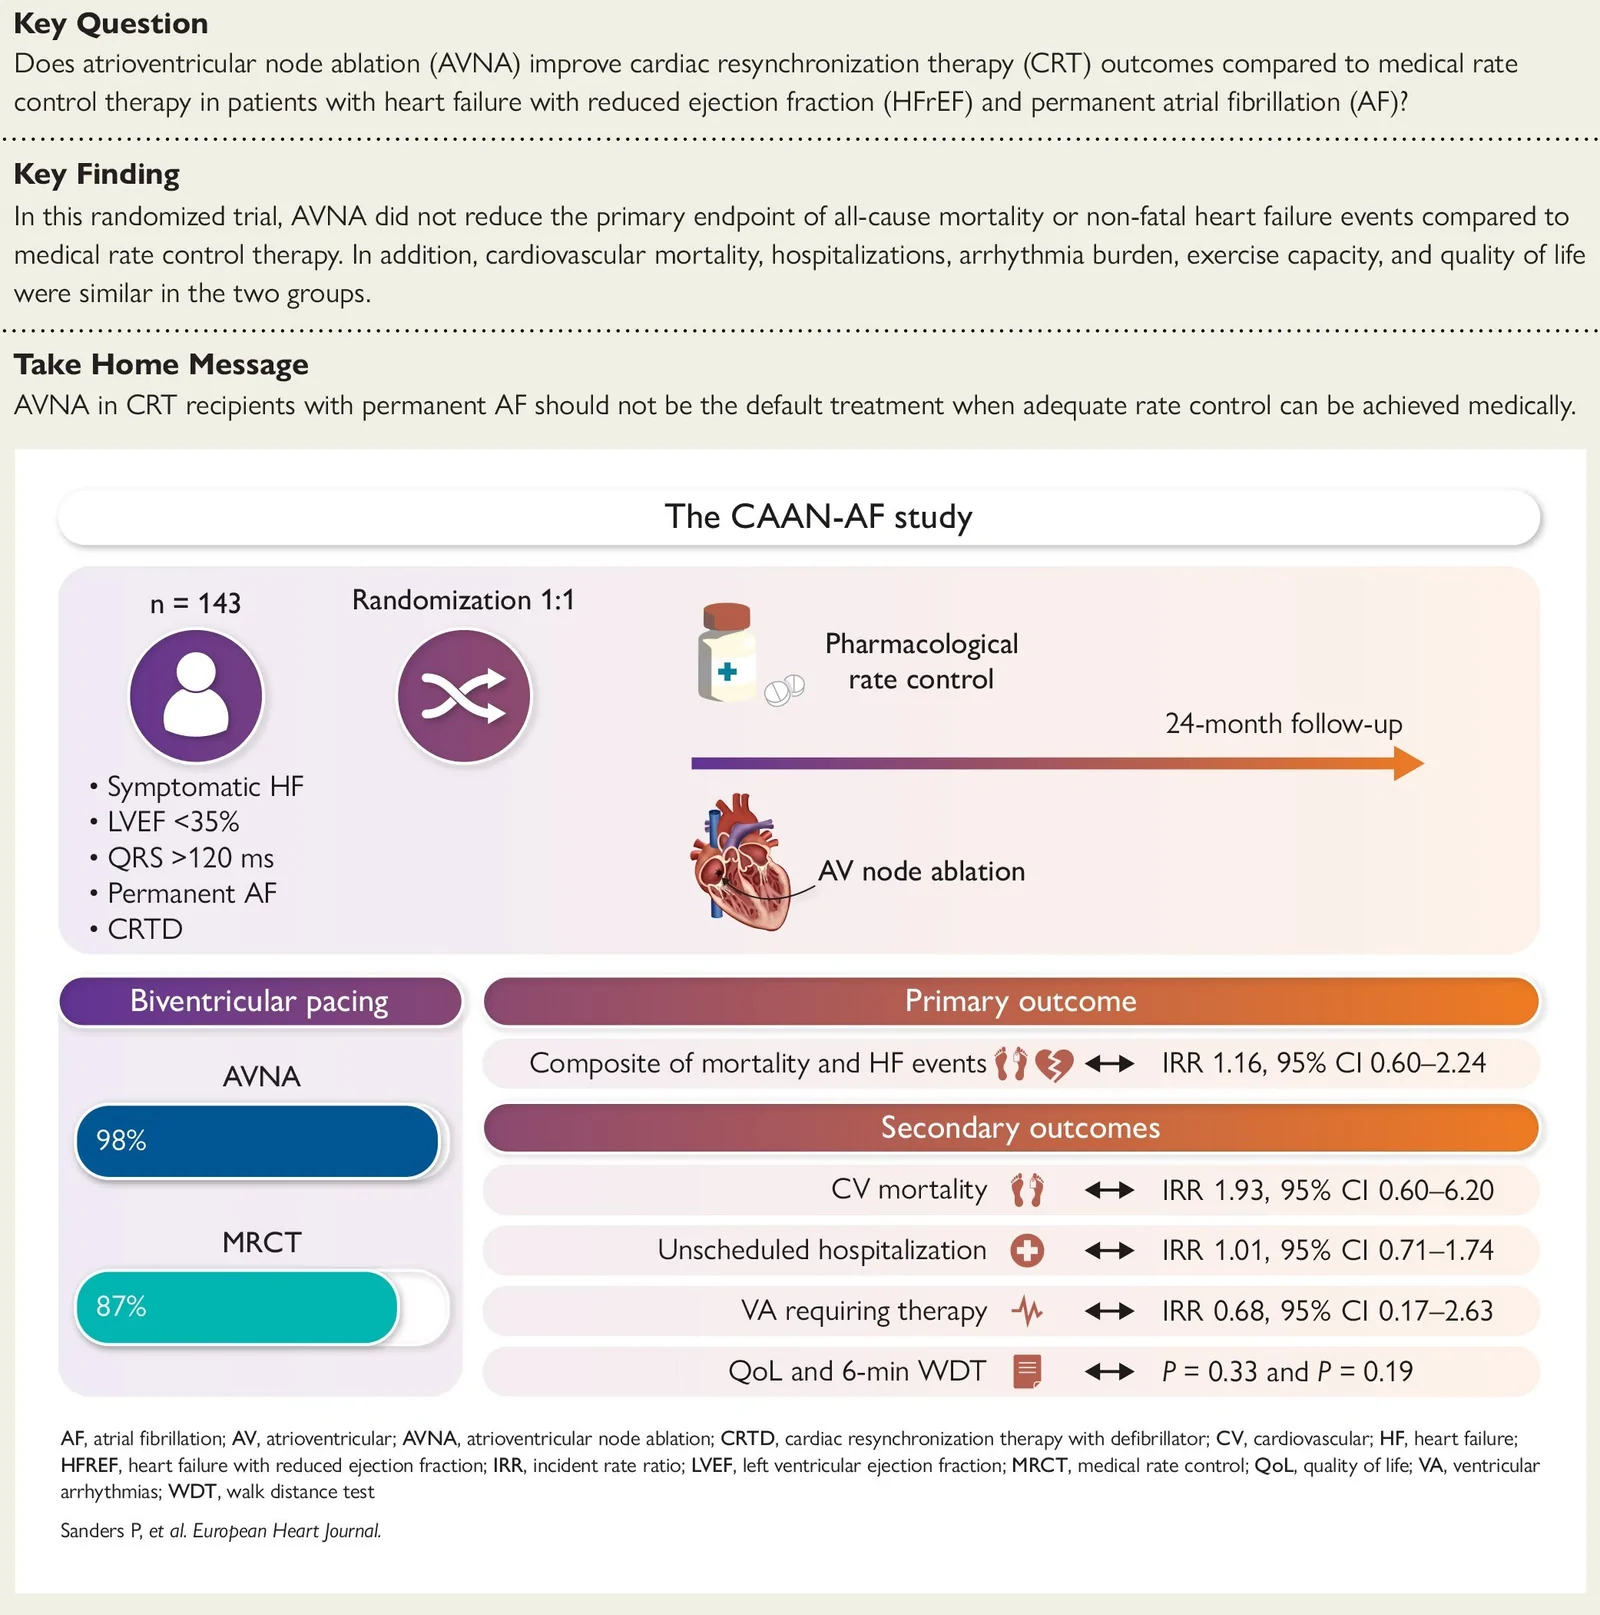
The CAAN-AF (Cardiac resynchronization therapy with AV node ablation in Atrial Fibrillation) trial was designed to rigorously compare AVNA plus CRT with optimized medical rate control therapy (MRCT) plus CRT in patients with HFrEF and permanent AF, to determine whether AVNA improves clinical outcomes.
Methods
This international, multicenter, randomized controlled trial enrolled patients with symptomatic HFrEF, permanent AF refractory to rhythm control strategies, and an indication for CRT-defibrillator implantation (CRT-D). Participants were randomized 1:1 to either AVNA or MRCT targeting a resting heart rate below 90 beats per minute.
Patients in both arms received aggressive device optimization to enhance CRT response, including adjustments to lead positioning and device programming aimed at achieving optimal ventricular synchrony.
The primary endpoint was a composite of all-cause mortality and nonfatal heart failure events, reflecting both survival and morbidity impacts. Secondary endpoints included cardiovascular-specific mortality, unplanned hospitalizations, ventricular arrhythmias necessitating device therapy, functional capacity measured by 6-minute walk distance (6MWD), and quality of life assessed by the SF-36 survey.
Results
The trial was terminated early due to futility after enrolling 143 patients (67 in the AVNA group and 76 in the MRCT group). Baseline characteristics were balanced between groups, including age, functional status, and cardiac function parameters.
Analysis of the primary endpoint revealed no statistically significant difference: 47 events occurred in the AVNA group versus 46 in the MRCT group. The incident rate ratio (IRR) was 1.16 with a 95% confidence interval (CI) of 0.60 to 2.24, indicating no survival or heart failure event reduction with AVNA.
Secondary outcomes similarly showed no significant improvements with AVNA. Cardiovascular mortality odds ratio was 1.93 (95% CI: 0.60-6.20), unplanned hospitalizations IRR was 1.01 (95% CI: 0.71-1.74), and ventricular arrhythmias requiring device therapy IRR was 0.68 (95% CI: 0.17-2.63). Functional capacity and quality of life—6MWD and SF-36 scores—also showed no meaningful differences.
Discussion
The findings suggest that AVNA does not confer additional benefit over optimized medical rate control in patients with permanent AF undergoing CRT-D implantation. While AVNA theoretically improves ventricular pacing efficacy by eliminating irregular AV conduction, this did not translate into improved clinical endpoints in this trial.
The early termination of the trial limits the power to detect smaller differences; however, the similarity in outcomes across multiple endpoints underscores the lack of a clear advantage.
Medical rate control remains a viable and less invasive alternative for these patients, focusing on careful titration of pharmacologic agents such as beta-blockers, digoxin, or calcium channel blockers to maintain heart rate control.
Future research could explore patient subgroups that might benefit from AVNA or refine CRT device programming and pacing strategies to optimize outcomes in the setting of AF.
Conclusion
The CAAN-AF trial provides pivotal evidence that in patients with heart failure and permanent atrial fibrillation, adding atrioventricular node ablation to cardiac resynchronization therapy with defibrillator does not reduce mortality or heart failure events compared with optimized medical rate control.
Clinicians should consider the lack of demonstrated benefit from AVNA when planning management strategies for this complex patient group, balancing procedural risks and patient preferences.
Trial Registration and Citation
This trial is registered under ClinicalTrials.gov identifier NCT01522898.
Reference: Sanders P, Ariyaratnam JP, Stiles MK, et al. Cardiac resynchronization therapy with or without atrioventricular node ablation in atrial fibrillation: the CAAN-AF trial. European Heart Journal. 2026;47(36):5128-5138. PMID: 41985940.


