

Highlight
- Blood transcriptomic signatures effectively track treatment response in drug-susceptible pulmonary tuberculosis patients.
- Several validated signatures predict recurrence and mortality, outperforming culture-based markers at baseline and month 2 of therapy.
- Only a subset of 22 published signatures met WHO Target Product Profile criteria for clinical utility at early timepoints.
- These findings support biomarker-guided personalized tuberculosis treatment and intensified care for patients at risk of poor outcomes.
Study Background and Disease Burden
Pulmonary tuberculosis (TB) remains a major global health burden, causing significant morbidity and mortality, particularly in resource-limited settings like Brazil. Although sputum smear and culture remain the cornerstone for diagnosis and treatment monitoring, their limitations include slow turnaround times and difficulties in sample collection, especially in paucibacillary or extrapulmonary forms. Moreover, predicting unfavorable treatment outcomes, such as treatment failure, recurrence, or death, remains challenging with existing clinical and microbiological tools. Thus, there is a critical unmet need for non-sputum biomarkers that can rapidly and reliably monitor disease progression and prognosis, enabling early tailored interventions to improve patient outcomes and reduce TB transmission.
Study Design
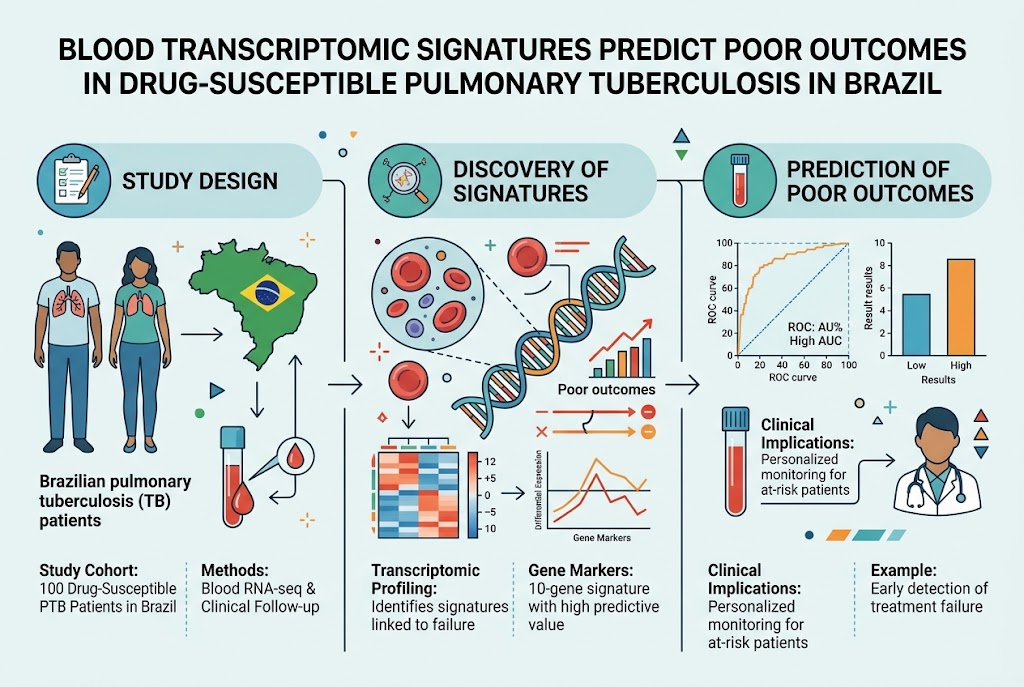
This prospective multicenter cohort study was conducted across five Brazilian sites, enrolling adults with culture-confirmed, drug-susceptible pulmonary tuberculosis. Whole-blood samples were collected using PAXgene tubes at three key time points: baseline (prior to treatment initiation), month 2 (M2), and at the end of treatment (EoT). The primary clinical endpoints were treatment failure (persistent sputum culture positivity at or beyond month 5), recurrence (clinical or microbiological recurrence within 24 months post-treatment initiation), and death (due to tuberculosis or unknown causes during treatment or follow-up).
The study employed microfluidic reverse transcription quantitative PCR (RT-qPCR) technology to measure expression levels of 22 previously published blood transcriptomic signatures associated with TB. Participants with unfavorable outcomes (treatment failure, death, or recurrence) were matched approximately 1:3 to those with recurrence-free cure, allowing comparative evaluation of signature prognostic performance. The predictive accuracy of these transcriptomic signatures was evaluated against World Health Organization (WHO) Target Product Profile (TPP) criteria for triage and treatment monitoring tools.
Key Findings and Results
A total of 263 participants with recurrence-free cure were matched to 33 with treatment failure, 24 who died (from TB or unknown causes), and 9 with recurrence. Signature scores consistently declined from baseline through EoT, reflecting treatment response dynamics.
At baseline and M2, multiple transcriptomic signatures predicted tuberculosis recurrence effectively, with area under the receiver operating characteristic curve (AUC) values ranging from 0.71 to 0.91. This predictive performance generally declined when signatures were measured at EoT (AUC range 0.42–0.89). Against WHO TPP benchmarks, 2 of 22 signatures met minimum criteria at baseline, while 13 of 22 signatures did so at M2, emphasizing the importance of early monitoring time points. No signatures fulfilled TPP criteria at EoT, suggesting diminished prognostic utility post-treatment.
Prediction accuracy for treatment failure was relatively poor across all three studied time points, with AUC values below 0.70, indicating that current blood transcriptomic signatures may not adequately discriminate this outcome.
Importantly, several signatures measured at baseline predicted death during treatment or follow-up with high accuracy (AUC ≥0.80). This highlights the potential utility of transcriptomic biomarkers in identifying patients at high risk of mortality who may benefit from enhanced clinical attention.
Overall, these data demonstrate that blood transcriptomic signatures robustly track treatment response and predict key poor outcomes such as recurrence and death in patients with drug-susceptible pulmonary TB.
Expert Commentary
The study by Mendelsohn et al. represents a significant advance in the quest for reliable non-sputum biomarkers in tuberculosis management. By leveraging a large, well-characterized Brazilian cohort and benchmarking against WHO stringent TPP criteria, the investigators provide robust validation of transcriptomic signatures that might operate as practical clinical tools.
The ability of transcriptomic signatures to predict recurrence and mortality as early as treatment initiation or at 2 months offers crucial opportunities for personalized medicine approaches. For example, patients identified as early responders could be candidates for shorter, less toxic treatment regimens, while those flagged as high-risk could receive intensified treatment and follow-up.
However, limited prediction of treatment failure indicates that some mechanisms underlying persistent bacillary presence may not be fully captured by host response signatures alone. Combining transcriptomics with other biomarkers, including pathogen-derived or imaging markers, might improve performance further.
Additionally, external validation in geographically and genetically diverse populations and prospective clinical trials are necessary to translate these biomarker insights into routine care. Importantly, cost-effectiveness, assay standardization, and accessibility in endemic settings are essential considerations before widescale implementation.
Conclusion and Summary
This comprehensive evaluation of host blood transcriptomic signatures in Brazilian adults with drug-susceptible pulmonary tuberculosis underscores their potential to transform treatment monitoring and prognosis. Signatures measured at baseline and month 2 of therapy met WHO Target Product Profile criteria for predicting tuberculosis recurrence and mortality, demonstrating clinical utility beyond conventional sputum-based methods.
Despite limited accuracy in predicting treatment failure, these findings support further development of biomarker-guided strategies to individualize tuberculosis therapy. Such approaches could enable therapy shortening for early responders and enhanced care for patients at risk of poor outcomes, ultimately improving global TB control efforts.
Funding and ClinicalTrials.gov Registration
The study was funded by collaborative consortia including RePORT South Africa and RePORT Brazil. Details on funding sources were disclosed in the original publication. ClinicalTrials.gov registration information was not specified in the cited article.
References
1. Mendelsohn SC, Andrade BB, Araújo-Pereira M, et al. Blood transcriptomic signatures predict poor outcomes in drug-susceptible pulmonary tuberculosis in Brazil. Am J Respir Crit Care Med. 2026;212(9):2211-2225. PMID: 42085241.
2. World Health Organization. High-priority target product profiles for new tuberculosis diagnostics: report of a consensus meeting, 2014.
3. Sweeney TE, Braviak L, Tato CM, et al. Genome-wide expression for diagnosis of pulmonary tuberculosis: a systematic review and meta-analysis. Lancet Respir Med. 2016;4(3):213-224.
4. Warsinske HC, Vashisht R, Khatri P. Host-response-based gene signatures for tuberculosis diagnosis: a systematic comparison of 16 signatures. PLoS Med. 2019;16(4):e1002786.
5. Kaforou M, Wright VJ, Oni T, et al. Detection of tuberculosis in HIV-infected and -uninfected African adults using whole blood RNA expression signatures: a case-control study. PLoS Med. 2013;10(10):e1001538.


