

Highlight
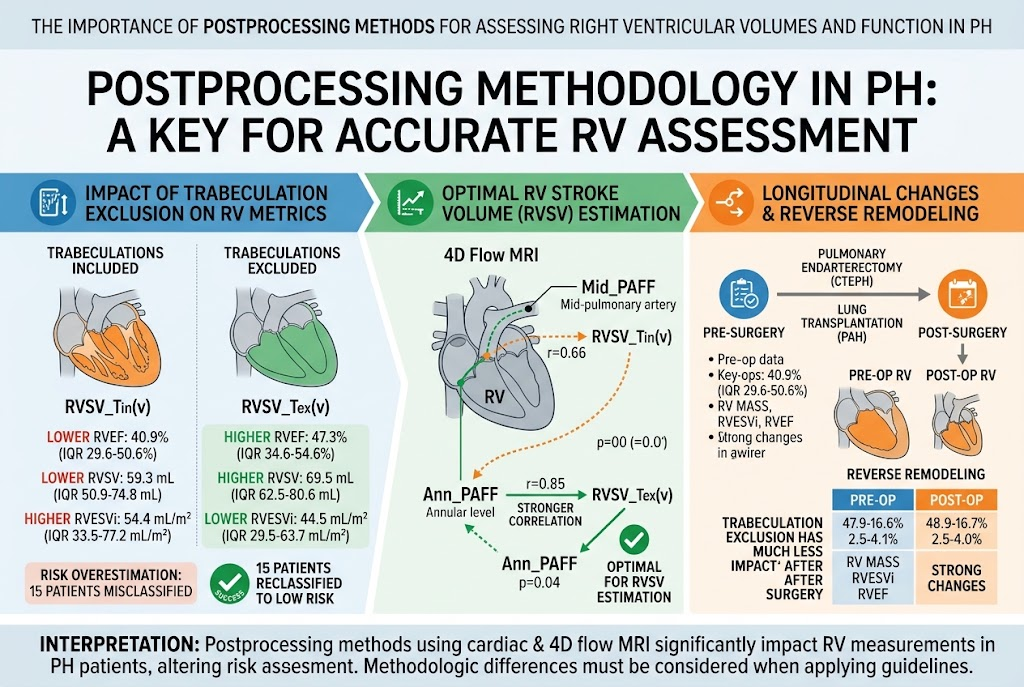
1. Exclusion of right ventricular (RV) trabeculations in cardiac MRI significantly increases measured RV ejection fraction (RVEF), stroke volume (RVSV), and mass compared to standard inclusion methods, leading to altered risk stratification in pulmonary hypertension (PH) patients.
2. Pulmonary artery (PA) flow measured at the annular level via 4D flow MRI correlates more strongly with RVSV when trabeculations are excluded, enhancing accuracy of volumetric assessment.
3. Post-surgical evaluation shows that the impact of trabeculation exclusion on RV metrics diminishes, consistent with reverse remodeling in chronic thromboembolic and pulmonary arterial hypertension after intervention.
4. Methodological differences in cardiac MRI postprocessing meaningfully influence RV functional and volumetric parameters, underscoring the need for standardized protocols to improve prognostic accuracy in PH.
Study Background
Pulmonary hypertension (PH) encompasses a group of progressive diseases characterized by elevated pulmonary arterial pressures, leading to right ventricular (RV) dysfunction and failure, which are major determinants of morbidity and mortality. Accurate assessment of RV volumes and function is crucial for prognostication and therapeutic decision-making. Cardiac magnetic resonance imaging (MRI) has emerged as the gold standard noninvasive modality for RV evaluation due to its high spatial resolution and reproducibility. However, discrepancies exist in reported RV volumetric thresholds and functional metrics used by expert centers, potentially due to differing postprocessing definitions, particularly regarding the inclusion or exclusion of RV trabeculations—the muscular ridges lining the RV cavity.
Furthermore, pulmonary artery (PA) flow quantification using advanced 4-dimensional (4D) flow MRI techniques presents a complementary approach to estimate stroke volume and evaluate pulmonary hemodynamics. Yet, the optimal site within the PA for flow measurement to accurately reflect RV stroke volume remains uncertain, and may vary depending on postprocessing strategies applied to RV volume assessment.
Study Design and Methods
This prospective study enrolled 42 patients diagnosed with PH under the Postoperative Right Heart Remodeling in Patients With Chronic Thromboembolic Pulmonary Hypertension After Endarterectomy, or Pulmonary Arterial Hypertension After Lung Transplantation (POST-REMODEL) study (ClinicalTrials.gov NCT03205085). Participants underwent right heart catheterization and comprehensive cardiac MRI including 4D flow MRI. The RV volumes and functional parameters—RV stroke volume (RVSV), RV ejection fraction (RVEF), RV end-systolic volume index (RVESVi), and RV mass—were quantified using two postprocessing approaches: one including trabeculations within the RV volume (RVSV_Tin(v)) and one excluding trabeculations (RVSV_Tex(v)).
PA forward flow (PAFF) was measured at two anatomical levels—the mid-PA trunk (Mid_PAFF) and the PA annular level (Ann_PAFF)—using 4D flow MRI. Correlations between RVSV methods and PAFF measurements were compared to determine the optimal pairing for accurate stroke volume estimation. Additionally, 23 patients underwent repeat evaluations following surgical interventions—pulmonary endarterectomy for chronic thromboembolic PH or lung transplantation for refractory pulmonary arterial hypertension—to assess longitudinal remodeling effects.
Key Findings and Results
Impact of Trabeculation Exclusion on RV Metrics: Excluding trabeculations led to statistically significant increases in median RVEF (47.3% vs 40.9%, P < .001), RVSV (69.5 mL vs 59.3 mL, P < .001), and RV mass (54.5 g vs 37 g, P < .001). Conversely, RV end-systolic volume index was lower when trabeculations were excluded (44.5 mL/m2 vs 54.4 mL/m2, P < .001). These shifts reclassified 15 patients from higher to lower risk categories based on RVEF thresholds, highlighting the clinical relevance of postprocessing methods in risk stratification.
Correlation Between PA Flow and RV Stroke Volume: Comparing the standard method (Mid_PAFF with RVSV_Tin(v)) to Ann_PAFF with RVSV_Tex(v), the latter demonstrated a stronger correlation (r = 0.85 vs r = 0.66, P = .04), suggesting that annular PA flow measurement paired with trabeculation-excluded RV volumes yields more accurate RV stroke volume estimation. This has important implications for optimizing 4D flow MRI protocols in PH evaluation.
Longitudinal Changes Post-Surgery: In the subset of 23 patients reassessed after intervention, marked improvements in RV mass, RVESVi, and RVEF were observed, indicative of reverse remodeling following pulmonary endarterectomy or lung transplantation. Additionally, the influence of trabeculation exclusion on RV metrics was markedly attenuated postoperatively, likely reflecting remodeling-induced changes in trabecular architecture and ventricular geometry.
Expert Commentary
This study rigorously demonstrates that methodological nuances in cardiac MRI postprocessing substantially influence the quantification of RV volumes and function—parameters central to PH management. The exclusion of trabeculations unmasked subtle but important changes in ventricular function that could alter prognostic classification and potentially treatment strategies. Moreover, the identification of the PA annulus as the superior site for flow measurement when using trabeculation-excluded volumes underscores the need for harmonization of MRI protocols.
Limitations include the moderate sample size and single-center cohort, which may affect generalizability. Moreover, the manual delineation of trabeculations introduces potential operator variability. Further multicenter studies are warranted to validate these findings and to explore automated segmentation techniques that can standardize postprocessing.
Conclusion
This study underscores the critical impact of postprocessing methodology on cardiac MRI-derived RV metrics in patients with pulmonary hypertension. Excluding trabeculations from RV volume calculation leads to higher measured RVEF, stroke volume, and mass, which substantially affects risk classification. Combining these volumetric methods with pulmonary artery annular flow measurement via 4D flow MRI enhances the accuracy of RV stroke volume estimation. Postoperative remodeling diminishes these methodological differences, reflecting changes in RV structure. These insights advocate for standardized cardiac MRI postprocessing protocols to optimize RV function assessment, improve prognostic precision, and guide therapeutic interventions in PH.
Funding and Clinical Trial Registration
This study was conducted under the auspices of the POST-REMODEL clinical trial (ClinicalTrials.gov registration number: NCT03205085). Funding details are provided in the original publication.
References
Azarine A, Kasani K, Kim YW, et al. The Importance of Postprocessing Methods for Assessing Right Ventricular Volumes and Function in Patients With Pulmonary Hypertension: Results From the Postoperative Right Heart Remodeling in Patients With Chronic Thromboembolic Pulmonary Hypertension After Endarterectomy, or Pulmonary Arterial Hypertension After Lung Transplantation Study. Chest. 2026 May 14;170(3):861-876. PMID: 42134497.


