

Highlight
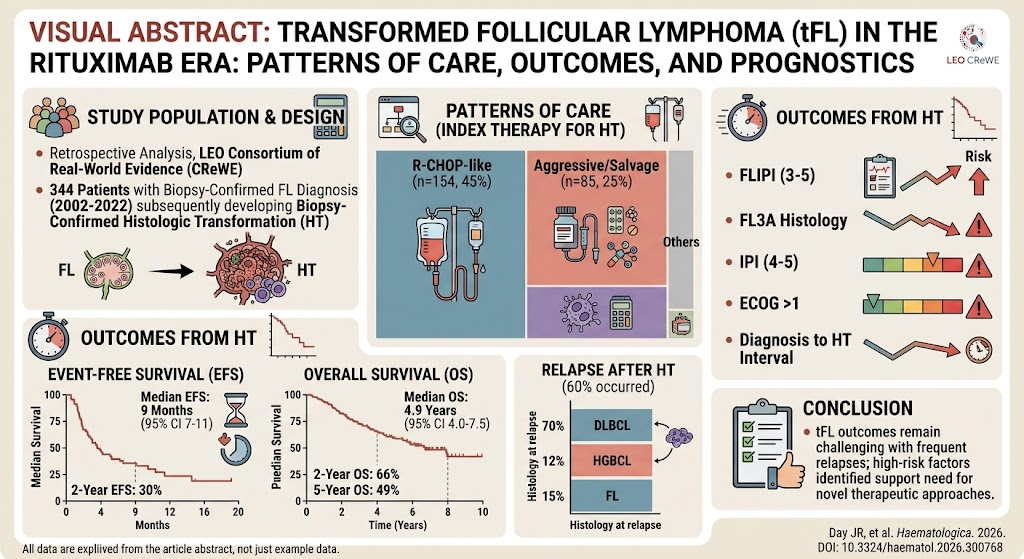
Histologic transformation (HT) of follicular lymphoma (FL) remains the principal cause of mortality despite advances with rituximab-based therapies. This large real-world cohort study of 344 patients characterized patterns of care and outcomes over two decades, highlighting a median event-free survival of just 9 months after transformation, with a 2-year survival rate of 66%. High-risk clinical scores and aggressive histologic features correlated strongly with poor outcomes, informing prognostic stratification and treatment decisions.
Study Background
Follicular lymphoma is an indolent B-cell non-Hodgkin lymphoma typically responsive to immunochemotherapy. However, histologic transformation to a more aggressive lymphoma subtype, often diffuse large B-cell lymphoma (DLBCL), markedly worsens prognosis. HT is the leading cause of death among FL patients. Despite the widespread adoption of rituximab-containing regimens since the early 2000s, outcomes after transformation remain incompletely defined. Prior studies have been limited by small cohorts and heterogeneous diagnostic criteria for HT, resulting in unclear treatment patterns and prognostic factors in the contemporary era.
Study Design
This retrospective cohort study utilized data from the Lymphoma Epidemiology of Outcomes (LEO) Consortium’s Real-World Evidence (CReWE) database, encompassing patients diagnosed initially with biopsy-confirmed FL between 2002 and 2022 who subsequently developed biopsy-confirmed HT. A total of 344 patients met criteria. Baseline demographic and clinical characteristics, including age, FLIPI and IPI scores, ECOG performance status, and histology, were collected. Initial treatment post-HT (index therapy) was categorized broadly into R-CHOP-like regimens and more aggressive/salvage therapies. Event-free survival (EFS) and overall survival (OS) from HT diagnosis were primary endpoints, with relapse patterns and subsequent therapies also analyzed.
Key Findings
The median age at HT was 64 years (IQR 57-72). Initial therapy post-transformation was R-CHOP-like in 45% (n=154), while 25% (n=85) received aggressive or salvage treatments, which often included autologous stem cell transplantation (ASCT) or chimeric antigen receptor T-cell (CAR-T) therapy.
Median event-free survival from HT diagnosis was only 9 months (95% CI, 7-11), with a 2-year EFS rate of 30% (95% CI, 26%-36%), underscoring the high relapse and progression risk. Median overall survival from HT was 4.9 years (95% CI, 4.0-7.5), with 2-year and 5-year OS rates of 66% (95% CI, 61%-71%) and 49% (95% CI, 43%-56%), respectively.
Relapses after HT were frequent, occurring in 60% of patients. The histology at relapse was predominantly DLBCL (70%), followed by follicular lymphoma (15%) and high-grade B-cell lymphoma (HGBCL) (12%). Among those relapsing, 44% received aggressive salvage therapy, often involving ASCT or CAR-T cell therapy, reflecting evolving therapeutic options for relapsed disease.
Prognostic factors independently associated with poorer outcomes included higher FLIPI scores (3-5), presence of grade 3A follicular histology, IPI scores of 4-5, and ECOG performance status greater than 1 at HT diagnosis. Additionally, shorter interval from initial FL diagnosis to transformation correlated with worse prognosis.
Expert Commentary
This comprehensive real-world study provides valuable insights into clinical outcomes and treatment patterns for transformed follicular lymphoma in the rituximab era. The modest median OS and poor event-free survival following HT emphasize the need for early identification of patients at risk and innovative therapeutic approaches. The predominance of DLBCL histology at relapse supports the concept that HT represents evolution to a biologically distinct and more aggressive clone.
Importantly, the study highlights the continued reliance on intensive chemotherapy regimens such as R-CHOP and salvage approaches like ASCT and CAR-T cell therapy to manage HT and relapse, reflecting current standards yet underscoring the unmet need for improved frontline therapies and risk-adapted strategies to prevent transformation.
Limitations include its retrospective nature and potential selection bias inherent in real-world datasets, as well as heterogeneity in treatment protocols across centers. Nevertheless, the large sample size and reliance on biopsy-confirmed transformations strengthen its validity. Future prospective trials incorporating molecular profiling and targeted therapies are warranted to refine prognostication and improve survival.
Conclusion
Histologic transformation of follicular lymphoma continues to confer a significant adverse prognosis despite rituximab-based chemoimmunotherapy. This large cohort study delineates critical clinical features and treatment outcomes in the contemporary era, revealing high relapse rates and limited event-free survival. Prognostic indices such as FLIPI and IPI scores, histology, and performance status provide useful stratification tools. These findings support ongoing efforts to develop novel treatments and integrate precision oncology approaches to enhance patient management after transformation.
Funding and ClinicalTrials.gov
The original study did not explicitly mention funding sources or clinical trial registration numbers. Further details should be sought directly from the LEO Consortium or corresponding publication.
References
Day JR, Larson MC, Casulo C, et al. Patterns of care, outcomes, and prognostics for transformed follicular lymphoma in the rituximab era. Haematologica. 2026 Sep 24. PMID: 42779337. Available from: https://pubmed.ncbi.nlm.nih.gov/42779337/
Montoto S, Davies AJ, Matthews J, et al. Risk factors and outcome of follicular lymphoma transformation in the rituximab era: a British Columbia population-based study. Blood. 2013;122(8): 1242-1248.
Salles G, Seymour JF, Offner F, et al. Rituximab maintenance for 2 years in patients with high tumour burden follicular lymphoma responding to rituximab plus chemotherapy (PRIMA): a phase 3, randomised controlled trial. Lancet. 2011;377(9759): 42-51.


