

Highlight
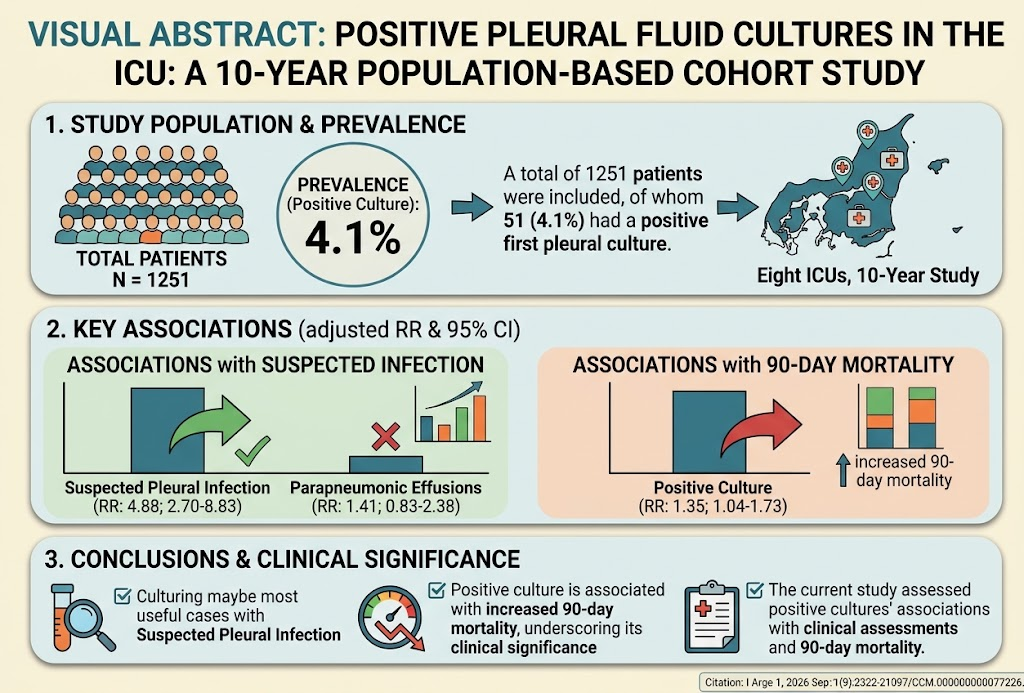
- The prevalence of positive pleural fluid cultures in ICU patients undergoing drainage is low, at 4.1% over a 10-year period.
- Suspected pleural infection strongly increases the likelihood of positive pleural fluid cultures (adjusted RR 4.88).
- Parapneumonic effusions do not show a significant association with positive pleural fluid cultures.
- Positive pleural fluid cultures correlate with increased 90-day all-cause mortality (adjusted RR 1.35), underscoring clinical importance.
Study Background
Pleural effusions, defined as abnormal fluid accumulation in the pleural space, are frequently encountered in intensive care units (ICUs) due to a variety of critical illnesses including infections, malignancies, and systemic inflammatory states. Timely diagnosis and appropriate management of suspected pleural infections, including empyema and complicated parapneumonic effusions, are essential to improve patient outcomes. The collection of pleural fluid for microbiological cultures is a standard diagnostic step; however, the prevalence of positive cultures and their clinical implications in ICU settings remain underexplored. Clarifying the microbial epidemiology and the impact of positive cultures on mortality can guide diagnostic and therapeutic approaches, thereby reducing morbidity and mortality associated with pleural infections in critically ill patients.
Study Design
This retrospective, population-based cohort study analyzed data from eight ICUs covering the entire North Denmark Region over a 10-year span (March 1, 2013, to February 28, 2023). Inclusion criteria encompassed all adult patients who underwent pleural fluid culturing during their ICU stay. The study extracted microbiological, administrative, and clinical data from a regional microbiological database and electronic medical records. The primary endpoint was the prevalence of positive microbial growth on first pleural fluid cultures. Secondary outcomes included 90-day all-cause mortality post-culture. Statistical analyses employed multiple regression models to evaluate associations between clinical categories such as suspected pleural infection and parapneumonic effusion on culture positivity, and between positive pleural fluid cultures and mortality risk, adjusting for relevant confounders.
Key Findings
The study included 1251 patients who underwent pleural fluid culture in ICU. Among these, only 51 (4.1%) had a positive microbial culture on their initial specimen, indicating a relatively low yield of positive cultures in this critically ill population.
Suspected pleural infection markedly increased the risk of a positive pleural fluid culture with an adjusted risk ratio of 4.88 (95% confidence interval [CI]: 2.70–8.83), confirming the clinical relevance of targeted microbiological investigations in this subgroup. In contrast, parapneumonic effusion—fluid accumulation associated with pneumonia but without overt suspicion of empyema—did not show a statistically significant association with a positive culture result (adjusted RR: 1.41; 95% CI: 0.83–2.38).
Clinically significant, a positive pleural fluid culture was independently associated with increased all-cause 90-day mortality (adjusted RR: 1.35; 95% CI: 1.04–1.73). This finding underscores that microbial recovery from pleural fluid is not only a marker of infection but also linked to worse prognosis in ICU patients.
The microbial spectrum of positive cultures was not detailed in the abstract, but understanding pathogen distribution would be valuable for guiding empiric antimicrobial therapy and infection control strategies.
Expert Commentary
The rarity of positive pleural fluid cultures despite frequent sampling may reflect multiple factors: prior antibiotic administration, variability in specimen collection techniques, or low microbial load. The strong association between suspected pleural infection and positive culture emphasizes that clinical suspicion remains a critical driver of diagnostic yield.
Given the significant association between culture positivity and 90-day mortality, positive cultures could serve as an important prognostic marker, assisting clinicians in risk stratification and guiding more aggressive or tailored interventions. However, the study’s retrospective design and regional single-population basis may limit direct generalizability. Furthermore, lack of detailed microbial characterization and antibiotic treatment data constrains mechanistic insights.
These results align partly with existing observational studies emphasizing the clinical importance of detecting pathogens in pleural infections. Current guidelines recommend pleural fluid culture to inform antimicrobial therapy, but this study refines understanding by quantitatively linking culture positivity to clinical context and mortality risk specifically in the ICU setting.
Conclusion
This population-based cohort study provides robust epidemiological data on pleural fluid culture positivity in critically ill patients, highlighting a generally low prevalence but a strong association with suspected pleural infection and increased mortality. These findings support judicious use of pleural fluid cultures primarily in patients with clinical suspicion of infection and reinforce the prognostic implications of positive cultures in the ICU. Future prospective studies are needed to elucidate microbial profiles, optimize diagnostic approaches, and assess the impact of culture-guided therapies on patient outcomes.
Funding and Clinical Trial Registration
Funding sources and clinical trial registration details were not provided in the abstract. Further inquiry into the full publication is recommended to identify potential conflicts of interest and funding disclosures.
References
Arge SI, Frambo SP, Nielsen FM, Rasmussen BS, Nielsen HL, Søgaard KK, Schjørring OL. Positive Pleural Fluid Cultures in the ICU: A 10-Year Population-Based Cohort Study of Prevalence, Microbial Characteristics, and Clinical Associations. Crit Care Med. 2026 Jun 12;54(9):2322-2334. PMID: 42283551.


