

Highlight
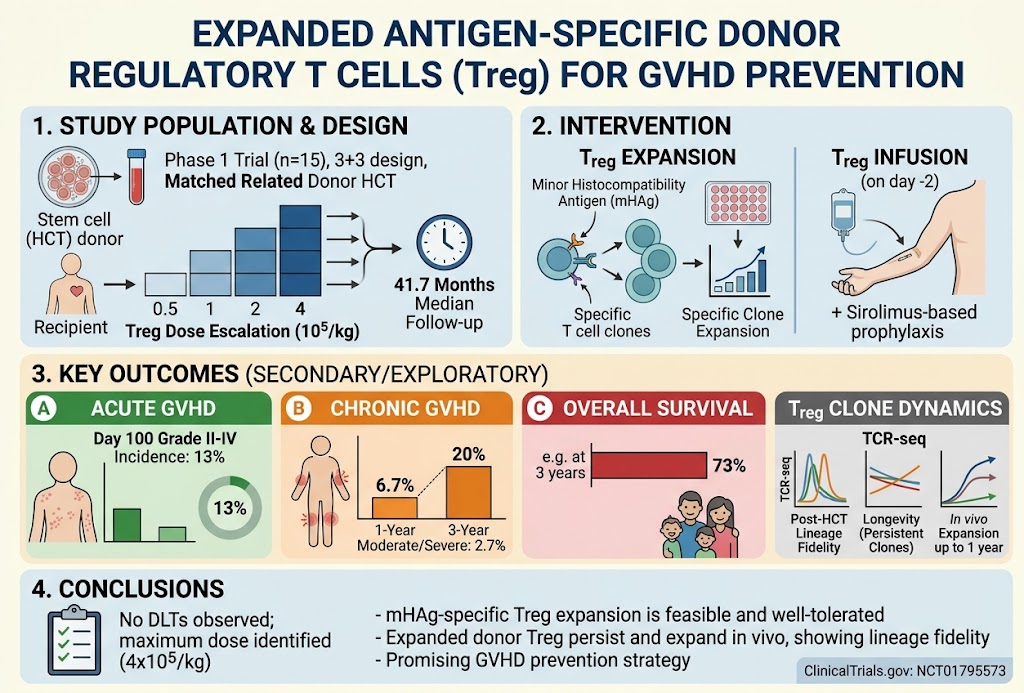
This phase 1 clinical trial assessed safety and initial efficacy of expanded minor histocompatibility antigen (mHAg)-specific donor regulatory T cells (Treg) infused prior to allogeneic hematopoietic cell transplantation (HCT) for graft-versus-host disease (GVHD) prevention. The maximum tolerated dose was identified as 4 × 10^5 Treg/kg with no dose-limiting toxicities. This approach, combined with sirolimus immunosuppression, yielded low acute and chronic GVHD incidences, high overall survival, and demonstrated long-term persistence and in vivo expansion of infused Treg clones.
Study Background
Graft-versus-host disease (GVHD) remains a significant complication of allogeneic hematopoietic cell transplantation (HCT), driven primarily by donor T cells recognizing minor histocompatibility antigens (mHAgs). Despite advances in HCT techniques and pharmacologic prophylaxis, acute and chronic GVHD continue to impair patient outcomes, contributing to morbidity and mortality. Regulatory T cells (Tregs) have immunomodulatory properties capable of suppressing alloreactive T cell responses. Prior efforts to prevent GVHD with polyclonal Treg infusions have shown promise but face challenges in scalability and specificity. Antigen-specific Tregs targeting mHAgs offer a more precise approach to suppressing deleterious alloimmune responses without compromising graft-versus-leukemia effects.
Study Design
This first-in-human phase 1 clinical trial (NCT01795573) utilized a 3+3 dose-escalation design to evaluate safety and preliminary efficacy of mHAg-specific donor Treg infusion combined with sirolimus-based immunoprophylaxis in matched related donor HCT recipients. Four escalating dose levels were tested: 0.5, 1, 2, and 4 × 10^5 Treg/kg. Tregs were expanded ex vivo from donor cells to achieve antigen specificity toward recipient mHAgs. The Treg infusion occurred on day -2 before HCT. The primary endpoint was safety focused on dose-limiting toxicities (DLTs), including severe infusion reactions, unexpected organ toxicity, severe acute GVHD, or treatment-related mortality. Secondary and exploratory endpoints included incidences of acute and chronic GVHD, survival, and the in vivo persistence and clonal expansion of Tregs assessed by T cell receptor sequencing (TCR-seq).
Key Findings
Fifteen patients were enrolled, with cohorts of three at each dose level for the first three doses and six patients at the highest dose (4 × 10^5/kg). No dose-limiting toxicities or grade III-IV acute GVHD events directly attributed to Treg infusion were observed across all doses, establishing the maximum tolerated dose at 4 × 10^5 Treg/kg. Median follow-up for surviving patients was 41.7 months (range 14.5–72.8 months), providing substantial mid-term outcome data.
Notably, the cumulative incidence of grade II-IV acute GVHD at day 100 was 13%, substantially lower than historical controls. The burden of chronic GVHD was also minimal, with 6.7% experiencing moderate or severe chronic GVHD at one year and 20% at three years, suggesting durable GVHD prevention effects. Overall survival was 73%, reflective of favorable transplant outcomes in this high-risk setting.
On a mechanistic level, Treg clones displayed substantial expansion during ex vivo culture and maintained lineage fidelity after infusion, as demonstrated by TCR-seq analyses. The infused antigen-specific Tregs persisted in vivo with evidence of expansion up to one year post-transplant, supporting their sustained immunoregulatory function. This persistence could underpin the reduced GVHD rates, emphasizing the biological plausibility of antigen-specific Tregs as a potent cell therapy.
Expert Commentary
This groundbreaking trial pioneers the clinical application of antigen-specific expanded donor Tregs as a sophisticated cellular immunotherapy to mitigate GVHD. The absence of dose-limiting toxicities and low GVHD incidence are encouraging, pointing to the safety and therapeutic potential of this precision approach. The combination with sirolimus, which favors Treg survival, likely synergizes with the cell product to optimize immune regulation.
However, limitations include the small sample size typical of phase 1 studies and lack of a control arm, which necessitates cautious interpretation and calls for larger randomized trials. The complexity of generating antigen-specific Tregs poses logistical challenges for broad clinical adoption, but advances in cell manufacturing technologies may overcome these hurdles. Future research should investigate the impact on graft-versus-leukemia effects, long-term immune reconstitution, and the potential applicability beyond matched related donors.
Conclusion
This translational phase 1 trial demonstrates that infusion of expanded mHAg-specific donor regulatory T cells is feasible, safe, and potentially efficacious for preventing acute and chronic GVHD in allogeneic HCT. The durable in vivo persistence and expansion of infused Tregs underpin a novel mechanism of targeted immune modulation. These promising results warrant further phase 2/3 trials to validate clinical benefit and explore wider applications in transplantation immunotherapy.
Funding and ClinicalTrials.gov
The trial was registered at www.clinicaltrials.gov under identifier NCT01795573. Funding sources were not detailed in the abstract but can typically be found in the full publication.
References
Pidala J, Cieri N, Schell MJ, et al. Expanded antigen-specific donor regulatory T cells for GVHD prevention. Blood. 2026 Sep 24;148(13):1659-1669. PMID: 42322116.
Additional relevant literature on Treg-mediated GVHD prevention and antigen-specific cellular therapies can be consulted to contextualize these findings further.


