

Highlights
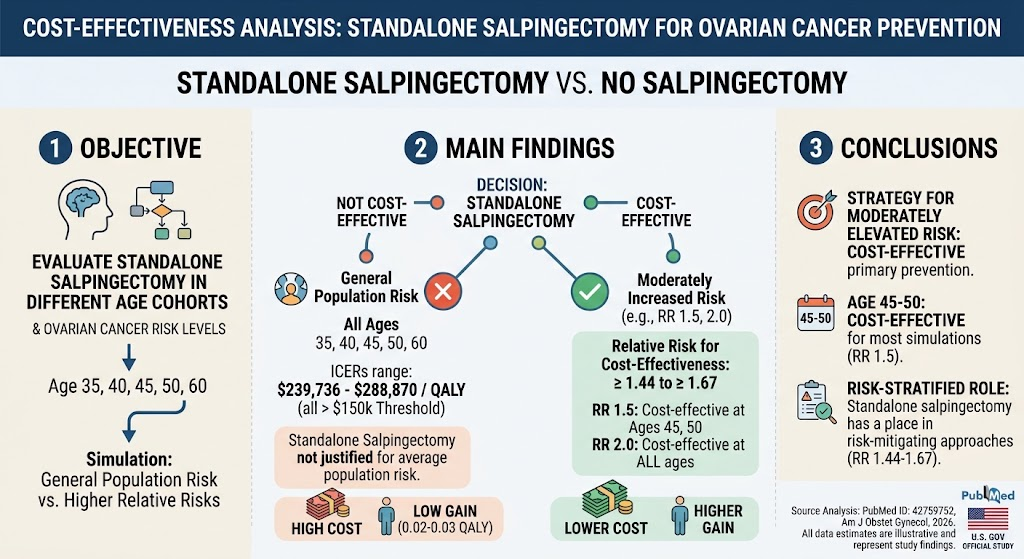
- Standalone salpingectomy is not cost-effective for average-risk women but becomes cost-effective at moderate or higher relative ovarian cancer risk levels (≥1.44–1.67).
- The age window of 45-50 years is where standalone salpingectomy is most consistently cost-effective in simulations, balancing cancer prevention benefit and surgical risk/costs.
- Markov modeling supports risk-stratified approaches for primary prevention using standalone salpingectomy, expanding beyond opportunistic procedures at other surgeries.
- Findings underscore the importance of integrating individual ovarian cancer risk profiles into prevention strategies, with potential healthcare policy implications.
Background
Ovarian cancer remains a leading cause of gynecologic cancer mortality worldwide, often due to late-stage diagnosis and limited effective screening modalities. Prevention strategies are critical, particularly for high-risk women such as those with BRCA mutations or strong family history. Recent evidence has implicated fallopian tube epithelium as an origin site for many high-grade serous ovarian cancers, shifting prevention focus to salpingectomy. Opportunistic salpingectomy, performed incidentally during other gynecologic or abdominal surgeries, has been supported as a cost-effective primary prevention approach. However, the independent utility and cost-effectiveness of standalone salpingectomy—performed without concurrent indication—requires further evaluation, especially given surgical risks, costs, and variable baseline ovarian cancer risk in the general population.
Key Content
Chronological Development of Evidence for Salpingectomy in Ovarian Cancer Prevention
Early pathologic studies and epidemiologic investigations (circa 2010s) identified the fallopian tube fimbriae as the likely site of origin for serous ovarian cancers, prompting clinical interest in prophylactic salpingectomy. Observational cohort studies demonstrated reduced ovarian cancer incidence following salpingectomy performed during benign gynecologic surgeries. Subsequent cost-effectiveness modeling of opportunistic salpingectomy indicated favorable incremental cost-effectiveness ratios (ICERs) relative to no intervention, influencing professional society guidelines to endorse opportunistic salpingectomy in appropriate surgical candidates.
Standalone Salpingectomy: Modeling Approach and Evidence Synthesis
Lazovic et al. (2026) developed a state-transition Markov decision-analytic model simulating women at ages 35, 40, 45, 50, and 60 years with varying ovarian cancer relative risks (population average to 2-fold elevated risk). The model incorporated surgical costs, cancer treatment costs, quality-adjusted life years (QALYs), and mortality, evaluating the ICER of standalone salpingectomy versus no surgery from a societal perspective and a willingness-to-pay threshold of $150,000 per QALY gained.
Key findings include:
– For average-risk women, standalone salpingectomy was not cost-effective at any age cohort (ICER $239,736–$288,870/QALY), reflecting small absolute QALY gains (0.02–0.03) against incremental costs (~$6,100 per person).
– At a moderate relative risk of 1.5, cost-effectiveness improved, with ICERs dropping to $142,516–$172,112/QALY and becoming cost-effective at ages 45 and 50.
– At a relative risk of 2.0, standalone salpingectomy was cost-effective across all ages examined (ICER $97,336–$118,544/QALY).
– The critical threshold for cost-effectiveness relative risks ranged between ≥1.44 (age 50) and ≥1.67 (age 35).
These results suggest standalone salpingectomy is most beneficial when targeted to women with moderately elevated risk based on familial, genetic, or other clinical factors, and particularly around midlife when cumulative cancer risk intersects with acceptable surgical risk.
Comparative Analysis with Opportunistic Salpingectomy and Risk-Reducing Salpingo-Oophorectomy
Compared to opportunistic salpingectomy, standalone salpingectomy bears higher costs and surgical risk given the absence of co-indicated surgery but retains preventive benefit. Risk-reducing salpingo-oophorectomy (RRSO) remains the gold standard for high-risk populations (e.g., BRCA mutation carriers) but is associated with premature menopause and associated morbidity, limiting its use in broader populations. Standalone salpingectomy offers a less morbid alternative with potential for risk reduction, positioning it as an intermediate prevention option in risk-stratified frameworks.
Expert Commentary
The findings by Lazovic et al. align with evolving understanding of ovarian carcinogenesis and underscore the need for individualized prevention strategies. While opportunistic salpingectomy remains attractive due to minimal incremental surgical risk, standalone salpingectomy’s broader implementation depends on judicious patient selection informed by validated risk stratification tools combining genetic, familial, reproductive, and potentially biomarker data.
Limitations of modeling include reliance on assumptions regarding relative risk reduction, surgical complication rates, and long-term cancer incidence, which may vary with emerging evidence. Furthermore, the cost-effectiveness thresholds and societal perspectives can differ by healthcare system, affecting generalizability. Nevertheless, the study emphasizes that population-level implementation of standalone salpingectomy may not be cost-effective but targeted interventions in moderate- to high-risk individuals hold promise.
Mechanistically, removal of fallopian tubes is biologically plausible to reduce origin sites of high-grade serous carcinoma, yet the effect on other histologic subtypes and overall mortality benefit warrants further prospective evaluation. As clinical trials and registries mature, real-world data will refine estimates of efficacy, surgical safety, and patient-centered outcomes.
Incorporation of standalone salpingectomy into guidelines will require careful weighing against alternative prevention measures and consideration of patient preferences. Multidisciplinary counseling integrating oncologic risk, surgical morbidity, reproductive plans, and quality-of-life impact remains essential.
Conclusion
Standalone salpingectomy represents a cost-effective ovarian cancer prevention strategy in women at moderately elevated risk, particularly between ages 45 and 50. It complements existing opportunistic salpingectomy practices and offers a less invasive alternative to RRSO for select populations. Future research should focus on refining risk prediction, prospective evaluation of long-term outcomes, and integration into personalized prevention algorithms. Health policy initiatives need to consider resource allocation aligned with risk-based prevention frameworks to optimize clinical and economic outcomes.
References
- Lazovic S, Chen L, Rouse KJ, Fischkoff K, Paraghamian S, Meyer LA, et al. Standalone Salpingectomy for Primary Ovarian Cancer Prevention: A Cost-Effectiveness Analysis. Am J Obstet Gynecol. 2026 Sep 18. PMID: 42759752.
- Menon U, et al. Ovarian cancer prevention and early detection: state of the art. Climacteric. 2017; 20(4): 325-331. PMID: 28582389.
- Callahan MJ, et al. Primary fallopian tube malignancies in BRCA mutation carriers. Clin Cancer Res. 2007; 13(4):337-41. PMID: 17332386.
- American College of Obstetricians and Gynecologists (ACOG). Practice Bulletin No. 222: Management of Women with an Inherited Predisposition to Breast and Ovarian Cancer. Obstet Gynecol. 2020; 135(3): e110-e126. PMID: 32162807.
- Falconer H, et al. Ovarian cancer risk after salpingectomy: a nationwide population-based study. J Natl Cancer Inst. 2015;107(2): dju410. PMID: 25561589.


