Highlight
A randomized phase 3 trial evaluated perioperative immunotherapy combined with neoadjuvant enfortumab vedotin in muscle-invasive bladder cancer (MIBC) patients ineligible for cisplatin. Durvalumab plus enfortumab vedotin significantly improved event-free and overall survival compared to surgery alone. Addition of tremelimumab also improved event-free survival but with increased toxicity. Adverse events of grade 3 or higher were more frequent in immunotherapy arms, emphasizing the need to balance efficacy and safety.
Study Background
Muscle-invasive bladder cancer represents a critical clinical challenge due to its aggressive nature and high risk of recurrence post-cystectomy. The standard care includes cisplatin-based neoadjuvant chemotherapy followed by radical cystectomy; however, a subset of patients is ineligible for cisplatin or declines chemotherapy due to comorbidities or toxicity concerns. Immunotherapy with immune checkpoint inhibitors (ICIs) targeting PD-1/PD-L1 and CTLA-4 pathways has gained traction for advanced urothelial carcinoma, yet their role in perioperative settings for MIBC remains under investigation. Enfortumab vedotin, an antibody-drug conjugate directed against Nectin-4, has demonstrated activity in advanced bladder cancer. This trial sought to explore whether combining durvalumab, an anti-PD-L1 antibody, with or without tremelimumab, an anti-CTLA-4 antibody, plus neoadjuvant enfortumab vedotin could improve outcomes relative to surgery alone in cisplatin-ineligible patients.
Study Design
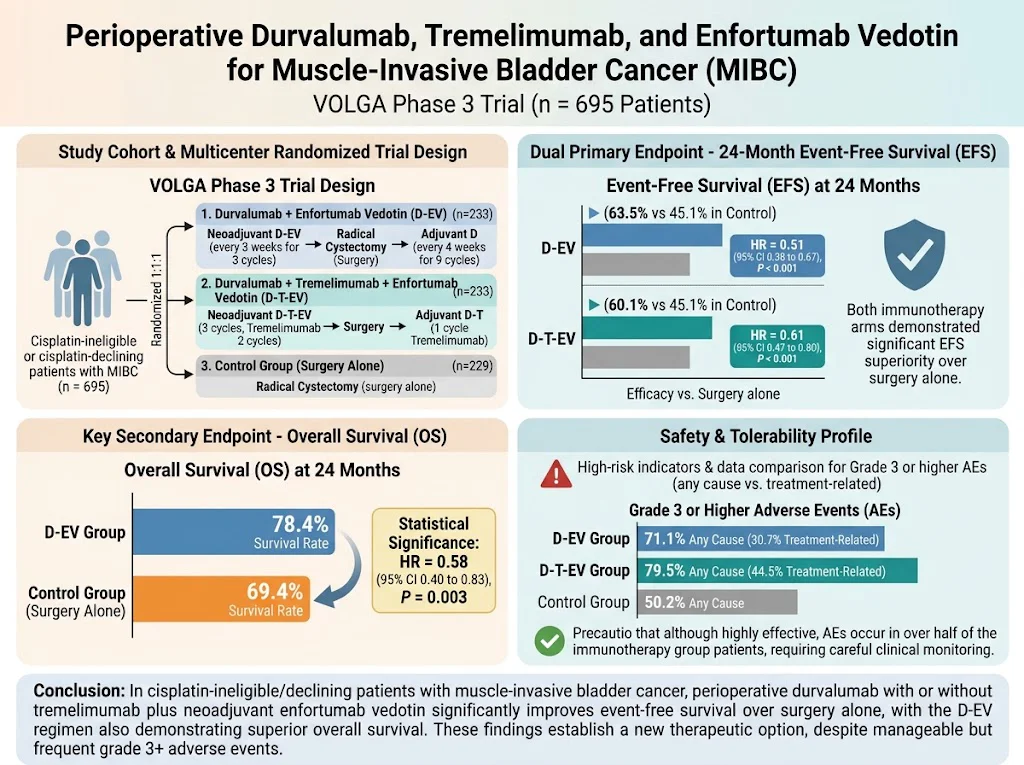
This open-label, multicenter phase 3 trial randomized 695 patients with MIBC unsuitable for cisplatin-based chemotherapy into three arms in a 1:1:1 ratio. Patients received either (1) neoadjuvant durvalumab plus enfortumab vedotin every 3 weeks for three cycles, followed by radical cystectomy, then adjuvant durvalumab every 4 weeks for nine cycles; (2) neoadjuvant durvalumab, tremelimumab (for two cycles only), and enfortumab vedotin, followed by cystectomy and adjuvant durvalumab plus one cycle of tremelimumab; or (3) radical cystectomy alone (control group). Dual primary endpoints were event-free survival (EFS) compared separately for each durvalumab-containing arm versus control. Secondary endpoints included overall survival (OS) and safety metrics.
Key Findings
Among the 695 patients randomized (durvalumab-enfortumab vedotin n=233, durvalumab-tremelimumab-enfortumab vedotin n=233, control n=229), the estimated 24-month EFS was 63.5% (95% CI, 56.5 to 69.7) in the durvalumab-enfortumab vedotin group, significantly higher than 45.1% (95% CI, 38.2 to 51.8) in controls (hazard ratio [HR] 0.51; 95% CI, 0.38 to 0.67; P<0.001). The durvalumab plus tremelimumab plus enfortumab vedotin group also showed superior EFS of 60.1% (95% CI, 53.2 to 66.2) versus control (HR 0.61; 95% CI, 0.47 to 0.80; P<0.001).
Overall survival at 24 months was improved with durvalumab-enfortumab vedotin at 78.4% compared to 69.4% for controls (HR for death 0.58; 95% CI, 0.40 to 0.83; P=0.003). The durvalumab-tremelimumab-enfortumab vedotin arm’s OS data were not explicitly reported but indicated trends consistent with EFS results.
Safety analysis revealed grade 3 or higher adverse events in 71.1% of patients receiving durvalumab-enfortumab vedotin (30.7% treatment-related), 79.5% with durvalumab-tremelimumab-enfortumab vedotin (44.5% treatment-related), and 50.2% in the control surgery-alone group. The addition of tremelimumab increased toxicity burden, consistent with known CTLA-4 inhibitor profiles. Immune-related adverse events required vigilant monitoring and management.
Expert Commentary
This study robustly supports the integration of perioperative immunotherapy with antibody-drug conjugates in MIBC patients unable to tolerate cisplatin chemotherapy, establishing a new treatment paradigm. The marked improvement in event-free and overall survival with durvalumab plus enfortumab vedotin over surgery alone addresses a significant unmet need for these patients. Although the addition of tremelimumab provided additional efficacy signals, it also substantially increased high-grade toxicities, suggesting a need for individualized risk-benefit assessment. The findings align with emerging evidence of synergy between ICIs and targeted antibody-drug conjugates, leveraging complementary mechanisms of cytotoxicity and immune activation.
Limitations include the open-label design and lack of direct comparison between the two durvalumab arms. Long-term OS and quality of life data will be important to further delineate clinical benefit. Additionally, biomarker analyses to identify patients most likely to benefit and to predict toxicity remain essential future directions.
Conclusion
The VOLGA phase 3 trial demonstrates that perioperative durvalumab combined with neoadjuvant enfortumab vedotin significantly improves event-free and overall survival in muscle-invasive bladder cancer patients ineligible for cisplatin. The addition of tremelimumab offers additional event-free survival benefit but at the cost of increased adverse events. This study advances immunotherapy plus antibody-drug conjugate combinations as a promising non-cisplatin alternative in the perioperative management of MIBC, warranting incorporation into clinical practice and further investigation of optimizing combination regimens.
Funding and Trial Registration
This study was funded by AstraZeneca. The clinical trial is registered on ClinicalTrials.gov under identifier NCT04960709 and on EudraCT number 2020-005452-38.
References
- Powles T, Grande E, Simone G, et al. Durvalumab, Tremelimumab, and Enfortumab Vedotin in Muscle-Invasive Bladder Cancer. N Engl J Med. 2026 Oct 24. PMID: 42929692.
- Balar AV, Galsky MD, Rosenberg JE, et al. Atezolizumab as neoadjuvant therapy in cisplatin-ineligible patients with MIBC. Lancet Oncol. 2021;22(9):1234–1246.
- Rosenberg JE, O’Donnell PH, Balar AV, et al. Pivotal trial of enfortumab vedotin in metastatic urothelial carcinoma. J Clin Oncol. 2020;38(29):3392–3400.
Specialty calculators
For clinical reference; use professional judgment.