

Introduction
Cervical cancer remains a significant global health challenge, particularly in cases where the disease is persistent, recurrent, or has metastasized. Traditional platinum-based chemotherapy, with or without bevacizumab, has been the cornerstone of treatment. However, the integration of immunotherapy, specifically pembrolizumab, an anti–PD-1 monoclonal antibody, has shown promise in enhancing treatment efficacy. The KEYNOTE-826 phase 3 randomized clinical trial was designed to evaluate the benefit of pembrolizumab combined with chemotherapy versus chemotherapy alone in patients with previously untreated advanced cervical cancer.
Study Background and Objectives
The KEYNOTE-826 trial enrolled women with persistent, recurrent, or metastatic cervical cancer who had not received prior systemic therapy for advanced disease. Participants were randomized to receive pembrolizumab plus platinum-based chemotherapy (with or without bevacizumab) or placebo plus chemotherapy. The initial interim analysis at a median follow-up of 22.0 months demonstrated significant improvement in progression-free survival (PFS) and overall survival (OS) with pembrolizumab. This exploratory analysis extends follow-up to approximately five years to assess the durability of benefit and long-term safety.
Study Design and Participants
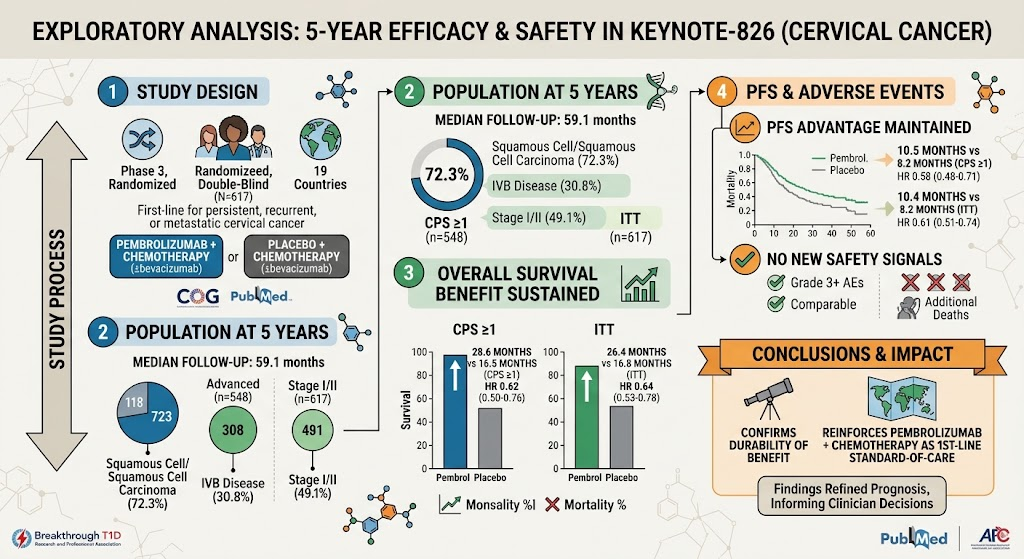
This ad hoc analysis included 617 female patients from 151 sites across 19 countries. The median age at baseline was 51 years (range 22–82), with nearly half presenting with Stage I/II disease and about 31% with Stage IVB. Histologically, the majority (72.3%) had squamous cell carcinoma or squamous cell carcinoma variants. Patients were randomized between November 2018 and January 2020. The median follow-up for this analysis was 59.1 months, roughly 20 months beyond the final previously reported analysis.
Treatment Regimen
Treatment arms consisted of pembrolizumab 200 mg administered intravenously every three weeks for up to 35 cycles combined with platinum-based chemotherapy (cisplatin or carboplatin), with or without bevacizumab, versus placebo with the same chemotherapy backbone. The addition of bevacizumab, an anti-angiogenesis agent targeting vascular endothelial growth factor (VEGF), was at the investigator’s discretion.
Key Outcomes: Progression-Free and Overall Survival
The primary efficacy endpoints were progression-free survival and overall survival. At five years, patients receiving pembrolizumab plus chemotherapy maintained a significant survival advantage compared to chemotherapy alone.
For patients with a programmed cell death ligand 1 (PD-L1) combined positive score (CPS) of at least 1, the median overall survival was 28.6 months (interquartile range [IQR] 12.3 to not reached) versus 16.5 months (IQR 9.0–40.5) for the placebo group, corresponding to a hazard ratio (HR) of 0.62 (95% confidence interval [CI] 0.50–0.76). In the intention-to-treat population, median overall survival was 26.4 months (IQR 12.0 to not reached) versus 16.8 months (IQR 9.1–40.1) respectively, with an HR of 0.64 (95% CI 0.53–0.78).
Progression-free survival improvements mirrored overall survival findings. For CPS ≥1 patients, median PFS was 10.5 months (IQR 6.2 to not reached) versus 8.2 months (IQR 4.2–17.1); HR 0.58 (95% CI 0.48–0.71). The intention-to-treat population showed similar benefit, with median PFS of 10.4 months (IQR 6.2 to not reached) versus 8.2 months (IQR 4.3–15.5); HR 0.61 (95% CI 0.51–0.74).
Safety and Tolerability
No new safety signals emerged during extended follow-up. Importantly, no additional deaths related to treatment-emergent adverse events have occurred since the prior final analysis. The known safety profile of pembrolizumab combined with chemotherapy remained consistent, with manageable immune-related adverse events and chemotherapy-associated toxicities as expected.
Clinical Implications
The five-year data from KEYNOTE-826 validate the sustained clinical benefit of pembrolizumab addition to platinum-based chemotherapy in advanced cervical cancer. Notably, the enduring improvement in overall survival supports pembrolizumab as a new first-line standard of care option for persistent, recurrent, or metastatic cervical cancer, particularly for patients expressing PD-L1 (CPS ≥1).
These findings underscore the importance of integrating immunotherapy into treatment algorithms and highlight the necessity for ongoing surveillance of long-term safety profiles in oncology practice. Furthermore, the broad international participation enhances the generalizability of results across diverse patient populations.
Conclusion
This extended exploratory analysis of the KEYNOTE-826 randomized phase 3 trial demonstrates that pembrolizumab, when combined with platinum-based chemotherapy (with or without bevacizumab), provides a durable survival benefit in previously untreated patients with advanced cervical cancer without new safety concerns. These data reinforce pembrolizumab plus chemotherapy as a first-line treatment standard, offering hope for improved outcomes in this challenging disease setting.
Trial Registration
ClinicalTrials.gov Identifier: NCT03635567
References
Hasegawa K, Colombo N, Tewari KS, et al. Pembrolizumab Plus Chemotherapy for Cervical Cancer: An Exploratory Analysis of the KEYNOTE-826 Randomized Clinical Trial. JAMA Oncology. 2026 Sep 10; PMID: 42720936. Available at: https://pubmed.ncbi.nlm.nih.gov/42720936/


