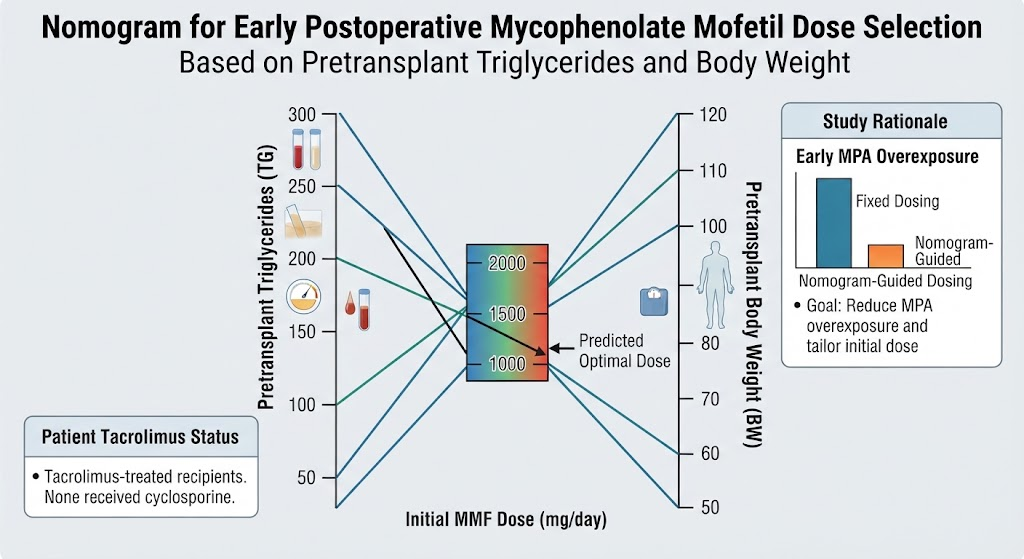
A nomogram incorporating pretransplant triglyceride levels and body weight was developed to personalize early postoperative mycophenolate mofetil (MMF) dosing in kidney transplant recipients.
The retrospective study of 116 tacrolimus-treated kidney transplant recipients demonstrated that the nomogram potentially reduces the rate of MPA overexposure before therapeutic drug monitoring (TDM) is initiated.
While the nomogram showed directional benefits in dose adjustment, findings were dependent on pharmacokinetic assumptions and require prospective validation before clinical adoption.
Study Background
Kidney transplantation remains the optimal treatment for end-stage renal disease, improving patient survival and quality of life. Immunosuppressive regimens commonly include mycophenolate mofetil (MMF), which metabolizes to mycophenolic acid (MPA) — the active immunosuppressive molecule. Adequate MPA exposure is critical to prevent acute rejection and optimize graft survival. However, early postoperative MPA exposure is highly variable due to differences in absorption, metabolism, and concomitant medications such as tacrolimus. Fixed initial MMF dosing carries risks of under- or overexposure, the latter potentially leading to adverse events such as infections or gastrointestinal toxicity.
Therapeutic drug monitoring (TDM) is the gold standard to tailor MMF dosing based on MPA area under the concentration-time curve (AUC). However, in the immediate posttransplant period, TDM may not be promptly available. Thus, clinicians require practical tools to inform initial MMF dosing that reduce overexposure risk. Identifying easily measurable pretransplant clinical variables that can predict early MPA exposure and guide dosing could improve outcomes and safety.
Study Design
This single-center retrospective study analyzed 117 consecutive adult kidney transplant recipients treated with tacrolimus-based immunosuppression, excluding those on cyclosporine, from whom 116 had full MPA concentration profiles. The investigators sought predictors of MPA exposure using pretransplant clinical variables, focusing primarily on triglyceride (TG) levels and body weight.
Based on modeling MMF dose, body weight, and triglycerides, a nomogram was constructed to guide early postoperative MMF dosing standardized to a baseline dose of 1500 mg/day. The nomogram provided a three-level dosing recommendation: 1000 mg, 1500 mg, or 2000 mg daily. Dose-proportional simulations assessed the impact on MPA AUC categories (60 mg·h/L).
Robustness was tested through false discovery rate (FDR) correction for multiplicity, internal validation, and alternative pharmacokinetic assumptions.
Key Findings
Among the 116 analyzed recipients, observed MPA AUC values fell into three categories: 12.1% underexposed (60 mg·h/L). Triglycerides remained statistically significant after dose-adjusted FDR correction (q=0.047), indicating an association with MPA exposure.
Simulation applying the nomogram’s dosing recommendations yielded adjusted proportions of 14.7% underexposed, 54.3% within target, and 31.0% overexposed recipients. This reflected a reduction in overexposure of approximately 10.4 percentage points (95% bootstrap CI -18.1 to -3.4). Across different pharmacokinetic assumptions, the overexposure reduction effect ranged from -1.7 to -10.4 percentage points, though improvements in target attainment were not consistently robust.
Internal validation supported a directionally consistent reduction in overexposure, albeit with some imprecision. The model did not replace the need for clinical judgement or formal TDM but rather served as a hypothesis-generating tool for early MMF dose individualization.
Expert Commentary
This study addresses a critical gap in personalized immunosuppression management immediately after kidney transplantation, a phase when drug monitoring data are often unavailable. Triglycerides, as a novel biomarker correlating with MPA exposure, may reflect changes in drug metabolism or distribution related to lipid profiles. Body weight-based dosing aligns with pharmacokinetic principles and clinical intuition.
The reduction in simulated overexposure is clinically relevant because supratherapeutic MPA levels contribute to toxicity risks that can impact graft function and patient morbidity. However, the reliance on retrospective pharmacokinetic modeling and the assumption-dependent nature of results necessitate cautious interpretation.
Limitations include the single-center design, lack of external validation, and potential confounding factors unaccounted for. Prospective studies are essential to confirm the nomogram’s predictive accuracy and determine its impact on clinical outcomes such as rejection rates and adverse events.
Current guidelines emphasize the importance of therapeutic drug monitoring but seldom provide concrete dosing adjustments before TDM availability. Incorporating a simple, readily accessible tool like this nomogram could streamline early immunosuppression management pending further validation.
Conclusion
The triglyceride- and body weight-based nomogram offers a promising approach to guide early postoperative MMF dosing in kidney transplant recipients, potentially reducing MPA overexposure before TDM is initiated. While the model showed consistent directionality in simulations, its performance varies with pharmacokinetic assumptions, and it should complement rather than replace therapeutic drug monitoring and clinical judgement.
Future prospective external validation studies are warranted to establish its reliability and clinical utility. If confirmed, this nomogram could become a practical adjunct in immunosuppressive dosing strategies, improving safety and graft outcomes in the critical early posttransplant period.
Funding and Clinical Trials
The original study was supported by institutional research funds at the single transplant center. No clinical trial registration number was reported.
References
Makiyama T, Kinoshita K, Morimoto A, Maruyama M. Triglyceride- and Body Weight-Based Nomogram for Early Postoperative Mycophenolate Mofetil Dose Selection Following Kidney Transplantation. Clin Transplant. 2026 Oct;40(10):e70696. PMID: 42867487.
Additional relevant literature:
1. Staatz CE, Tett SE. Clinical pharmacokinetics and pharmacodynamics of mycophenolate in solid organ transplant recipients. Clin Pharmacokinet. 2004;43(13):841-885.
2. Kuypers DR. Therapeutic drug monitoring of mycophenolic acid in kidney transplant recipients: why, when, and how to do it? Drugs. 2012;72(9):1151-1171.
3. Borrows R, et al. Clinical pharmacokinetics and therapeutic drug monitoring of mycophenolate mofetil in transplant patients. Transplantation. 2002;73(5):681-691.