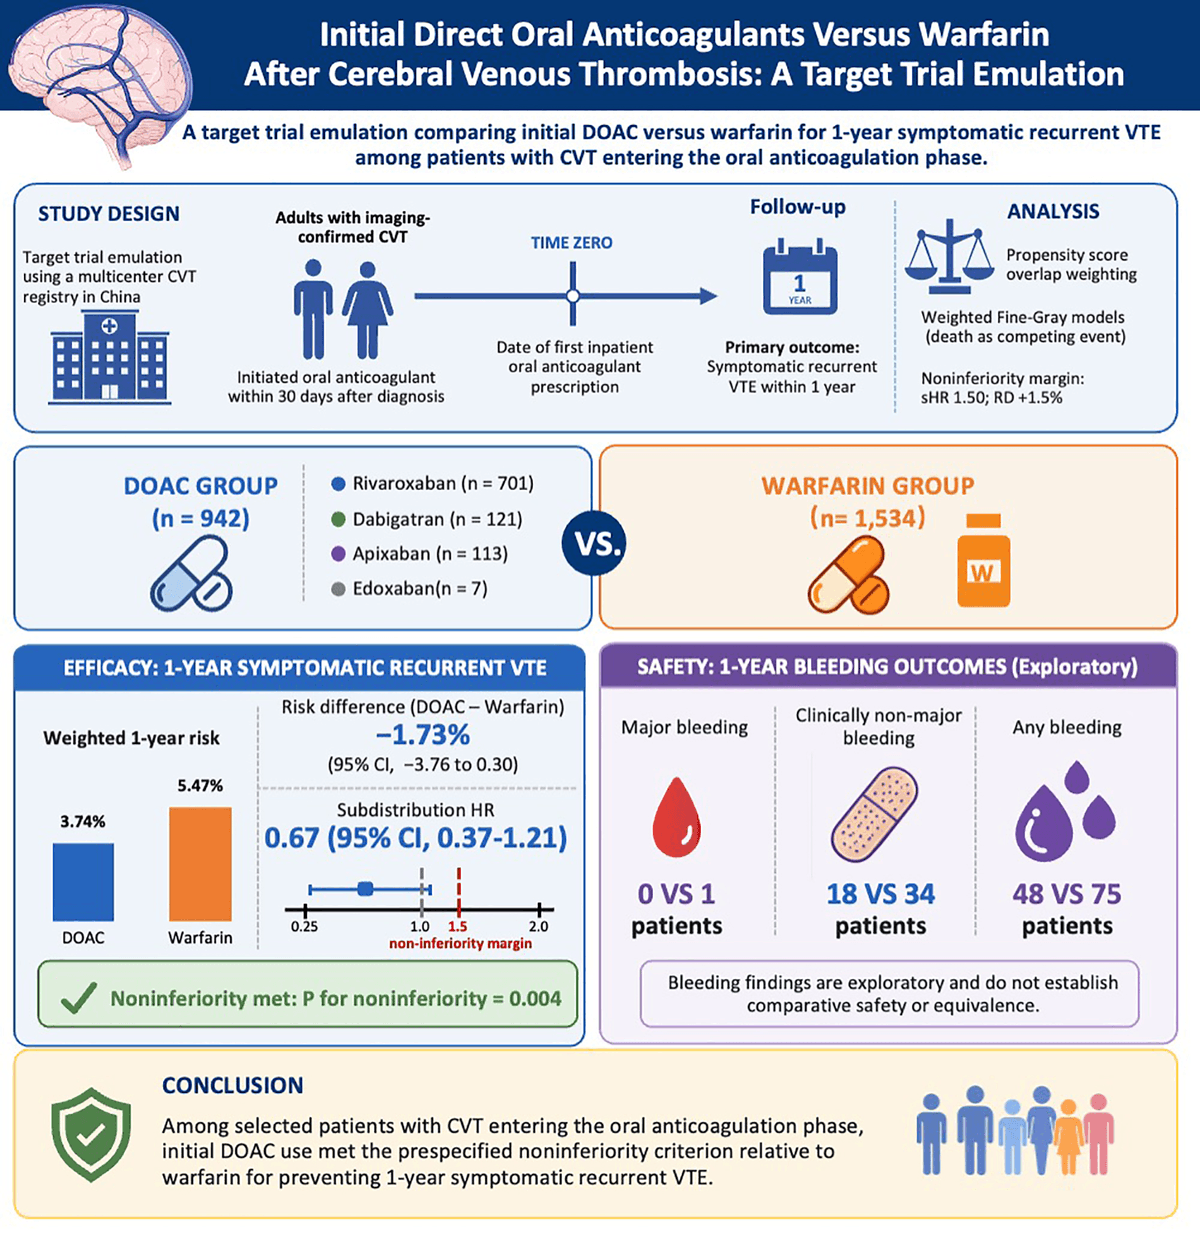
Direct oral anticoagulants (DOACs) are noninferior to warfarin for preventing 1-year symptomatic recurrent venous thromboembolism (VTE) after cerebral venous thrombosis (CVT).
A large registry-based target trial emulation included 2476 Chinese adults with imaging-confirmed CVT initiating anticoagulation within 30 days of diagnosis.
The overlap-weighted analysis showed a 1-year recurrent VTE risk of 3.74% with DOACs versus 5.47% with warfarin, corresponding to a risk difference favoring DOACs.
Exploratory bleeding outcomes suggested numerically fewer clinical nonmajor and any bleeding events with DOACs, though conclusions on safety are premature.
Study Background
Cerebral venous thrombosis (CVT) is a rare form of stroke characterized by thrombosis of the cerebral venous sinuses or cortical veins, leading to intracranial hypertension, venous infarcts, or hemorrhage. Anticoagulation is the cornerstone of treatment, aimed at preventing thrombus propagation and recurrent events. Historically, vitamin K antagonists such as warfarin have been standard for extended anticoagulation following CVT. However, management can be challenging due to warfarin’s narrow therapeutic window, frequent monitoring requirements, and dietary interactions.
Direct oral anticoagulants (DOACs) — including rivaroxaban, dabigatran, apixaban, and edoxaban — have more predictable pharmacodynamics and fewer monitoring requirements and are increasingly prescribed after CVT, despite limited randomized evidence. Whether DOACs provide comparable efficacy and safety to warfarin for preventing recurrent venous thromboembolism (VTE) after CVT remains uncertain, especially over extended follow-up.
The study by Zhong et al. addresses this clinical uncertainty by emulating a target trial using a large, bidirectional multicenter Chinese CVT registry to compare initial DOACs versus warfarin for prevention of symptomatic recurrent VTE at 1 year.
Study Design
This was a registry-based target trial emulation leveraging a cerebral venous thrombosis registry comprising retrospective data (2015–2022) and prospective data collection (2023–2025) from multiple centers in China. Eligible patients were adults diagnosed with imaging-confirmed CVT who initiated either a DOAC or warfarin within 30 days of diagnosis. Time zero was defined as the date of first oral anticoagulant prescription.
The primary efficacy endpoint was symptomatic recurrent VTE within 1 year, including recurrent CVT or other venous thromboembolic events. Death was treated as a competing risk in analyses. Propensity score overlap weighting was applied to balance baseline characteristics between treatment groups, and weighted Fine-Gray models estimated the subdistribution hazard ratio (SHR) for recurrent VTE, accounting for competing mortality.
Critically, a prespecified noninferiority margin was set as an absolute increase of 1.5 percentage points in 1-year recurrent VTE risk—reflecting about a 50% relative risk margin—to assess whether DOACs were not clinically worse than warfarin.
Key Findings
A total of 2476 eligible patients were analyzed: 942 initiated DOACs (majority rivaroxaban) and 1534 initiated warfarin. Baseline characteristics were well balanced after overlap weighting.
Within 1 year, symptomatic recurrent VTE occurred in 36 patients on DOACs versus 73 on warfarin. The overlap-weighted 1-year recurrence risks were 3.74% (DOAC) versus 5.47% (warfarin), yielding a risk difference of -1.73 percentage points (95% CI, -3.76 to 0.30). This estimate suggests a nonsignificant trend toward lower recurrence with DOACs.
The subdistribution hazard ratio for DOAC versus warfarin was 0.67 (95% CI, 0.37 to 1.21; P=0.184), indicating no statistically significant difference in recurrent VTE risk but meeting the stringent noninferiority criterion (P for noninferiority=0.004).
Regarding bleeding, major bleeding events were very rare, with none in the DOAC group and one in the warfarin group. Clinical nonmajor bleeding occurred in 1.9% (18/942) of DOAC patients and 2.2% (34/1534) of warfarin patients. Any bleeding events were reported in 5.1% (48/942) versus 4.9% (75/1534) respectively. These bleeding outcomes were exploratory, underpowered, and should not be taken as definitive comparative safety evidence.
Subgroup analyses and sensitivity checks were not detailed in the abstract but may be presented in the full publication.
Expert Commentary
This large real-world study, using rigorous target trial emulation methodology, provides important evidence supporting the use of DOACs in CVT patients, a population traditionally treated with warfarin. The results align with recent smaller randomized trials and observational studies favoring DOACs for similar indications. The noninferiority margin chosen is clinically justified and reflects pragmatic acceptance of a modest potential risk change.
The study’s strengths include its large sample size, multicenter nature, modern analytic methods including propensity score overlap weighting, and competing risk adjustment. However, as a registry analysis, residual confounding cannot be entirely excluded. The low rate of major bleeding limits conclusions on safety, and longer-term outcomes remain to be elucidated.
Current guidelines increasingly acknowledge DOACs as an alternative to warfarin for CVT, especially in patients with contraindications or intolerance to warfarin. This study adds supportive evidence for DOAC initial use, potentially facilitating broader adoption and simplifying management.
Biologically, DOACs’ direct thrombin or factor Xa inhibition mechanisms may offer more targeted anticoagulation without the variability seen with warfarin’s vitamin K antagonism. Their predictable pharmacology and fewer drug-food interactions improve therapeutic adherence.
Conclusion
In patients with cerebral venous thrombosis initiating oral anticoagulation, direct oral anticoagulants demonstrate noninferior efficacy compared to warfarin in preventing 1-year symptomatic recurrent venous thromboembolism. This evidence supports DOACs as a valid initial anticoagulant strategy in this population.
Further research is needed to clarify bleeding risk profiles, long-term safety, and efficacy in diverse ethnic populations and CVT subtypes. The findings encourage clinicians to consider DOACs for CVT treatment, balancing individual patient factors and preferences.
Funding and Clinical Trials Registration
The study was supported by Chinese multicenter research collaborations; specific funding sources were not detailed in the abstract. The clinical trial registration was not reported.
References
1. Zhong J, Vellema J, Yu M, Dong Y, Xu Y, Zhang W, et al. Initial Direct Oral Anticoagulants Versus Warfarin After Cerebral Venous Thrombosis: A Target Trial Emulation. Stroke. 2026 Oct 19.
2. Ferro JM, Canhão P, Stam J, Bousser MG, Barinagarrementeria F; ISCVT Investigators. Prognosis of cerebral vein and dural sinus thrombosis: results of the International Study on Cerebral Vein and Dural Sinus Thrombosis (ISCVT). Stroke. 2004 Mar;35(3):664-70.
3. Einhäupl KM, Stam J, Bousser MG, De Bruijn SF, Ferro JM, Martinelli I, Masuhr F, European Federation of Neurological Societies. EFNS guideline on the treatment of cerebral venous and sinus thrombosis. Eur J Neurol. 2010 Oct;17(10):1229-35.
4. Coutinho JM, de Bruijn SF, de Veber G, Stam J. Cerebral venous thrombosis in women. Stroke. 2009 Aug;40(8):2356-61.