

Highlight
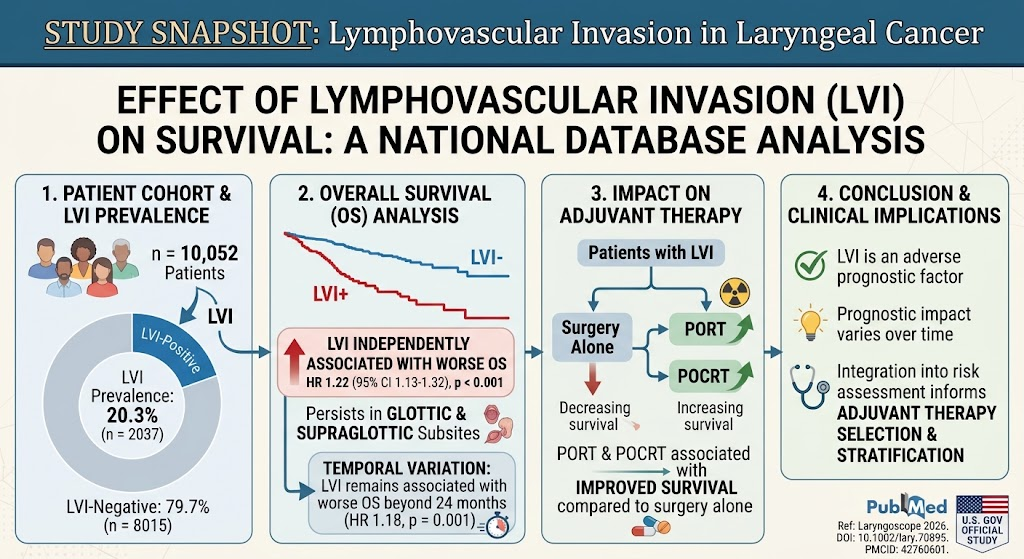
This large national database analysis demonstrates that lymphovascular invasion (LVI) is an independent adverse prognostic factor in laryngeal squamous cell carcinoma (LSCC). The presence of LVI significantly reduces overall survival (OS), with the prognostic impact persisting beyond two years post-surgery. Furthermore, adjuvant therapies such as postoperative radiotherapy (PORT) and combined chemoradiotherapy (POCRT) improve survival outcomes in patients with LVI compared to surgery alone.
Study Background
Laryngeal squamous cell carcinoma (LSCC) constitutes a significant subset of head and neck malignancies, with prognosis primarily dependent on tumor stage, subsite, and treatment modality. Lymphovascular invasion (LVI), defined as the presence of cancer cells within lymphatic or blood vessels, is a histopathological marker often reported but its independent prognostic value in LSCC remains unclear. While LVI is recognized as a risk factor in other head and neck sites, its role in survival prediction and influence on therapeutic decisions in laryngeal cancer has not been conclusively established. This gap underlines the need for large-scale analyses to clarify the clinical importance of LVI and guide postoperative management.
Study Design
This retrospective cohort study utilized a national cancer database identifying adult patients diagnosed with LSCC who underwent definitive surgical resection. Inclusion criteria required absence of distant metastases and exclusion of patients receiving preoperative radiotherapy, systemic therapy, or those with non-squamous histology to minimize confounding. Data analyzed included demographics, comorbidity indices, tumor stage, anatomical subsite (glottic versus supraglottic), surgical margin status, treatment facility type, and adjuvant treatment modalities.
The primary endpoint was overall survival (OS). The association between LVI and OS was assessed using multivariable Cox proportional hazards regression models controlling for relevant clinical and pathological covariates. Landmark analyses were performed to explore temporal variations in LVI’s prognostic impact. Secondary analyses evaluated survival differences among patients with LVI stratified by receipt of postoperative radiotherapy (PORT) or combined postoperative chemoradiotherapy (POCRT) versus surgery alone.
Key Findings
A total of 10,052 patients met inclusion criteria, with lymphovascular invasion identified in 20.3% (n=2,037). The mean follow-up duration was approximately 70 months. After rigorous adjustment for confounders, LVI was independently associated with worse overall survival (hazard ratio [HR] 1.22, 95% confidence interval [CI] 1.13–1.32, p<0.001). This adverse prognostic effect was consistent across the major laryngeal subsites, including glottic tumors (HR 1.30, p=0.001) and supraglottic tumors (HR 1.26, p<0.001).
Landmark analyses revealed temporal variation in the survival effect of LVI. Specifically, the negative prognostic impact persisted beyond 24 months after surgery (HR 1.18, p=0.001), suggesting that LVI is linked to both early and late mortality risks.
Among patients who exhibited LVI, the receipt of adjuvant therapies demonstrated survival benefits. Both PORT and POCRT were associated with significantly improved overall survival when compared to surgery alone, supporting the role of intensified postoperative treatment in this high-risk subgroup.
Expert Commentary
The study’s robust sample size and comprehensive multivariable adjustment strengthen the credibility of its conclusions. The identification of LVI as an independent prognostic marker corroborates findings in other head and neck cancers and validates its importance in LSCC. Notably, the persistence of LVI’s influence beyond 2 years post-resection highlights that LVI is not merely a surrogate for aggressive early disease but also an indicator of potential late recurrence or metastatic risk.
These findings emphasize the need for routine, standardized reporting of LVI in pathological assessments. Incorporating LVI into postoperative risk stratification algorithms may refine patient selection for adjuvant therapy, potentially improving long-term outcomes. However, limitations inherent to retrospective database analyses, including possible residual confounding and lack of detailed information on radiation dosing or chemotherapy regimens, should temper overinterpretation. Future prospective studies and randomized trials could more definitively establish optimal adjuvant treatment strategies for LVI-positive LSCC patients.
Biologically, LVI denotes tumor cell access to lymphatic and vascular networks, facilitating regional and distant dissemination. This emphasizes its mechanistic plausibility as a marker of metastatic potential and poor prognosis.
Conclusion
This extensive national database analysis identifies lymphovascular invasion as an adverse, independent prognostic factor in surgically treated laryngeal squamous cell carcinoma. Its presence correlates with reduced overall survival, with prognostic effects sustained over time. Importantly, patients with LVI benefit from adjuvant radiotherapy or combined chemoradiotherapy, underscoring LVI’s potential utility in guiding postoperative treatment decisions. Integration of LVI status into routine pathological reporting and postoperative risk assessment frameworks is warranted to optimize personalized therapeutic approaches in LSCC.
Funding and ClinicalTrials.gov
No specific funding sources were reported for this cohort study. It was conducted through analysis of a national cancer database. The study protocol and data source details are not linked to any registered clinical trial.
References
1. Carvalho AL, Nishimoto IN, Califano JA, Kowalski LP. Trends in incidence and prognosis for head and neck cancer in the United States: a site-specific analysis of the SEER database. Int J Cancer. 2005;114(5):806–816.
2. Edge SB, Compton CC. The American Joint Committee on Cancer: the 7th edition of the AJCC cancer staging manual and the future of TNM. Ann Surg Oncol. 2010;17(6):1471–1474.
3. Lydiatt WM, Patel SG, O’Sullivan B, et al. Head and neck cancers-major changes in the American Joint Committee on Cancer eighth edition cancer staging manual. CA Cancer J Clin. 2017;67(2):122–137.
4. Lydiatt WM, Patel SG. The prognostic importance of lymphovascular invasion in head and neck squamous cell carcinoma. J Natl Compr Canc Netw. 2012;10(10):1279–1283.
5. Machtay M, Moughan J, Trotti A, et al. Factors associated with severe late toxicity after concurrent chemoradiation for locally advanced head and neck cancer: an RTOG analysis. J Clin Oncol. 2008;26(21):3582–3589.
6.Porto-Gutierrez F, Kacin A, Campbell B, Montanez-Azcarate V, Syed Z, Jalisi S. Lymphovascular Invasion Predicts Survival in Laryngeal Cancer: A National Database Analysis. Laryngoscope. 2026 Sep 18. doi: 10.1002/lary.70895. Epub ahead of print. PMID: 42760601.


