

Patient Information
A 21-year-old woman presented with primary amenorrhea and absence of vaginal canalization. She had normal secondary sexual characteristics including breast development and pubic hair, with no prior relevant medical or surgical history. The patient reported no cyclical abdominal pain or urinary symptoms. Physical examination revealed a well-developed vulva but a vaginal dimple with absence of a palpable vaginal canal. She was otherwise healthy with unremarkable systemic examination.
Diagnosis
Laboratory evaluation confirmed a normal 46,XX karyotype. Hormonal profile demonstrated normal ovarian function (normal follicle-stimulating hormone, luteinizing hormone, estradiol levels). Imaging via pelvic ultrasound and MRI revealed absence of the uterus and proximal vagina with normally formed ovaries. These findings were consistent with Müllerian agenesis syndrome (Mayer-Rokitansky-Küster-Hauser syndrome), a congenital disorder characterized by uterine and vaginal agenesis despite normal ovarian function and secondary sexual characteristics.
Differential Diagnosis
Other causes of primary amenorrhea and vaginal agenesis considered included:
– Androgen insensitivity syndrome: excluded by a normal female karyotype (46,XX vs 46,XY in AIS).
– Transverse vaginal septum or imperforate hymen: ruled out by imaging findings and clinical examination.
– Congenital adrenal hyperplasia or other endocrine disorders: ruled out by hormonal profile and absence of virilization.
– Hypogonadotropic hypogonadism: inconsistent with normal secondary sexual characteristics and hormone levels.
Treatment and Management
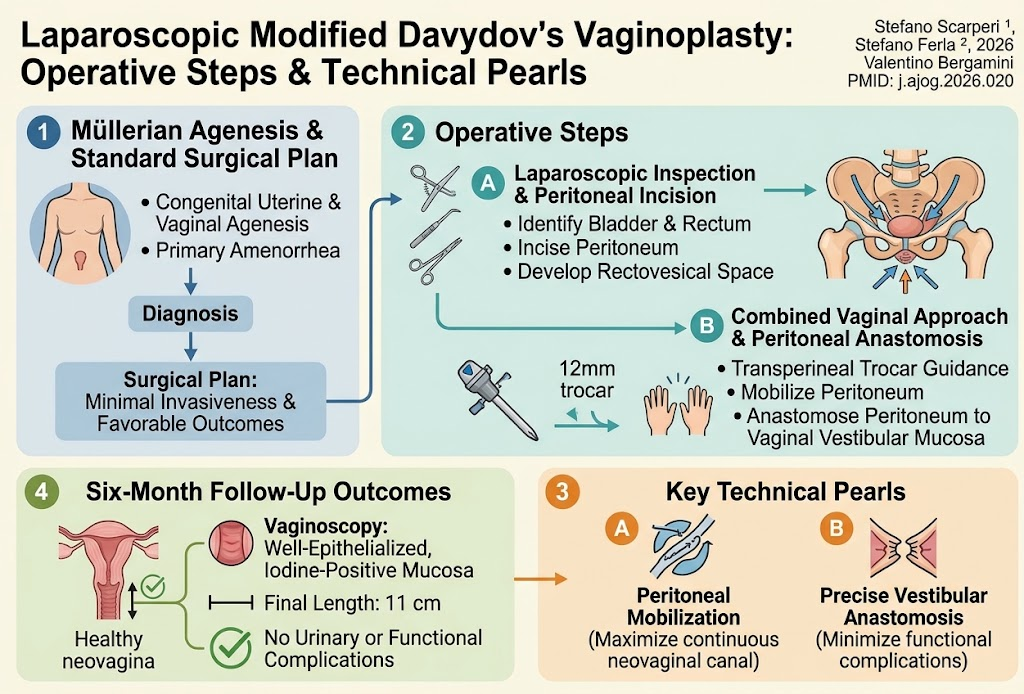
Given the patient’s anatomical findings and desire for vaginal reconstruction, a surgical approach using a modified laparoscopic Davydov technique was chosen. Preoperative counseling covered surgical risks, postoperative care, and expectations.
Operative steps included:
1. A combined laparoscopic and vaginal approach was utilized under general anesthesia.
2. Initial laparoscopic inspection confirmed absent uterus and defined pelvic anatomy.
3. The peritoneum between the bladder and rectum (the recto-vesical space) was incised laparoscopically to develop the neovaginal canal.
4. The mobilized peritoneum was prepared laparoscopically to be used as a neovaginal lining.
5. A 12-mm trocar was inserted transperineally through the vaginal dimple to facilitate anastomosis between the mobilized peritoneal flap and the vaginal vestibular mucosa, thus creating a continuous, epithelial-lined neovagina.
6. Appropriate hemostasis was secured, and no intraoperative complications occurred.
Postoperatively, the patient was advised on use of dilators and hygiene to maintain neovaginal patency and epithelialization.
Outcome and Prognosis
At 6-month follow-up, the patient underwent vaginoscopy revealing a well-epithelialized, iodine-positive mucosal lining within the neovaginal canal measuring 11 cm in length. No urinary tract or bowel complications were noted. The patient reported satisfactory functional outcomes, with an absence of dyspareunia and maintained vaginal patency. Psychological wellbeing was also reported to have improved, emphasizing the positive psychosocial impact.
Discussion
Müllerian agenesis syndrome poses a challenging congenital anomaly with significant functional and psychological consequences. Vaginal reconstruction aims to provide anatomical and sexual function while minimizing complications. While nonsurgical dilation remains first-line for some, surgical options are often required in patients where non-surgical management is not feasible or effective.
The laparoscopic Davydov technique, initially described in the 1960s and refined with minimally invasive approaches, offers distinct advantages: it uses the patient’s own peritoneum to line the neovagina, which favors natural epithelialization and lubrication, and its minimally invasive nature reduces morbidity and recovery time.
This case illustrates a standardized surgical technique emphasizing critical anatomical landmarks such as the recto-vesical peritoneal space and the strategic use of a transperineal trocar to facilitate precise anastomosis, optimizing outcomes. Our experience underscores the importance of comprehensive preoperative evaluation, patient counseling, and meticulous surgical technique.
The favorable functional results with no complications at 6 months align with existing literature supporting laparoscopic modified Davydov vaginoplasty as a reliable approach. Future studies with larger cohorts and longer follow-up will further consolidate evidence on the efficacy and durability of this technique.
References
1. Scarperi S, Ferla S, Raimondo D, Bergamini V. Laparoscopic modified Davydov’s technique for vaginoplasty: operative steps and technical pearls. Am J Obstet Gynecol. 2026 Sep 18; PMID: 42759742.
2. Acién P, Acién M. Mayer-Rokitansky-Küster-Hauser syndrome: Anatomical, clinical, and molecular genetics. Orphanet J Rare Dis. 2007;2:13.
3. Davydov SN. A method of plastic surgery of the vagina [in Russian]. Akush Ginekol (Mosk). 1969;48(4):555-559.
4. Raine-Fenning NJ, Wardle S, Smith A, et al. Current and emerging techniques for vaginal reconstruction in the patient with vaginal agenesis. Obstet Gynecol Surv. 2014 Aug;69(8):502-510.
This standardized approach and attention to technical details can help optimize functional and psychosocial outcomes for women affected by this complex congenital anomaly.


