

Highlight
1. Dose escalation of oral antihypertensive medication during expectant management of early-onset preeclampsia with severe features is associated with progressively increased maternal risk.
2. Both the number and rate of antihypertensive dose escalations and use of intravenous hypertension control correlate with adverse maternal outcomes.
3. Treatment intensity measured by Hypertension Daily Dose (HDD) is linked to maternal risk but does not demonstrate a clear dose-response.
4. Neonatal outcomes remain unaffected across different dose escalation categories, underscoring the complexity of maternal risk without corresponding neonatal compromise.
Study Background
Early-onset preeclampsia with severe features, occurring before 34 weeks of gestation, poses a significant challenge in obstetric care due to its association with increased maternal morbidity and mortality. Expectant management to prolong pregnancy aims to improve neonatal outcomes but risks progression of maternal disease. Antihypertensive therapy is a cornerstone to control severe hypertension that can precipitate catastrophic maternal complications such as stroke, pulmonary edema, or multi-organ dysfunction syndrome. Although oral and intravenous antihypertensive medications are routinely escalated as blood pressure worsens, the prognostic significance of escalating antihypertensive treatment during expectant management has been insufficiently characterized. Understanding this relationship may identify dynamic markers for maternal risk stratification and guide clinical decision-making.
Study Design
This retrospective cohort study analyzed singleton pregnancies complicated by early-onset preeclampsia with severe features, managed expectantly between 23 weeks 0 days and 33 weeks 5 days gestation at a single level IV referral center from January 2016 through December 2025. The primary exposure variable was the number of oral antihypertensive medication dose escalations during expectant management. Secondary exposures included the rate of dose escalation, the overall treatment intensity quantified by Hypertension Daily Dose (HDD), and intravenous (IV) antihypertensive medication pushes for urgent blood pressure control. The primary outcome was a composite of maternal adverse events including placental abruption, intrauterine fetal demise, acute kidney injury, pulmonary edema, myocardial infarction, HELLP syndrome (hemolysis, elevated liver enzymes, and low platelet count), disseminated intravascular coagulation, eclampsia, stroke, or maternal death.
Multivariable Poisson and linear regression models adjusted for potential confounders were applied to assess associations between antihypertensive treatment escalation and adverse maternal outcomes.
Key Findings
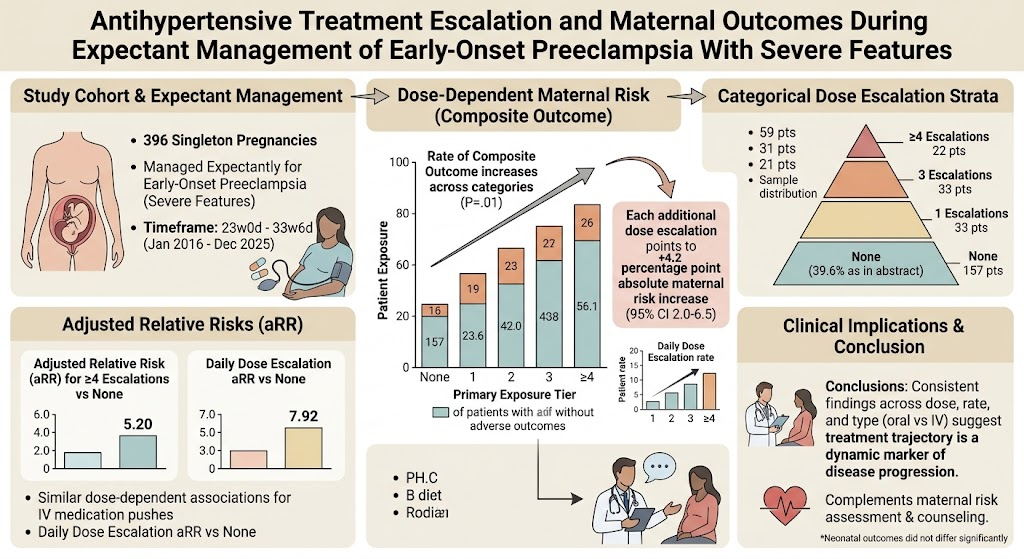
The cohort comprised 396 women undergoing expectant management. Among them, 39.6% had no oral antihypertensive dose escalation, while 25.2%, 21.2%, 8.3%, and 5.6% experienced 1, 2, 3, and ≥4 dose escalations, respectively. The incidence of composite maternal adverse outcomes showed a statistically significant stepwise increase across categories of dose escalation (P = .01).
Each additional oral antihypertensive dose escalation was associated with an absolute 4.2 percentage point increase in risk (95% CI, 2.0–6.5). Adjusted relative risks (aRR) for patients with 3 and ≥4 dose escalations compared to none were 4.07 (95% CI, 1.41–11.78) and 5.20 (95% CI, 1.81–14.90), respectively. Notably, daily dose escalation bore an even greater aRR of 7.92 (95% CI, 2.90–21.63), indicating that rapid escalation is a strong predictor of maternal complications.
Parallel analyses demonstrated that repeated administration of intravenous antihypertensive pushes also displayed a dose-dependent relationship with increased maternal morbidity. While higher HDD levels correlated with maternal risk, a clear dose-response relationship was not evident, possibly due to heterogeneous pharmacodynamics or timing of escalation.
Importantly, neonatal outcomes did not differ significantly across groups, suggesting that increased maternal risk with dose escalation is not directly mirrored by adverse neonatal outcomes within this study context.
Expert Commentary
This study provides valuable insight into the clinical course of early-onset severe preeclampsia managed expectantly. The incremental increase in maternal risk with each antihypertensive dose escalation highlights treatment trajectory as a potential real-time marker of disease progression. The findings align with pathophysiologic understanding that worsening hypertensive status indicates advancing endothelial dysfunction and organ involvement.
While causality cannot be inferred from this retrospective analysis, these robust associations underscore the need for vigilant maternal surveillance when antihypertensive dosing is intensified. The dissociation between maternal and neonatal outcomes warrants further investigation, especially considering the delicate balance between prolonging pregnancy and maternal safety.
Limitations include single-center design, potential confounding by indication, and lack of granular blood pressure measurements or adjunctive biomarkers. Nevertheless, these results may inform clinical guidelines and counseling by integrating treatment escalation patterns into maternal risk stratification models. Future prospective studies could clarify mechanistic links and refine therapeutic thresholds.
Conclusion
Antihypertensive treatment escalation during expectant management of early-onset preeclampsia with severe features is strongly associated with increased maternal adverse outcomes. The number and rapidity of dose escalations, along with emergent intravenous interventions, serve as dynamic indicators of maternal disease progression. Recognizing these patterns can enhance risk assessment and optimize timing of delivery decisions. Neonatal outcomes appear unaffected by antihypertensive treatment escalation in this cohort, highlighting the complexity of balancing maternal and fetal considerations. Further research is warranted to validate these findings and develop integrated management algorithms to improve both maternal and neonatal safety.
Funding and Clinical Trials Registration
The study was conducted at a single level IV referral center with no funding sources declared in the referenced publication. ClinicalTrials.gov registration details were not provided.
References
1. Bart Y, Doughan Z, Diab L, Zaki Moustafa AS, Sibai BM. Antihypertensive Treatment Escalation and Maternal Outcomes During Expectant Management of Early-Onset Preeclampsia With Severe Features. Am J Obstet Gynecol. 2026 Sep 18. PMID: 42759740.
2. Sibai BM. Management of severe preeclampsia/eclampsia. Am J Obstet Gynecol. 1990;163(5 Pt 1):1699-1707.
3. Magee LA, Pels A, Helewa M, Rey E, von Dadelszen P. Diagnosis, evaluation, and management of the hypertensive disorders of pregnancy. Pregnancy hypertension. 2014;4(2):105-145.
4. American College of Obstetricians and Gynecologists. Hypertension in Pregnancy. ACOG Practice Bulletin No. 222. Obstet Gynecol. 2020;135(2):e57-e70.
5. Tita AT, Szychowski JM, Boggess K, et al. Treatment of severe hypertension in pregnancy. Obstet Gynecol. 2013;122(4):875-884.


