

Highlight
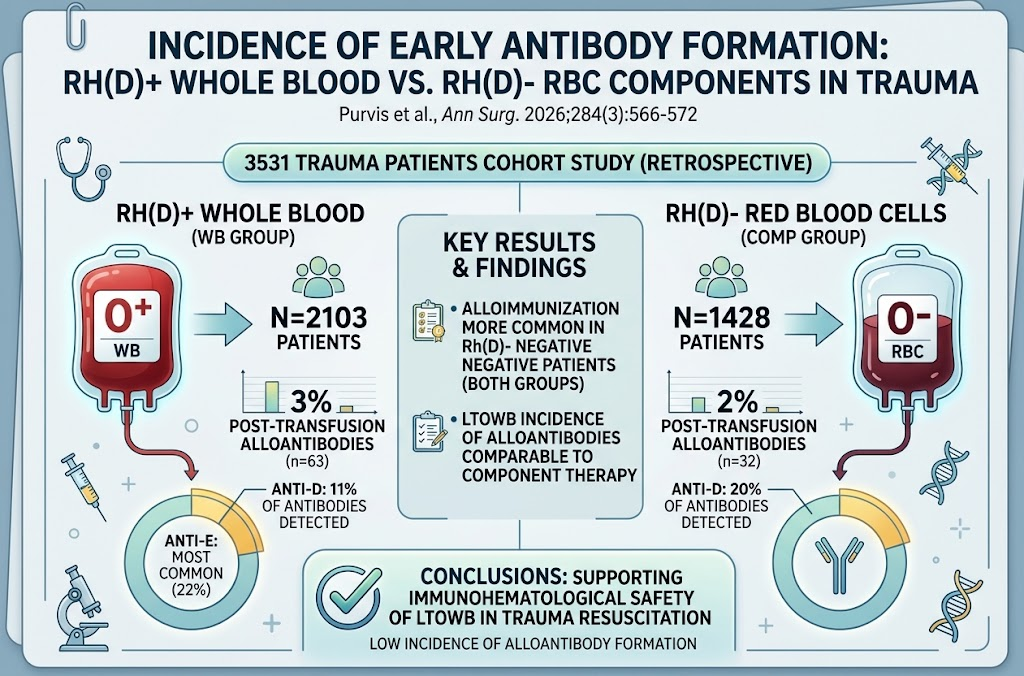
- This study reports a 3% alloimmunization incidence in trauma patients receiving Rh(D)+ low-titer group O whole blood (LTOWB), comparable to 2% in those receiving Rh(D)- component therapy.
- Anti-D antibodies represented a smaller fraction of alloantibodies post-LTOWB transfusion compared to component therapy (11% vs. 20%).
- Alloantibody formation was more frequent among Rh(D)-negative recipients in both cohorts.
- Findings support the immunohematological safety of LTOWB, underscoring its viability for rapid trauma resuscitation.
Study Background
Hemorrhagic shock from traumatic injury remains a leading cause of preventable death worldwide. Rapid, effective resuscitation with blood products is critical to restore circulating volume and hemostasis. Low-titer group O whole blood (LTOWB) has gained attention due to logistical advantages over component therapy (red blood cells, plasma, and platelets separately), including simplified administration and potential superior hemostatic efficacy. However, concerns about red blood cell (RBC) alloimmunization have tempered universal adoption, particularly the risk of anti-D antibody formation in Rh(D)-negative recipients exposed to Rh(D)-positive blood products.
Alloimmunization can complicate future transfusions by causing hemolytic transfusion reactions and complicating crossmatching. Yet the actual incidence of early alloantibody formation after LTOWB transfusion, especially under emergency trauma conditions, remains incompletely characterized.
Study Design
This retrospective cohort study analyzed trauma registry data from a single Level I trauma center collected between 2017 and 2023. Inclusion criteria were adult trauma patients (≥15 years) receiving uncrossmatched, emergency release blood transfusions either prehospital or shortly after admission. Patients were subdivided into:
- WB group: Those receiving Rh(D)+ low-titer group O whole blood (n=2103).
- COMP group: Those receiving Rh(D)- negative red blood cell component therapy exclusively (n=1428).
Antibody screening was conducted on admission and at approximately 72-hour intervals during hospitalization, enabling detection of early alloantibody formation. The primary endpoint was the incidence of new alloantibodies formed post-transfusion, with a focus on clinically significant RBC antibodies including anti-D.
Key Findings
Among 3531 trauma patients, the incidence of post-transfusion alloimmunization was 3.0% in the WB group and 2.2% in the COMP group, a difference that suggests comparable immunogenicity of LTOWB and component transfusion strategies in the acute trauma setting.
The pattern of alloantibodies differed between groups. In the WB cohort, anti-D antibodies constituted 11% of alloantibodies detected, with anti-E antibodies being most common (22%). In contrast, in the COMP group, anti-D accounted for 20% of detected antibodies, representing a higher relative frequency despite all blood products being RhD-negative. This may reflect baseline RhD-negative recipient immunologic responsiveness or a feature of antibody detection and small sample differences.
Consistently, alloantibody formation was more prevalent in Rh(D)-negative patients regardless of transfusion group, highlighting the immunologic risk associated with RhD antigen exposure or other alloantibody generation in this subset.
The overall low rate of alloimmunization in both groups supports the safety profile of emergency transfusion protocols employing LTOWB, which is beneficial given its logistical and hemostatic advantages over component therapy.
Clinical Significance and Safety
Early alloimmunization within days of trauma resuscitation can pose challenges for ongoing transfusion management. The study indicates that LTOWB does not impose a significantly increased immunologic risk for alloantibody formation when compared to standard component therapy, even with the presence of Rh(D)+ red cells.
This evidence bolsters confidence in broader LTOWB use in trauma, enabling resource optimization and potentially improved clinical outcomes without elevating alloimmunization complications.
Expert Commentary
The findings align with emerging literature emphasizing the feasibility and safety of LTOWB in trauma care. Dr. Brian Cotton, coauthor and trauma transfusion specialist, notes, “Our data provide reassuring evidence that the immunohematological risks of LTOWB are low, which supports its implementation where rapid massive transfusion is necessary.” This study addresses a critical knowledge gap and may influence future guidelines regarding trauma resuscitation strategies.
Limitations include its retrospective design and single-center setting, which may affect generalizability. Additionally, antibody screening focused on early alloimmunization, and longer-term immune responses were not evaluated. Further prospective, multicenter studies could validate these findings and characterize delayed alloantibody formation.
Conclusion
This large retrospective cohort analysis demonstrates that low-titer group O whole blood transfusion is associated with a low incidence of early red cell alloantibody formation, comparable to Rh(D)-negative component therapy in trauma patients. The modest risk of anti-D antibody formation among Rh(D)-negative recipients supports the immunohematological safety of LTOWB, endorsing its use as an effective and safe component of trauma resuscitation protocols.
These findings highlight important translational implications for trauma transfusion practice by mitigating alloimmunization concerns traditionally raised with LTOWB, thereby facilitating broader adoption of this resource-efficient and hemostatically advantageous resuscitation strategy.
Funding and ClinicalTrials.gov
The study was supported by institutional research funding at the Level I trauma center. No clinical trial registration number was reported, reflecting its retrospective cohort design.
References
- Purvis CD, Bavishi D, Rigi M, et al. What is the Incidence of Early Antibody Formation After Resuscitation of Hemorrhage? A Comparison of RH(D)+ Whole Blood and RH(D)- Red Blood Cells in 3531 Trauma Patients. Ann Surg. 2026;284(3):566-572. doi:10.1097/SLA.0000000000005232
- Spinella PC, Cap AP. Whole Blood for Resuscitation of Traumatic Hemorrhagic Shock in Civilian and Military Settings. Blood Adv. 2019;3(15):254-260.
- Howard JT, Ennis JK, Nelson MF, et al. Early Transfusion of Plasma, Platelets, and Red Blood Cells and Survival in Patients with Massive Traumatic Hemorrhage. JAMA Surg. 2020;155(7):619-627.


