

Highlight
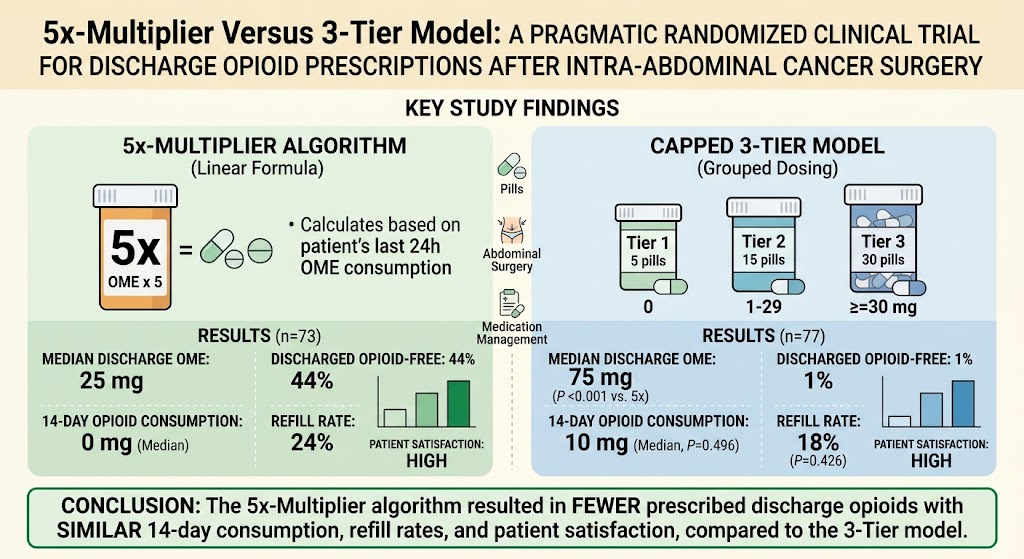
- The 5x-multiplier model prescribes fewer opioids at discharge than the 3-tier model after major intra-abdominal cancer surgery.
- Nearly half of patients in the 5x-multiplier group were discharged opioid-free versus 1% in the 3-tier group.
- There was no significant difference in 14-day post-discharge opioid consumption, refill rates, or patient satisfaction between models.
- Results support using individualized multipliers based on last 24-hour opioid use to optimize opioid stewardship and minimize excess pills.
Study Background
Opioid overprescribing after surgery contributes to the ongoing opioid crisis by increasing risk for persistent use, dependence, and diversion of unused medication. Abdominal cancer surgeries often require substantial postoperative pain control, leading to variable opioid prescribing behavior. Standardized prescribing models are needed to reduce excess opioids dispensed while maintaining adequate pain control and patient satisfaction. This trial compares two validated, pragmatic discharge opioid prescribing strategies to identify which achieves optimal balance.
Study Design
This single-center, pragmatic phase II randomized clinical trial enrolled 150 consenting adults undergoing open intra-abdominal cancer resections—including hepatectomy, pancreatectomy, nephrectomy, thoracoabdominal sarcoma resection, or ovarian cytoreduction—performed by 25 surgeons across five specialties between April and December 2024. Perioperative and discharge pain management incorporated a standardized nonopioid analgesic bundle.
Participants were randomized to one of two discharge opioid prescribing models: (1) the 5x-multiplier algorithm, dispensing opioids quantified as the last 24-hour in-hospital oral morphine equivalent (OME) of opioid use multiplied by five; or (2) a capped 3-tier model assigning fixed pill counts of 5, 15, or 30 based on last 24-hour OME strata of 0 mg, 1–29 mg, or ≥30 mg, respectively. Coprimary endpoints were the volume of opioids prescribed at discharge and reported 14-day postdischarge opioid consumption. Secondary outcomes included opioid refill rates, patient symptom inventories, and satisfaction scores.
Key Findings
The trial randomized 73 patients to the 5x-multiplier arm and 77 patients to the 3-tier arm. Patient demographics were balanced (52% female, median age 63 years). Surgical distribution was representative of major intra-abdominal cancer operations.
The median discharge opioid volume measured in oral morphine equivalents was significantly lower in the 5x-multiplier group at 25 mg versus 75 mg in the 3-tier group (P < 0.001). Notably, 44% of the 5x-multiplier patients were discharged opioid-free compared to only 1% in the 3-tier cohort.
Despite reduced prescribed opioids, median 14-day postdischarge opioid consumption did not differ significantly: 0 mg in the 5x-multiplier group versus 10 mg in the 3-tier group (P = 0.496). Refill rates were comparable at 24% versus 18% respectively (P = 0.426), aligning with historical patterns.
Patient satisfaction and symptom burden scores showed no statistical differences, affirming that lower opioid prescribing did not compromise perceived pain control or overall recovery experience.
Expert Commentary
This well-conducted pragmatic trial corroborates earlier observational work suggesting that discharge opioid prescriptions individualized by recent in-hospital opioid consumption can substantially reduce excess medication without impairing pain management. The 5x-multiplier model’s approach reconciles the need to minimize leftover opioids—a recognized source of diversion and misuse—while maintaining clinician flexibility based on patient opioid requirements.
Limitations include the single-center design and lack of blinding, which could influence prescribing and reporting behaviors. Additionally, longer-term opioid use and functional outcomes were not assessed. Nevertheless, the findings bear strong clinical relevance for surgeons and pain management teams striving to optimize postoperative opioid stewardship in oncologic surgery.
Conclusion
Intra-abdominal cancer surgery patients managed with the 5x-multiplier discharge opioid prescribing strategy receive significantly fewer opioids at discharge without increased consumption, refills, or dissatisfaction compared to a standard 3-tier model. This supports broader adoption of personalized opioid dosing algorithms based on opioid exposure metrics to reduce extraneous opioids and associated risks in surgical oncology.
Reference
Fields BC, Newhook TE, Lillemoe HA, Hierl AN, Rukundo I, Karam JA, Matin SF, Meyer LA, Li Z, Qiao W, Vauthey JN, Katz MHG, Tzeng CD; PROMOTE Consortium. 5x-Multiplier Versus 3-Tier Model: A Pragmatic Randomized Clinical Trial for Discharge Opioid Prescriptions After Intra-Abdominal Cancer Surgery. Ann Surg. 2026 Sep 1;284(3):647-657. doi: 10.1097/SLA.0000000000007115. Epub 2026 Jun 22. PMID: 42322127.


