

Highlight
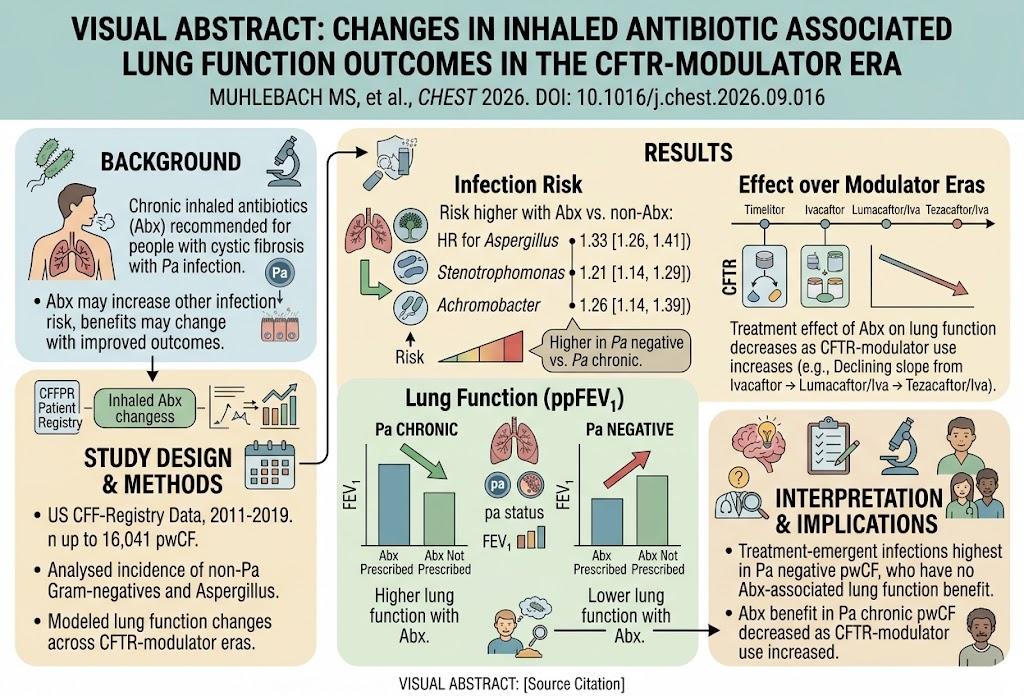
This study from the U.S. Cystic Fibrosis Foundation Patient Registry (2011-2019) demonstrates key dynamics in inhaled antibiotic treatment among people with cystic fibrosis (pwCF):
- Inhaled antibiotics improve lung function mainly in pwCF with chronic Pseudomonas aeruginosa infection, but this benefit has declined with the introduction of CFTR modulators.
- Those without chronic Pseudomonas infection face increased risk of opportunistic infections such as Aspergillus, Stenotrophomonas maltophilia, and Achromobacter when treated with inhaled antibiotics, without lung function improvement.
- The evolving CF care landscape, marked by increased age, better lung function, and widespread CFTR modulator use, influences the risk-benefit profile of inhaled antibiotics.
Study Background
Cystic fibrosis (CF) is a genetic disorder characterized by defective CFTR protein function, leading to thickened mucous secretions and chronic pulmonary infections. Persistent airway colonization with Pseudomonas aeruginosa (Pa) contributes to pulmonary decline and increased morbidity in CF. Chronic inhaled antibiotics are a cornerstone in managing Pa infection to reduce bacterial load and preserve lung function. However, inhaled antibiotics carry potential risks including selection for resistant organisms and opportunistic infections.
The recent advent of CFTR modulators, such as ivacaftor and combination therapies (lumacaftor/ivacaftor, tezacaftor/ivacaftor), has substantially improved lung function and altered the clinical course of CF. This paradigm shift raises the question whether the benefits and risks of chronic inhaled antibiotics remain consistent in the modulator era, especially across different Pa infection statuses.
Study Design and Methods
This retrospective cohort analysis utilized the U.S. Cystic Fibrosis Foundation Patient Registry data spanning 2011 to 2019. The study population included 12,000 to 16,041 pwCF annually, with data capturing demographic, clinical, and treatment parameters.
The main exposure was prescription of chronic inhaled antibiotics. Pa infection classification was based on Leeds criteria, categorizing patients as chronic Pa infection or Pa negative. The primary endpoints were:
- Incidence of secondary infections: Aspergillus species and Gram-negative bacteria such as Stenotrophomonas maltophilia and Achromobacter.
- Changes in lung function, measured by forced expiratory volume in 1 second (FEV1).
Analytical approaches included inverse probability treatment weighting to reduce confounding, survival modeling to estimate hazard ratios (HR) for secondary infections, and generalized estimating equations to assess lung function differences. The authors examined whether the inhaled antibiotic-associated lung function effect varied across three CFTR modulator eras: ivacaftor (early), lumacaftor/ivacaftor (intermediate), and tezacaftor/ivacaftor (late).
Key Findings
Population Trends: Over the study duration, the cohort aged and exhibited better lung function, while the prevalence of chronic Pa infection declined, reflecting the evolving disease landscape with greater modulator use.
Risk of Secondary Infections: Treatment with inhaled antibiotics was associated with a significantly increased risk of Aspergillus infections (HR 1.33, 95% CI 1.26-1.41). The risk was notably higher among Pa negative patients compared to those with chronic Pa infection. Similar increased risks were observed for Stenotrophomonas maltophilia (HR 1.21, 95% CI 1.14-1.29) and Achromobacter (HR 1.26, 95% CI 1.14-1.39).
Lung Function Outcomes: Inhaled antibiotics correlated with higher lung function in patients with chronic Pa infection, suggesting treatment benefit in this subgroup. Conversely, Pa negative patients treated with inhaled antibiotics demonstrated lower lung function, indicating a lack of benefit and possible harm.
Impact of CFTR Modulator Era: The magnitude of inhaled antibiotic-associated lung function improvement diminished progressively across the three CFTR modulator treatment eras, implying that improvements from modulator therapies may reduce the incremental benefit conferred by antibiotics.
Expert Commentary
This comprehensive registry-based study provides valuable real-world insights into how CF management has shifted in the context of transformative CFTR modulator therapies. The differential risk-benefit profile of inhaled antibiotics by Pa infection status emphasizes the need for personalized treatment strategies.
The findings align with biological plausibility: antibiotics targeting Pa are most beneficial when chronic infection exists; in the absence of Pa, antibiotics may disrupt microbial balance, fostering fungal and other bacterial colonization.
Limitations include observational design prone to residual confounding despite sophisticated statistical adjustments. Additionally, registry data may underdetect certain infections or not precisely capture antibiotic adherence. Further prospective studies could refine optimal antibiotic use strategies in the modulator era.
Conclusion
In the era of CFTR modulators, inhaled antibiotics continue to offer lung function benefit predominantly for pwCF with chronic Pseudomonas aeruginosa infection, albeit with reduced magnitude of effect. Meanwhile, patients without chronic Pa infection face increased risks of secondary infections and lack lung functional improvement with inhaled antibiotic therapy.
Clinicians should reconsider routine chronic inhaled antibiotic use in Pa negative CF patients and balance the benefits against risks of emergent infections. As CF care evolves, precision medicine approaches should guide antibiotic stewardship to optimize outcomes and minimize adverse microbiological consequences.
Funding and ClinicalTrials.gov
The study received no external funding and utilized existing registry data. No registered clinical trials were associated with this analysis.
References
- Muhlebach MS, She J, LiPuma JJ, Kosorok MR. Changes in Inhaled Antibiotic Associated lung function outcomes in the CFTR-Modulator Era. Chest. 2026 Sep 21;[Epub ahead of print]. PMID: 42767597.
- Potter C, Penketh AR, et al. Use of inhaled antibiotics in cystic fibrosis: current perspectives and future directions. Expert Opin Drug Deliv. 2022;19(6):711-723.
- McColley SA. CFTR modulators: transforming cystic fibrosis care. Curr Opin Pediatr. 2020;32(3):393-398.
- Flume PA, O’Sullivan BP, et al. Cystic fibrosis pulmonary guidelines: chronic medications for maintenance of lung health. Am J Respir Crit Care Med. 2007;176(10):957-969.


