Highlight
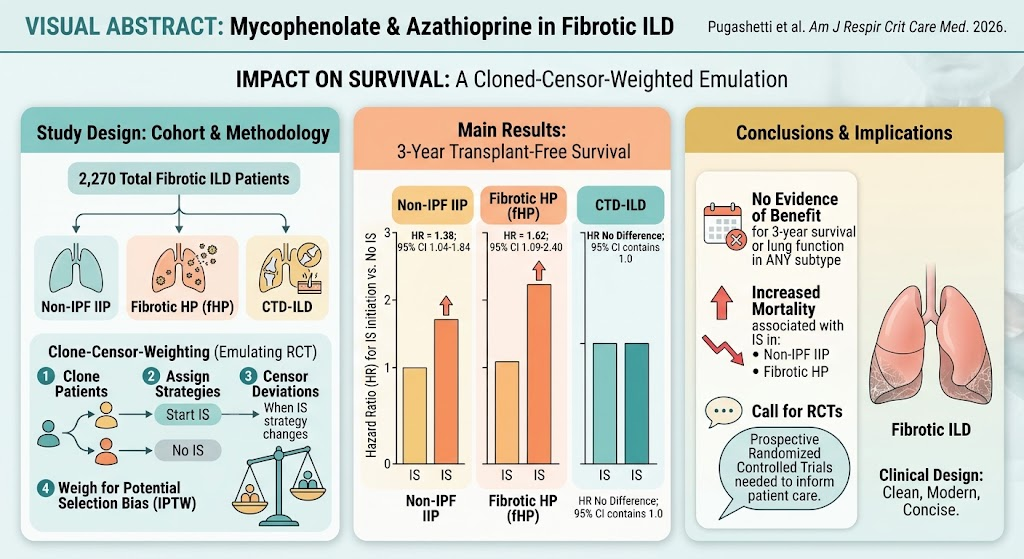
1. Immunosuppressive therapy with mycophenolate or azathioprine showed no benefit in 3-year transplant-free survival for fibrotic interstitial lung diseases (ILDs).
2. Worse survival was associated with immunosuppression in non-IPF idiopathic interstitial pneumonia (IIP) and fibrotic hypersensitivity pneumonitis (fHP).
3. Lung function trajectory did not improve with immunosuppression across ILD subtypes assessed.
4. Prospective randomized controlled trials are urgently needed to clarify the role and safety of immunosuppression in fibrotic ILD.
Study Background
Chronic fibrotic interstitial lung diseases represent a heterogeneous group of disorders characterized by progressive scarring of lung parenchyma, resulting in respiratory impairment and increased mortality. Idiopathic pulmonary fibrosis (IPF) is the archetype of fibrotic ILD with a well-established poor prognosis and limited treatment options. However, other fibrotic ILDs such as non-IPF idiopathic interstitial pneumonia (IIP), fibrotic hypersensitivity pneumonitis (fHP), and connective tissue disease-associated ILD (CTD-ILD) also impose substantial disease burden and mortality. Immunosuppression with agents like mycophenolate mofetil and azathioprine is commonly employed in non-IPF fibrotic ILD, based on pathophysiological rationale and clinical experience. Nevertheless, high-quality evidence from randomized controlled trials (RCTs) regarding long-term benefits or risks remains limited, and the impact on survival and lung function outcomes is unclear. This has led to clinical equipoise and variability in management approaches worldwide.
Study Design
The study by Pugashetti and colleagues employed an innovative clone-censor-weighting methodology to emulate an RCT using retrospective multicenter data from 2,270 patients with fibrotic ILDs. This statistical approach enabled comparison of treatment strategies by cloning each patient into two hypothetical arms: one assigned to initiate immunosuppression within six months of enrollment, the other assigned to no immunosuppression initiation. Patients were censored when their real treatment course diverged from the assigned strategy. Stabilized inverse probability weights accounted for confounding and censoring. The ILD subtypes evaluated included non-IPF IIP (n=1022), fHP (n=544), and CTD-ILD (n=704). The primary endpoint was 3-year transplant-free survival, analyzed via weighted Cox proportional hazards models across treatment groups. Secondary outcome assessed lung function trajectory using weighted generalized estimating equations, focusing on forced vital capacity (FVC) changes over time.
Key Findings
Only a minority of patients within each ILD subtype commenced immunosuppression within six months (non-IPF IIP 18%, fHP 30%, CTD-ILD 31%). The main results indicated no survival benefit associated with initiation of immunosuppressive therapy in any subgroup. In fact, initiation of mycophenolate or azathioprine correlated with significantly worse survival in non-IPF IIP (hazard ratio [HR] 1.38; 95% confidence interval [CI], 1.04–1.84) and fHP (HR 1.62; 95% CI, 1.09–2.40). CTD-ILD patients showed no significant survival difference. Regarding lung function trajectory, immunosuppression initiation did not significantly alter FVC decline when compared with no immunosuppression in any ILD subtype.
Safety data were not explicitly detailed in this retrospective analysis; however, the increased mortality risk observed among certain groups raises concerns about potential adverse effects or ineffectiveness of the immunosuppressive regimens in these populations.
Expert Commentary
This study provides a critical real-world perspective highlighting the lack of evidence for benefit and potential harm from mycophenolate or azathioprine in specific fibrotic ILD subtypes. Patients with non-IPF IIP and fHP appear particularly vulnerable to adverse outcomes when exposed to immunosuppression, potentially reflecting heterogeneous disease mechanisms or detrimental effects of suppressing inflammation in fibrotic contexts. In contrast, CTD-ILD, often driven by autoimmune pathology, may not experience survival detriment, though no clear benefit emerged. The clone-censor-weighting approach, while robust for observational data, cannot fully substitute for randomized trials which remain the gold standard for causal inference. The findings align with prior concerns voiced in clinical practice about the indiscriminate use of immunosuppression in fibrotic ILDs and underscore the urgent need for prospective trials to delineate which patients, if any, may benefit and which may be harmed.
Additionally, mechanisms underlying increased mortality with immunosuppression deserve further exploration including risks of infection, drug toxicity, and interaction with fibrotic pathways. Biomarker-driven phenotyping may guide future individualized treatment decisions.
Conclusion
This comprehensive retrospective study casts doubt on the benefit of initiating mycophenolate or azathioprine in fibrotic ILDs outside of IPF, showing no improvement in 3-year transplant-free survival or lung function, and potential harm in non-IPF IIP and fHP subgroups. Given the considerable morbidity and mortality associated with fibrotic ILDs, these data highlight the critical knowledge gaps and safety concerns surrounding immunosuppressive therapy in these diseases. Clinicians should exercise caution and consider risks when prescribing such agents pending definitive randomized trial evidence. Future research must prioritize prospective RCTs incorporating stratified patient populations, mechanistic insights, and long-term outcome assessment to guide optimal management strategies for fibrotic ILDs.
Funding and Clinical Trials
The reported study was a multicenter retrospective analysis without direct funding sources stated. The necessity of prospective randomized controlled trials is emphasized to establish evidence-based treatment protocols.
References
1. Pugashetti JV, Jee AS, Yu AR, et al. Mycophenolate and azathioprine in fibrotic interstitial lung disease. Am J Respir Crit Care Med. 2026 Oct 1;212(10):2493-2503. PMID: 42432856.
2. Raghu G, et al. Management of idiopathic pulmonary fibrosis: clinical practice guidelines update. Am J Respir Crit Care Med. 2018;198(7):e44-e68.
3. Cottin V, et al. Fibrotic hypersensitivity pneumonitis: clinical characteristics and outcome. Eur Respir J. 2014;43(4):969-978.
4. Fischer A, et al. Connective tissue disease-associated interstitial lung disease: a comprehensive review and ongoing challenges. Eur Respir Rev. 2016;25(140):47-58.
5. Oldham JM, et al. Immunosuppressive therapy in IPF and non-IPF fibrotic ILDs: a clinical conundrum. Thorax. 2021;76(1):3-12.