

Highlight
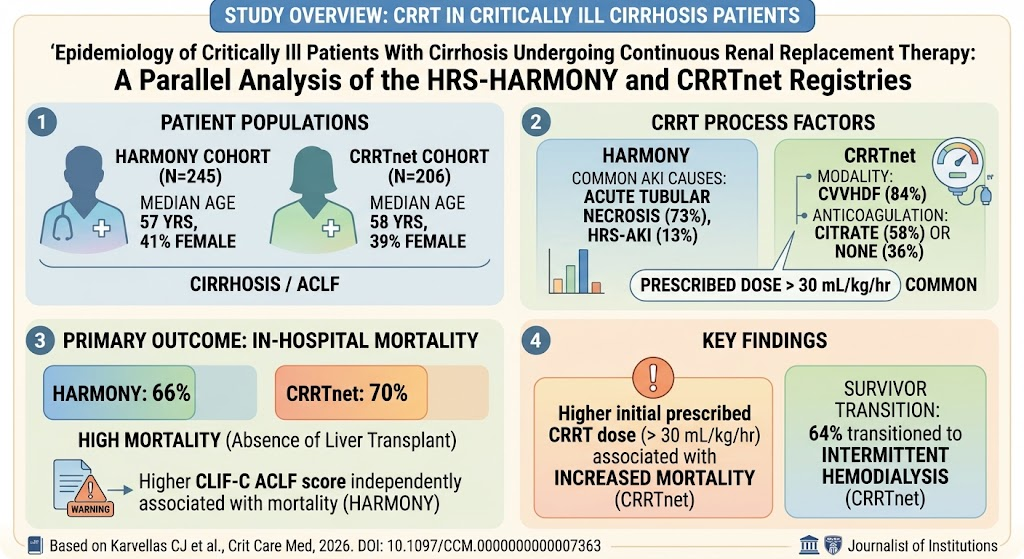
- Critically ill patients with cirrhosis and acute-on-chronic liver failure (ACLF) exhibit high in-hospital mortality when treated with continuous renal replacement therapy (CRRT).
- Higher prescribed CRRT dose (>30 mL/kg/hr) is independently associated with increased mortality, suggesting careful dosing optimization is necessary.
- Regional citrate anticoagulation is commonly utilized despite historical concerns about citrate toxicity in cirrhotic patients.
- Most ICU survivors transition from CRRT to intermittent hemodialysis prior to hospital discharge, indicating the trajectory of renal recovery and dialysis management in this population.
Specialty calculators
For clinical reference; use professional judgment.


