Highlight
Cavernous sinus thrombosis (CST) is a rare but potentially fatal condition that can present subtly without classic orbital signs, often leading to diagnostic delays and misdiagnosis.
Early clinical features such as headache, cranial neuropathies, and neck pain, especially in younger patients with sphenoid sinusitis, warrant high suspicion for CST.
Imaging commonly reveals sphenoid sinus opacification, bony erosion, and superior ophthalmic vein thrombosis, aiding definitive diagnosis.
Prompt sinus surgery combined with anticoagulation is critical for source control and improving clinical outcomes, although hemorrhagic complications can occur.
Study Background
Cavernous sinus thrombosis is a rare thrombotic complication of infections, notably paranasal sinusitis, with an estimated high mortality and morbidity despite modern therapies. The cavernous sinus’s intimate relation to cranial nerves and venous drainage pathways results in complex neurological manifestations. Early CST can lack hallmark features such as orbital edema or visual loss, complicating prompt recognition and delaying intervention. Misdiagnosis can lead to poor outcomes, underscoring the need to better delineate early clinical and radiologic patterns and to guide management. This study presents the largest single-institution series to characterize these facets, exploring patterns of initial diagnostic uncertainty (IDU) and its clinical correlates.
Study Design
This retrospective cohort study reviewed 33 patients diagnosed with CST based on radiologic criteria at a single institution. IDU was defined as any prior discharge or transfer with a diagnosis unrelated to CST, such as migraine, muscle strain, or uncomplicated sinusitis. Data captured included demographics, presenting symptoms, cranial neuropathies, imaging findings, timing from symptom onset to presentation, treatment modalities including sinus surgery and anticoagulation, complications, and outcomes including visual impairment and radiographic resolution of thrombosis. Statistical analyses identified factors associated with diagnostic delays.
Key Findings
Diagnostic Challenges and Presentation:
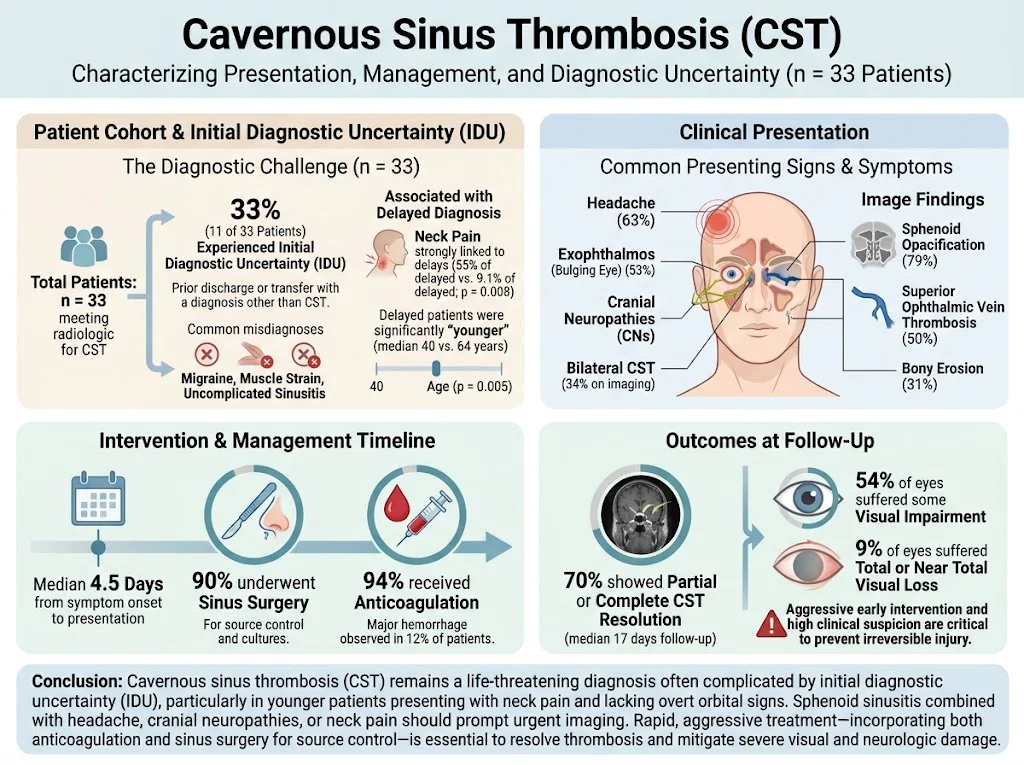
One-third (33%) of patients experienced IDU with initial misdiagnoses primarily made in the Emergency Department. These patients were significantly younger (mean age 40 vs. 64 years; p=0.005) and more frequently reported neck pain (55% vs. 9.1%; p=0.008). This finding suggests that younger adults presenting with headache and neck pain without classic orbital findings are particularly at risk for delayed CST diagnosis.
Clinical Signs:
Common presenting signs included headache (63%), exophthalmos (protrusion of the eye, 53%), and cranial neuropathies. Cranial nerve dysfunction involved nerves traversing the cavernous sinus, manifesting as ophthalmoplegia and sensory deficits.
Imaging Characteristics:
Computed tomography and magnetic resonance imaging revealed sphenoid sinus opacification in 79% of cases, which was frequently associated with bony erosion (31%). Superior ophthalmic vein thrombosis was noted in half of the patients, and surprisingly, bilateral CST occurred in 34%, highlighting the aggressive vascular involvement.
Management:
Almost all patients (90%) underwent sinus surgery, which allowed for direct infection source control and culture acquisition. Surgical timing was prompt following diagnosis. Anticoagulation was administered to 94% of patients to limit thrombus propagation, despite a 12% incidence of major hemorrhagic complications, which emphasizes the risk-benefit balance clinicians must navigate.
Outcomes:
Follow-up imaging at a median of 17 days showed 70% of patients achieved partial or complete resolution of CST. Visual impairment persisted in more than half of the affected eyes, with 9% suffering total or near-total visual loss, reflecting the serious potential for long-term disability.
Summary Table of Relevant Data:
| Parameter | Value or Percentage |
|---|---|
| Patients with IDU | 33% (11/33) |
| Mean age (IDU vs. non-IDU) | 40 vs. 64 years (p=0.005) |
| Neck pain association with delay | 55% vs. 9.1% (p=0.008) |
| Headache presentation | 63% |
| Exophthalmos presentation | 53% |
| Sphenoid sinus opacification on imaging | 79% |
| Bony erosion | 31% |
| Superior ophthalmic vein thrombosis | 50% |
| Bilateral CST | 34% |
| Sinus surgery performed | 90% |
| Anticoagulation administered | 94% |
| Major hemorrhagic events | 12% |
| CST resolution at follow-up | 70% |
| Visual impairment rate | 54% of eyes |
| Total/near total visual loss | 9% |
Expert Commentary
Cavernous sinus thrombosis remains a neurologic emergency requiring heightened clinical vigilance. The study by Anisman et al. fortifies the understanding that early CST can be diagnostically elusive, especially in younger patients without overt orbital findings. The association of neck pain with diagnostic delay underscores the need for comprehensive neurological and infectious evaluations in such presentations.
From a pathophysiological angle, CST results from propagation of infectious thrombophlebitis typically originating from sinus or facial infections, particularly involving the sphenoid sinus due to its proximity to the cavernous sinus. The noted bony erosion and venous involvement on imaging are pathognomonic and should prompt urgent surgical intervention. Sinus surgery provides crucial means of infection source control and enables targeted antimicrobial therapy based on culture data.
Anticoagulation remains controversial due to bleeding risks but is generally indicated to prevent thrombus extension and aid resolution, with close monitoring.
Limitations of this study include its retrospective nature and single-center design, which could influence generalizability. However, the comprehensive characterization of presentations and management strategies contributes valuable clinical insights, particularly in highlighting the risk factors for initial diagnostic uncertainty.
Conclusion
Clinicians should maintain a high index of suspicion for CST in patients presenting with sphenoid sinusitis accompanied by headache, cranial neuropathies, orbital signs, or neck pain. Early recognition through detailed examination and imaging is paramount. Prompt sinus surgery combined with anticoagulation therapy constitutes the cornerstone of effective treatment, though clinicians must balance hemorrhagic risks.
This study emphasizes the importance of awareness of subtle early clinical features and supports aggressive intervention to reduce permanent neurological impairment. Further prospective studies are needed to optimize diagnostic pathways and refine management protocols for this severe condition.
Funding and ClinicalTrials.gov
The original study does not report external funding or ClinicalTrials.gov registration. Further research support details were not specified.
References
- Anisman EJ, Colwell L, DeSimone J, et al. Cavernous Sinus Thrombosis: Presentation, Management, and Initial Diagnostic Uncertainty. Laryngoscope. 2026 Aug;136(11):4797-4805. PMID: 42550667.
- Bhatia K, Busaidi A, Elboushi A. Cavernous sinus thrombosis: a review of pathogenesis, clinical presentation, and management. Int J Emerg Med. 2015;8(1):21.
- Suppiah S, Meenakshi-Sundaram S, Kumar S. The contemporary approach to diagnosis and management of cavernous sinus thrombosis. Eur J Neurol. 2017;24(1):58-65.
- Morton RP, Howard MR. Surgical management of septic cavernous sinus thrombosis secondary to sphenoid sinusitis. J Laryngol Otol. 2020;134(7):597-602.
Specialty calculators
For clinical reference; use professional judgment.