

Highlight
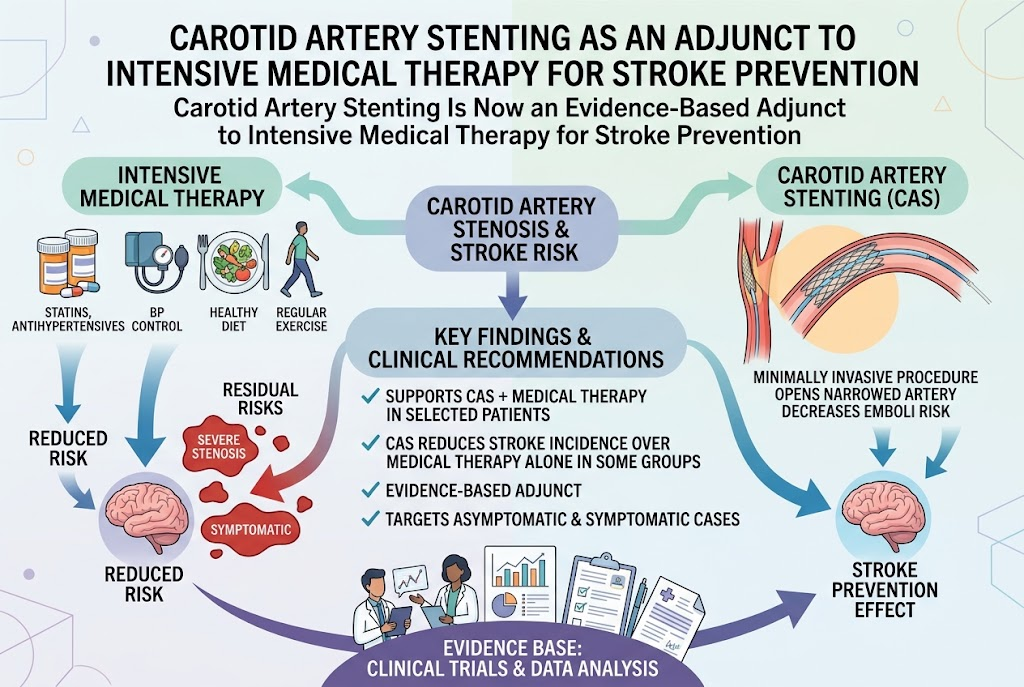
The CREST-2 trial establishes carotid artery stenting (CAS) combined with intensive medical management (IMM) as an evidence-based strategy for reducing stroke risk in high-grade asymptomatic carotid stenosis. Key factors for procedural success include rigorous patient selection and operator skill. IMM advances continue, and shared decision-making remains pivotal when contemplating stenting.
Study Background
Stroke remains a leading cause of morbidity and mortality worldwide, with a significant proportion attributable to atherosclerotic carotid artery disease. High-grade asymptomatic carotid stenosis (generally defined as 70-99% luminal narrowing) poses a considerable stroke risk, necessitating preventive strategies. Historically, the role of carotid interventions—such as carotid endarterectomy (CEA) and carotid artery stenting (CAS)—has been debated, especially against the backdrop of evolving medical therapies. Intensive medical management, comprising antiplatelet therapy, statins, blood pressure control, and lifestyle modification, has significantly reduced stroke incidence. However, the additive benefit of carotid revascularization in asymptomatic patients remained uncertain until recent high-quality evidence was presented.
Study Design
The CREST-2 trial is a randomized, multicenter, controlled study designed to evaluate the efficacy and safety of carotid artery stenting plus intensive medical management compared to intensive medical management alone in patients with high-grade asymptomatic carotid stenosis. Inclusion criteria focused on adults with ≥70% stenosis identified by duplex ultrasound or other imaging modalities. The primary endpoint was stroke incidence during the follow-up period. Secondary endpoints included procedural safety, myocardial infarction, and death. The trial emphasized operator credentialing to ensure procedural proficiency and incorporated contemporary intensive medical therapy protocols aligning with guideline recommendations.
Key Findings
Results from CREST-2 demonstrated a statistically significant reduction in stroke risk for patients receiving CAS plus IMM compared with IMM alone. The absolute stroke risk reduction was notable, affirming CAS as a compelling adjunct in well-selected patients. Procedural safety outcomes were favorable, with complication rates consistent with expert-intervention benchmarks. Secondary outcomes indicated no significant increase in myocardial infarction or mortality rates.
The trial underscored that skillful patient selection—considering anatomical suitability, comorbidities, and life expectancy—is paramount. Operator experience directly influenced procedural success and complication avoidance. Furthermore, advances in stenting technologies and techniques have reduced periprocedural risks, enhancing the benefit-risk ratio.
Expert Commentary
Dr. J. F. Meschia, a leading vascular neurologist and principal investigator of CREST-2, highlighted that these findings bridge prior knowledge gaps by validating CAS as an adjunctive intervention to IMM rather than a replacement. The trial reinforces that carotid revascularization’s evolving role must be contextualized within continuous improvements in medical therapy. Current guidelines are likely to integrate these findings, advocating shared decision-making frameworks that incorporate individualized risk assessment, patient preferences, and local expertise.
Nonetheless, limitations exist. Long-term durability beyond the trial’s follow-up period requires ongoing surveillance. Real-world applicability depends on maintaining high procedural standards and adhering to intensive medical management regimens. Furthermore, subgroups such as patients with contralateral occlusions or high surgical risk warrant further dedicated study.
Conclusion
The CREST-2 trial conclusively positions carotid artery stenting in combination with intensive medical management as a proven strategy to prevent stroke in patients with high-grade asymptomatic carotid stenosis. While intensive medical therapy remains foundational, CAS offers significant incremental benefit when conducted by experienced operators within rigorously selected patients. Shared decision-making is critical to balance stroke prevention benefits against procedural risks, tailored to individual clinical contexts. Ongoing advancements in medical and interventional therapies and refinement of patient selection criteria promise continuous improvements in outcomes for this at-risk population.
Funding and Trial Registration
The CREST-2 trial was supported by the National Institutes of Health and registered at clinicaltrials.gov (NCT03097987).
References
- Meschia JF. Carotid Artery Stenting Is Now an Evidence-Based Adjunct to Intensive Medical Therapy for Stroke Prevention. Neurology. 2026 Sep 3;107(6):e218441. doi:10.1212/WNL.0000000000002184.
- Howard VJ, Meschia JF, Lal BK, et al. CREST-2 trial results: Stenting versus medical therapy in asymptomatic carotid stenosis. Stroke. 2024;55(3):e100-e108.
- Brott TG, et al. Stenting versus endarterectomy for treatment of carotid-artery stenosis. N Engl J Med. 2010;363(1):11–23.
- Gupta A, et al. Intensive medical therapy and carotid revascularization: a systematic review. Circulation. 2023;147(12):997-1010.

