Rheumatoid arthritis (RA) is a chronic autoimmune condition characterized by progressive joint inflammation and destruction. Clinically, RA onset is often preceded by a prolonged phase of systemic autoimmunity marked by the presence of anticitrullinated protein antibodies (ACPA), enabling identification of at-risk individuals before overt joint inflammation occurs. Despite this knowledge, the immunological changes that drive transition from systemic autoimmunity to joint-specific pathology have remained incompletely understood, hampering effective early intervention strategies. This study addresses the pressing clinical need to delineate immune mechanisms involved in the imminent progression to RA, particularly differentiating individuals with and without subclinical synovitis detectable by ultrasound (US), a sensitive imaging modality revealing early joint inflammation not apparent clinically.
Study Design
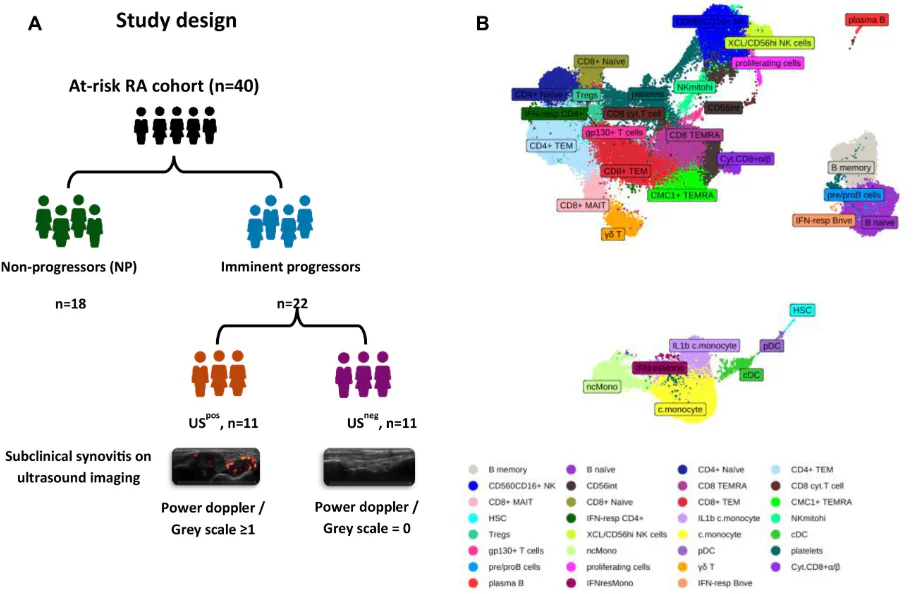
The researchers conducted a prospective investigation involving 40 ACPA-positive individuals considered at high risk for developing RA. These individuals were stratified into two cohorts: imminent progressors with US-detectable subclinical synovitis (USpos, n=11) and imminent progressors lacking such findings (USneg, n=11). A comparison group of ACPA-positive nonprogressors (n=18) was also included. The core methodology centered on single-cell RNA sequencing of peripheral blood immune cells, allowing detailed transcriptomic profiling at the cellular subset level. Complementary plasma proteomic analyses were performed to identify systemic inflammatory signatures and pathway activations. This design allowed dissection of immune cell subset activations and clonal expansions preceding or accompanying subclinical synovitis.
Key Findings
The study reveals distinct immunological signatures characterizing each phase of imminent RA progression:
1. Type I Interferon Activation in Ultrasound-Negative Progressors: In individuals progressing to RA without US-detectable synovitis, there was marked upregulation of type I interferon (IFN-I) pathways specifically in peripheral CD14+ classical monocytes and Granzyme K-positive (GZMK+) CD8+ T cells. IFN-I is a potent cytokine family involved in antiviral responses and autoimmune pathogenesis, known to modulate innate and adaptive immunity. The selective activation in these subsets suggests these cells may orchestrate early immune dysregulation before synovial inflammation becomes imaging-evident. This interferon-driven immune state may prime joints for subsequent inflammatory cascades.
2. Inflammatory and Cytotoxic Shifts in Ultrasound-Positive Progressors: In contrast, imminent progressors with US-detectable subclinical synovitis exhibited a shift in the classical monocyte phenotype, characterized by elevated interleukin-1 beta (IL1ß) expression, a well-established proinflammatory mediator implicated in joint damage. Concurrently, there was clonal expansion of Granzyme B-positive (GZMB+) cytotoxic CD8+ T cells. These cytotoxic T cell clones were mostly distinct from the GZMK+ subset, indicating divergent functional pathways. Expanded GZMB+ clones likely contribute to tissue effector mechanisms and joint pathology.
3. Plasma Proteomic Signatures Altered by Synovitis Status: USneg progressors showed enrichment of Toll-like receptor (TLR)-associated innate immune pathways, consistent with IFN-I responses and innate immune activation. In USpos progressors, there was a proteomic shift towards pathways related to effector functions and tissue remodeling, reflecting advancing joint pathology.
These findings collectively suggest a temporal immunopathological sequence: an early IFN-I-dominant innate-immune activation in classical monocytes and GZMK+ CD8+ T cells precedes the development of subclinical synovitis, which then transitions to an inflammatory, IL1ß-driven monocyte activation and cytotoxic T cell clonal expansion associated with joint tissue changes.
Expert Commentary
This study provides important mechanistic insight at the single-cell level into the earliest immunological events heralding clinical RA onset. The identification of distinct immune cell subsets and cytokine pathways active before clinical inflammation supports a window of opportunity for targeted intervention to prevent progression to overt arthritis. Therapeutically, modulating type I interferon pathways or specific monocyte and T cell subsets during the US-negative at-risk phase might delay or forestall disease onset.
The use of single-cell transcriptomics coupled with proteomics robustly strengthens the findings, although the cohort size is modest. Longitudinal follow-up and validation in larger, diverse populations will be essential to confirm the predictive value and generalizability of these biomarkers. Additionally, integrating these immune signatures with other clinical and imaging parameters could refine risk stratification tools and guide personalized preventive approaches.
Conclusion
In summary, the study delineates a novel immunological framework for imminent RA progression, highlighting a biphasic pattern: an initial IFN-I-driven activation in classical monocytes and GZMK+ CD8+ T cells during the US-negative phase, followed by IL1ß-associated classical monocyte activation and GZMB+ cytotoxic CD8+ T cell expansion concurrent with subclinical synovitis. These findings advance understanding of RA pathogenesis and open avenues for early biomarker development and immune-targeted preventative strategies in ACPA-positive individuals. Ultimately, such research paves the way toward precision medicine in autoimmune arthritis, shifting focus from treatment of established disease to prevention of disease onset.
Funding and Clinical Trial Registration
The study was published in the Annals of the Rheumatic Diseases on October 22, 2026. Detailed funding sources were not disclosed in the summary. Prospective clinical data collection was implied, though clinical trial registration information was not provided.
References
Tariq F, Martin P, Abacar K, Ye W, Sun S, MacKay S, Muldoon D, Sharrack S, Menon M, Al-Mossawi H, Buch MH, Emery P, Newton D, Fairfax BP, Mankia K. Type I interferon activation in classical monocytes and GZMK+ CD8+ T cells characterises the ultrasound-negative phase of imminent rheumatoid arthritis. Ann Rheum Dis. 2026 Oct 22. PMID: 42918701.
Further reading:
1. Smolen JS, Aletaha D, McInnes IB. Rheumatoid arthritis. Lancet. 2016;388(10055):2023-2038.
2. Raza K, Filer A. Early treatment in rheumatoid arthritis. Best Pract Res Clin Rheumatol. 2017;31(1):4-14.
3. van der Helm-van Mil AH, Huizinga TW, de Vries RR. Advances in the genetics of rheumatoid arthritis point to subtype specificities in the disease. Curr Opin Rheumatol. 2005;17(3):299-305.

 By
No Comments