

Highlight
This article evaluates novel interim outcome measures for multi-arm multistage (MAMS) trials in progressive multiple sclerosis (PMS), focusing on patient-reported mobility and physical health scales that robustly predict long-term disability progression and optimize trial efficiency.
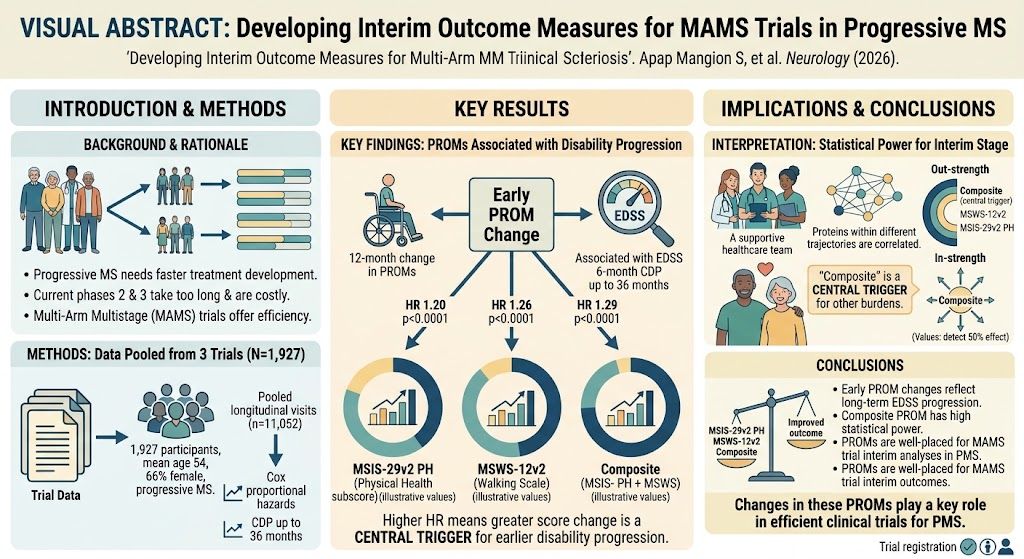
Using pooled data from 3 large PMS trials, the MSIS-29v2 Physical Health subscore, MSWS-12v2, and a composite score demonstrated significant association with six-month confirmed disability progression (CDP) on the EDSS over 36 months.
Simulations suggest that applying these patient-reported outcome measures (PROMs) as 12-month interim endpoints in MAMS trials can detect meaningful treatment effects with high statistical power, potentially reducing participant numbers and accelerating drug development.
Study Background
Progressive multiple sclerosis (PMS) is characterized by gradual neurological decline, leading to accumulating disability with limited therapeutic options despite extensive research. Traditional drug development relies heavily on phased clinical trials (phases 2 and 3) that are costly, lengthy, and require large patient cohorts to demonstrate efficacy, slowing the availability of new treatments.
Multi-arm multistage (MAMS) trial designs offer a solution by simultaneously evaluating multiple candidate therapies within a single protocol, using interim analyses to discontinue ineffective arms and advance promising treatments efficiently. However, effective interim outcome measures are critical to this process, requiring early sensitivity to clinical changes and strong correlation with final disability outcomes.
Patient-reported outcome measures (PROMs) provide a cost-effective, accessible approach to capturing patients’ perspectives on their functional status. Yet, their validity and power as interim endpoints in MAMS trials for PMS have not been fully established.
Study Design
The study conducted a pooled analysis of longitudinal data from three previously conducted PMS clinical trials, encompassing 11,052 visits from 2,046 participants. After exclusions, 1,927 participants (mean age 54 years, 66% female) were analyzed.
The candidate PROMs examined included the Multiple Sclerosis Impact Scale 29 version 2 Physical Health subscore (MSIS-29v2 PH), the Multiple Sclerosis Walking Scale 12 version 2 (MSWS-12v2), and a composite measure developed to minimize ceiling effects and prioritize scales showing greatest change.
Relationships between changes in these PROMs at early timepoints (notably at 12 months) and subsequent six-month confirmed disability progression (CDP) on the Expanded Disability Status Scale (EDSS) up to 36 months were explored using Cox proportional hazards models. Statistical simulations estimated sample size requirements for detecting treatment effects at interim analyses.
Key Findings
The study found statistically significant associations between 12-month increases in PROM scores and risk of EDSS 6-month CDP over 36 months. Hazard ratios for each 1-standard deviation increase were 1.20 (95% CI 1.08–1.33) for MSIS-29v2 PH, 1.26 (1.13–1.40) for MSWS-12v2, and 1.29 (1.16–1.44) for the composite score, all with p-values < 0.0001.
These findings indicate that worsening patient-reported physical function and walking ability at 12 months predicts long-term confirmed disability progression robustly.
Importantly, simulations demonstrated that using the composite PROM as an interim endpoint, a sample size of approximately 125 participants per treatment arm could detect a 50% treatment effect on mean 12-month change with statistical power equal to or exceeding 90%. Increasing to 200 participants per arm improved power to 95%, signifying that MAMS trials using these PROMs can be highly efficient in detecting treatment differences early.
Expert Commentary
This study underscores the growing recognition that PROMs can serve as meaningful, sensitive endpoints in progressive multiple sclerosis trials, reflecting patients’ lived experience and disease impact. Their incorporation enables more dynamic and resource-efficient trial designs like MAMS, which are crucial given the urgent need for effective PMS therapies.
The composite PROM developed mitigates ceiling effects that limit responsiveness in individual scales, improving detection of change across a wider disability spectrum. Such methodical optimization enhances the robustness of interim analyses and may translate into better go/no-go decision-making in multisite trials.
Limitations include reliance on data collected in previous trials with their own enrollment criteria and treatment backgrounds, which may affect generalizability. Additionally, while PROMs capture patient perspective, objective measures and biomarkers remain important for comprehensive assessment.
Future research should confirm these findings prospectively in ongoing MAMS trials and explore integration with imaging and fluid biomarkers to further refine early outcome measures.
Conclusion
In progressive multiple sclerosis clinical trials, patient-reported outcome measures such as the MSIS-29v2 Physical Health subscore, MSWS-12v2, and a composite of these scales have demonstrated predictive validity for confirmed disability progression over three years. Their use as 12-month interim outcomes in MAMS trial designs offers efficient detection of treatment efficacy, potentially accelerating trial timelines and reducing participant burden.
These findings support the adoption and further validation of PROMs as key tools in innovative trial methodologies for neurodegenerative diseases like PMS, addressing critical gaps in clinical trial efficiency and outcome measurement.
Funding and Clinical Trials Registrations
The analyzed data were pooled from three prior PMS clinical trials; specific funding details were not provided in the source article. Details for these trials can be found via ClinicalTrials.gov identifiers associated with the original studies.
References
- Apap Mangion S, Wade C, Coles D, et al. Developing Interim Outcome Measures for Multi-Arm Multistage Clinical Trials in Multiple Sclerosis. Neurology. 2026 Sep 24;107(8):e218426. doi:10.1212/WNL.0000000000200328.
- Chataway J, et al. Effect of high-dose biotin on disability in progressive multiple sclerosis (SPI2): A randomised, double-blind, placebo-controlled, phase 3 trial. Lancet Neurol. 2020;19(4):278-287.
- Lublin FD, Reingold SC. Defining the clinical course of multiple sclerosis: Results of an international survey. Neurology. 1996;46(4):907-911.
- Goodin DS, et al. Disease-modifying therapies in multiple sclerosis: Report of the Therapeutics and Technology Assessment Subcommittee of the American Academy of Neurology and the MS Council for Clinical Practice Guidelines. Neurology. 2002;58(2):169-178.


