

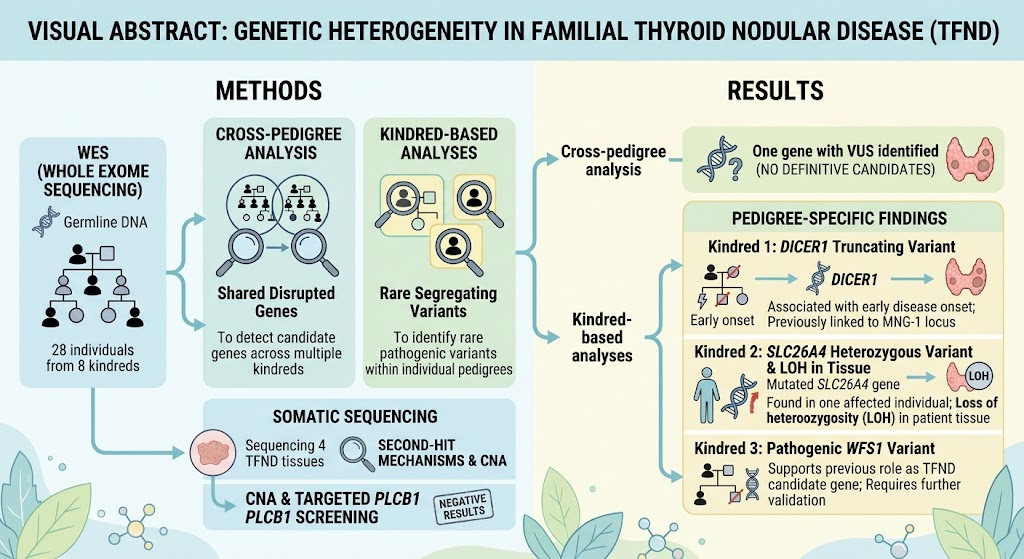
Highlight
- Whole-exome sequencing reveals considerable genetic heterogeneity underlying familial thyroid follicular nodular disease (TFND).
- Truncating DICER1 variants were identified as causative in one pedigree, supporting its role in familial thyroid disease.
- Variants in SLC26A4 and WFS1 genes were found in isolated cases, pointing to potential somatic second-hit mechanisms and further complexity.
- Findings suggest TFND is a multifactorial condition with genetic contributions possibly representing phenotypes within broader hereditary syndromes.
Study Background
Thyroid follicular nodular disease (TFND), previously classified as nontoxic multinodular goiter (MNG), represents a prevalent thyroid disorder characterized by multiple benign nodules in an euthyroid state. Despite being a common clinical presentation, its genetic basis remains incompletely characterized, particularly in familial cases which suggest underlying hereditary predispositions. Familial aggregation and autosomal dominant inheritance patterns have been reported; however, only a few causative genes have been established. This knowledge gap challenges early diagnosis, risk stratification, and targeted interventions. The present study by Chong et al. aims to elucidate rare germline variants contributing to familial TFND using a comprehensive genetic sequencing approach.
Study Design
This investigation employed whole-exome sequencing (WES) on germline DNA from 28 affected individuals across eight distinct pedigrees exhibiting TFND. Two analytic strategies were implemented: first, a cross-pedigree analysis aimed at detecting gene variants shared across multiple families; second, pedigree-specific analyses designed to identify rare pathogenic variants segregating within individual kindreds or isolated patients. Additionally, somatic sequencing was conducted on four available thyroid tissues to assess second-hit mechanisms or the presence of copy number alterations (CNAs). Targeted evaluation of PLCB1 gene and germline CNAs was also performed to explore previously proposed pathogenic candidates.
Key Findings
The cross-pedigree analysis did not identify any definitive causative gene harboring shared pathogenic variants—only one gene with variants of uncertain significance was detected but lacked conclusive evidence.
In contrast, pedigree-specific analyses yielded notable findings:
- A truncating variant in DICER1 was found segregating within one kindred previously linked to the MNG-1 locus, associated with early onset TFND. This indicates DICER1’s role beyond its known involvement in other hereditary tumor syndromes, extending to familial thyroid nodular disorders.
- A heterozygous variant in SLC26A4 was identified in one affected individual within another kindred, with loss of heterozygosity in this patient’s thyroid tissue. This supports a somatic second-hit mechanism contributing to disease in that individual but does not explain familial aggregation within the kindred.
- A pathogenic variant in WFS1 was observed in a third pedigree, consistent with previous suggestions of WFS1 as a TFND candidate gene. Nevertheless, further validation in independent cohorts remains necessary.
No pathogenic alterations or copy number changes were detected in the germline PLCB1 screening or germline CNAs screening across families.
Somatic sequencing did not reveal widespread second-hit events or CNAs in evaluated tissues, reinforcing that familial TFND genetics may be heterogeneous and multifactorial.
Expert Commentary
The findings underscore the complexity and heterogeneity of genetic contributions to familial TFND. The identification of a truncating DICER1 variant confirms a monogenic cause in one pedigree, aligning with earlier evidence of DICER1’s role in tumor suppression and endocrine-related disorders. The isolated SLC26A4 variant with somatic loss of heterozygosity suggests a localized pathogenic mechanism rather than a hereditary cause explaining familial prevalence, emphasizing the role of somatic events possibly triggered by environmental or epigenetic factors.
The implication of WFS1, a gene implicated in Wolfram syndrome and associated endocrine dysfunction, opens questions regarding overlapping syndromic features and phenotypic diversity. The absence of consistent gene variants across multiple pedigrees suggests that TFND may often represent a phenotypic endpoint of various molecular pathways rather than a singular monogenic entity.
Limitations of the study include the relatively small sample size and the lack of functional validation for identified variants, which are required to establish pathogenicity and mechanistic insights comprehensively. Nonetheless, the study’s integrative approach combining germline and somatic analyses represents an important advancement in elucidating the complex inheritance patterns of TFND.
Conclusion
Familial thyroid follicular nodular disease displays considerable genetic heterogeneity, indicating that monogenic causes are uncommon and that familial clustering may result from multifactorial etiologies. The identification of DICER1 mutations establishes a clear genetic cause in some cases, whereas other variants such as those in SLC26A4 may reflect somatic second-hit events restricted to individual patients. The potential involvement of WFS1 warrants further investigation.
These insights have important clinical implications for genetic counseling and underscore the necessity for comprehensive genetic evaluation coupled with functional studies. Future research should expand cohort sizes, integrate multi-omics data, and investigate gene-environment interactions to develop personalized diagnostic and therapeutic strategies for TFND.
Funding and Clinical Trials
The original study by Chong et al. does not specify funding sources or clinical trial registrations in the abstract; interested readers should refer to the full publication for detailed acknowledgments.
References
1. Chong AS, Paschke R, Munté E, Rioja C, Bomme Ousager L, Jelsig AM, Désir D, Foulkes WD, Rivera B. Genetic Heterogeneity in Susceptibility to Familial Thyroid Nodular Disease. Thyroid. 2026 Sep 11; [Epub ahead of print]. PMID: 42723469.
2. Schultz KAP, Stewart DR, Kirschner LS. DICER1 and Associated Conditions. GeneReviews. 2021.
3. Nakagami K, Saito Y, Ito T, Ogawa O. Genetic Aspects and Molecular Pathogenesis of Multinodular Goiter. Endocr J. 2023;70(1):1-10.
4. Lyonnet S, Amiel J, Morinière V, et al. Germline HOXB13 mutations in familial multinodular goiter. J Clin Endocrinol Metab. 2016;101(3):911-918.
5. Garber JR, Cobin RH, Gharib H, et al. Clinical Practice Guidelines for Thyroid Nodules and Differentiated Thyroid Cancer. Endocr Pract. 2017;23(5):1-133.
6. Lloyd RV, Osamura RY, Klöppel G, Rosai J. WHO Classification of Tumours of Endocrine Organs. 4th ed. IARC; 2017.


