

Highlight
- Heterozygous germline mutations in MSH3 and probably MLH3 increase colorectal cancer (CRC) risk by approximately two-fold via somatic second hits.
- Bi-allelic MSH3 and MLH3 mutation carriers exhibit tumor phenotypes resembling constitutional mismatch repair deficiency (cMMRd), including hypermutation without microsatellite instability.
- Excess somatic deletions, particularly ≥2 base pairs, and mutational signature ID4 are characteristic of MSH3/MLH3-deficient colorectal tumors.
- ID4 mutational signature, linked to these deficiencies, has not previously been causally associated with specific mutations in human tumors.
Study Background
DNA mismatch repair (MMR) is a key pathway ensuring genomic integrity by correcting insertion-deletion loops and base mismatches arising during DNA replication. While canonical MMR genes such as MLH1, MSH2, MSH6, and PMS2 are well-established drivers of Lynch syndrome and colorectal cancer predisposition, non-canonical MMR genes including MSH3 and MLH3 have been less extensively characterized. Recent reports describe colorectal adenomas and cancers in rare patients with bi-allelic germline MSH3 or MLH3 mutations, implicating these genes in hereditary CRC risk. However, the spectrum of cancer risk in heterozygous carriers and the underlying molecular mechanisms remain incompletely understood.
Given the critical role of MSH3 and MLH3 in repairing insertion-deletion mutations, understanding whether heterozygous loss-of-function mutations in these genes act similarly to Lynch syndrome-related MMR defects could expand the paradigm of inherited colorectal cancer risk and inform genetic counseling and screening strategies.
Study Design
This large-scale genetic association study incorporated approximately 12,000 colorectal cancer and multiple polyp cases and 460,000 population controls. Among these, 2,023 patients underwent comprehensive cancer genome sequencing to evaluate somatic mutation patterns and tumor molecular profiles.
The investigators screened for germline mutations in MSH3 and MLH3, assessing both bi-allelic and heterozygous carriers. They further analyzed tumors from these patients for somatic inactivating “second hits” to ascertain mechanisms of tumor suppressor gene inactivation. They characterized tumor mutational burden, microsatellite instability status, and mutational signatures, focusing particularly on signature ID4 and the prevalence of somatic deletion mutations.
Key Findings
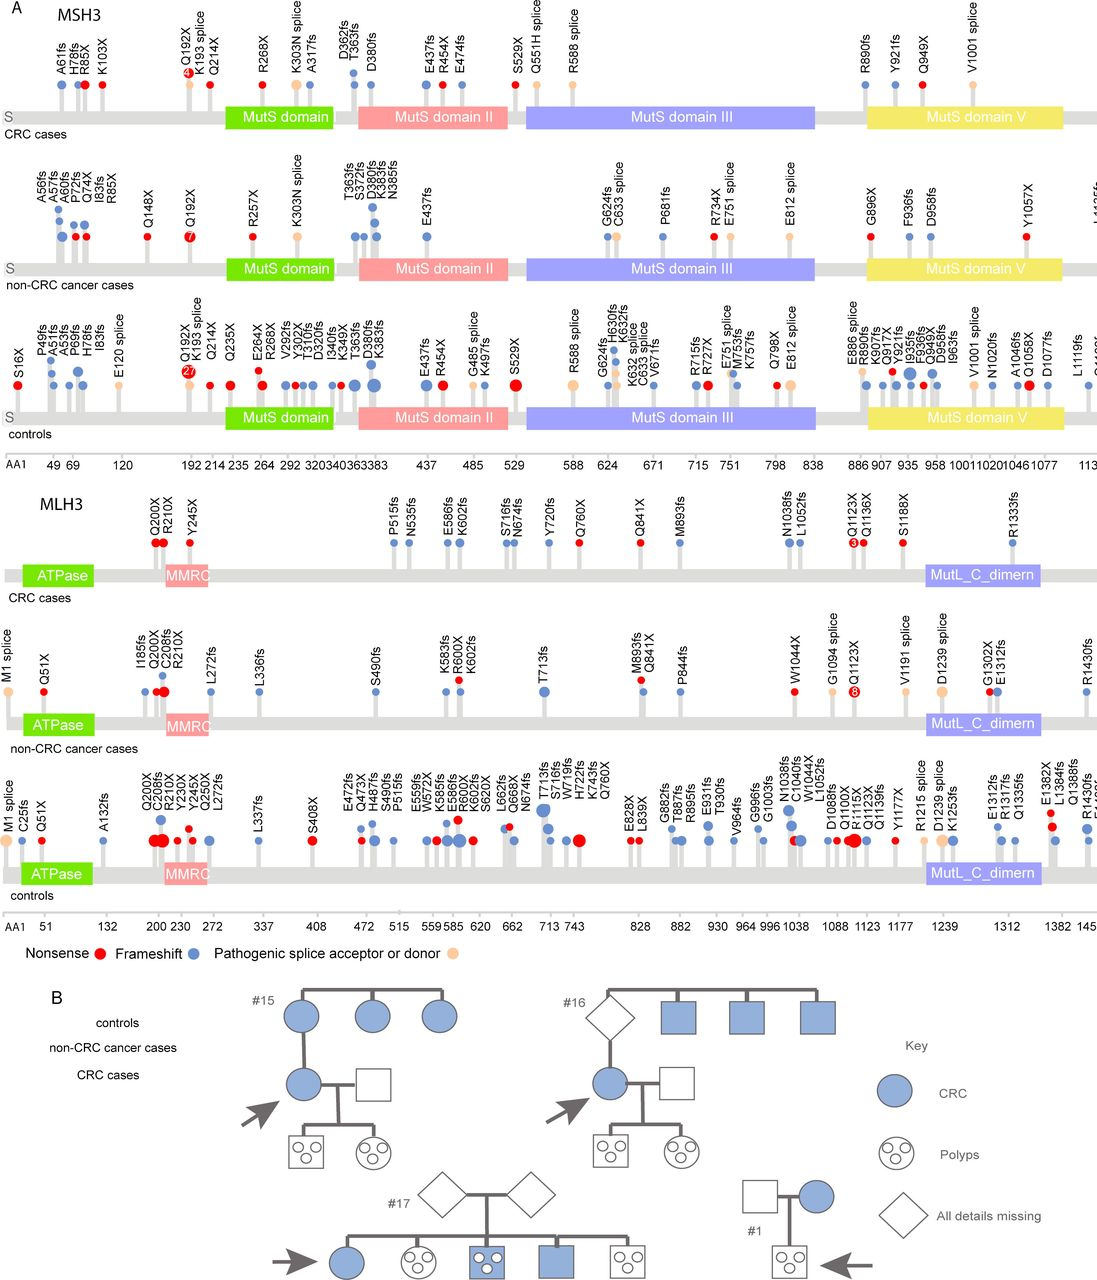
Among studied patients, one case exhibited bi-allelic germline mutations in MSH3, and another harbored bi-allelic mutations in MLH3, both consistent with a constitutional mismatch repair deficiency phenotype. Significantly, carriers heterozygous for germline loss-of-function mutations in MSH3 and MLH3 demonstrated a statistically significant increased colorectal cancer risk—2.2-fold for MSH3 (p=6.6×10⁻⁵) and 1.6-fold for MLH3 (p=0.028)—compared to controls.
Tumors from heterozygous carriers frequently acquired somatic second hits that inactivated the remaining wildtype allele, aligning with the classical two-hit hypothesis for tumor suppressor genes. Intriguingly, single somatic events occasionally simultaneously inactivated both MSH3 and the nearby APC gene, an important driver in colorectal tumorigenesis, suggesting a cooperative mechanism in tumor development.
All colorectal cancers deficient in MSH3 or MLH3 were microsatellite-stable (MSS) despite exhibiting hypermutation—a phenotype divergent from canonical Lynch syndrome tumors characterized by microsatellite instability. The tumors showed a particularly elevated burden (~12-fold increase) of somatic deletions of two or more base pairs, which correlates strongly with mutational signature ID4. This signature, previously not linked to a defined etiology in human cancers, was highly enriched (p<0.0001) in MSH3- and MLH3-deficient tumors.
Tumors from heterozygotes lacking second hits did not demonstrate hypermutation, indicating that loss of both alleles is required to produce the hypermutant phenotype and increased colorectal cancer risk.
Expert Commentary
This study provides pivotal evidence that heterozygous germline mutations in non-canonical MMR genes MSH3 and likely MLH3 act as classical tumor suppressors, increasing CRC risk through mechanisms similar to those in Lynch syndrome but with distinct molecular characteristics. Notably, the observed phenotype resembles PMS2-mutant Lynch syndrome with microsatellite stability but hypermutation driven by indel mutagenesis.
The identification of mutational signature ID4 as a hallmark of MSH3 or MLH3 deficiency deepens mechanistic understanding of DNA repair deficiency phenotypes and may serve as a biomarker to identify these mutation carriers. The co-inactivation of APC alongside MSH3 hints at a potentially synergistic genomic instability pathway driving colorectal tumor initiation.
Limitations include the rarity of bi-allelic MLH3 mutation carriers and the need for functional assays to definitively confirm causality of specific MLH3 variants. Larger cohort studies and prospective clinical investigations are warranted to clarify penetrance, cancer risk stratification, and implications for genetic counseling and targeted surveillance in identified heterozygotes.
Conclusion
The study establishes that germline heterozygous loss-of-function mutations in MSH3 and likely MLH3 increase colorectal cancer susceptibility by operating as classical tumor suppressors requiring somatic inactivation of the wildtype allele. These defects promote hypermutant, microsatellite-stable tumors bearing excessive somatic deletions and characterized by the mutational signature ID4.
These findings expand the spectrum of hereditary colorectal cancer predisposition beyond canonical mismatch repair genes, underscore the importance of somatic second hits in tumorigenesis, and provide new genomic markers for identifying at-risk individuals. Integration of MSH3 and MLH3 germline testing into genetic screening programs may improve early detection and personalized management of colorectal cancer in mutation carriers.
Funding and Trials
Details on funding sources and clinical trial registrations were not reported in the current publication.
References
1. Soriano I, Sherwood K, Ward JC, et al. Heterozygous germline mutations in MSH3, and probably MLH3, act as classical tumour suppressors, leading to excess somatic deletion mutations, signature ID4 and increased colorectal cancer risk. Gut. 2026; published ahead of print. PMID: 42728028.
2. Lynch HT, de la Chapelle A. Hereditary colorectal cancer. N Engl J Med. 2003;348(10):919-32.
3. Palles C, Cingi A, Howarth KM, et al. Germline variants in MLH3: implications for colorectal cancer susceptibility. J Med Genet. 2020;57(8):518-526.
4. Alexandrov LB, Kim J, Haradhvala NJ, et al. The repertoire of mutational signatures in human cancer. Nature. 2020;578(7793):94-101.


