

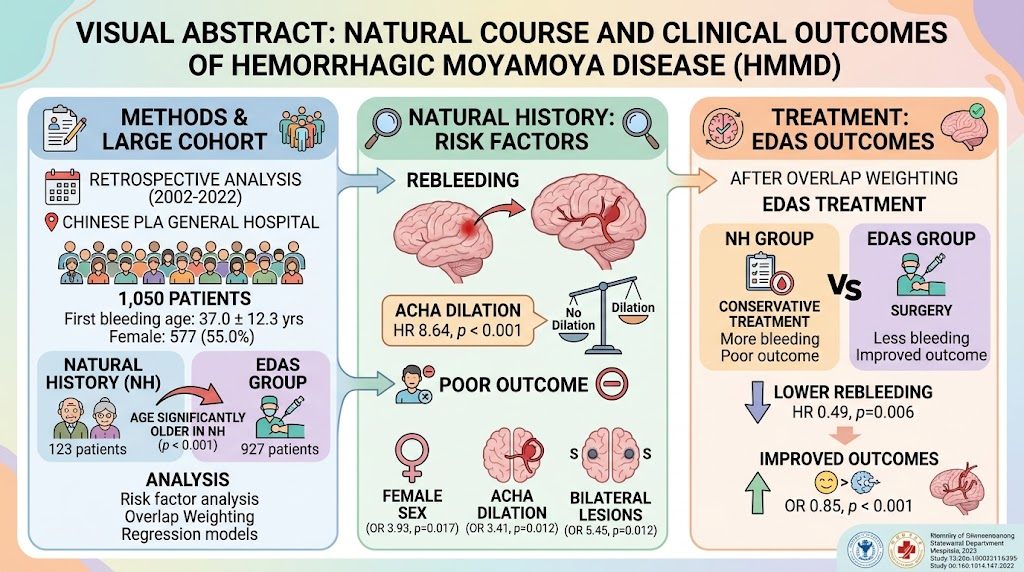
Highlight
- In hemorrhagic Moyamoya disease (hMMD), anterior choroidal artery (AChA) dilation strongly predicts rebleeding risk during the natural history.
- Female sex, AChA dilation, and bilateral cerebral lesions are key risk factors for poor neurological outcomes in hMMD patients.
- Indirect revascularization by encephaloduroarteriosynangiosis (EDAS) significantly reduces the incidence of rebleeding and improves clinical outcomes compared to conservative management.
- Findings reinforce the potential benefit of EDAS for hMMD but underscore the need for prospective validation.
Study Background
Moyamoya disease is a chronic, progressive cerebrovascular disorder characterized by stenosis or occlusion of the terminal portions of the internal carotid arteries and their major branches, leading to the development of a fragile compensatory collateral network. Hemorrhagic Moyamoya disease (hMMD), marked by intracranial bleeding due to rupture of these fragile vessels, represents one of the most severe clinical manifestations, often causing significant morbidity and mortality. Despite growing recognition, the natural history of hMMD—particularly the risk factors for rebleeding and poor outcomes—remains inadequately defined. Moreover, although surgical revascularization techniques such as encephaloduroarteriosynangiosis (EDAS) are employed to reduce ischemic symptoms and bleeding risk, high-quality long-term data on their efficacy in hMMD are limited. This knowledge gap impedes optimal clinical decision-making and prognostic counseling.
Study Design
This large, retrospective cohort study analyzed consecutive patients with hemorrhagic Moyamoya disease admitted to the Chinese PLA General Hospital over a 20-year period (April 2002 to March 2022). The cohort comprised 1,050 patients who experienced their first hemorrhagic event at a mean age of 37.0 ± 12.3 years, with female patients representing 55.0% of the population. Patients were categorized into two groups: 123 managed with conservative (natural history) treatment and 927 undergoing indirect revascularization by EDAS. Clinical data, radiological findings (including the status of anterior choroidal artery dilation and lesion laterality), rebleeding events, and neurological outcomes were systematically collected and analyzed. Statistical models, including logistic regression and Cox proportional hazards regression, identified predictors of poor outcomes and rebleeding. Overlap weighting was employed to balance baseline differences between the EDAS and conservative groups, followed by weighted regression models to compare clinical outcomes.
Key Findings
Demographics and Baseline Characteristics
Patients in the natural history group were significantly older at first hemorrhage (mean 43.7 years) compared to the EDAS group (mean 36.1 years). The female sex distribution was similar between groups.
Risk Factors During Natural History
By evaluating patients who did not undergo surgical intervention, anterior choroidal artery (AChA) dilation emerged as a potent risk factor for rebleeding with a hazard ratio (HR) of 8.64 (95% CI 3.03-24.67, p < 0.001). This finding suggests vessels’ pathological enlargement reflects hemodynamic stress and fragility, predisposing to hemorrhage recurrence.
Risk factors for poor neurological outcome in natural history patients included female sex (OR 3.93; 95% CI 1.27-12.13; p = 0.017), AChA dilation (OR 3.41; 95% CI 1.32-8.82; p = 0.012), and bilateral intracranial involvement (OR 5.45; 95% CI 1.45-20.52; p = 0.012). These associations emphasize that both patient demographics and vascular pathology influence clinical prognosis.
Efficacy of Indirect Revascularization with EDAS
After applying overlap weighting to balance confounders between surgical and conservative groups, EDAS treatment significantly reduced rebleeding rates (HR 0.49; 95% CI 0.30-0.81; p = 0.006). The odds of poor neurological outcomes were also lowered in the EDAS group (OR 0.85; 95% CI 0.79-0.93; p < 0.001). These findings support the clinical utility of EDAS in mitigating hemorrhagic risks and improving functional recovery in hMMD.
Safety and Limitations
The retrospective design limits causal inference and could harbor selection bias, despite statistical adjustments. The study did not report on perioperative complications or long-term morbidity specifics beyond functional outcomes. Additionally, the cohort being single-center and ethnically Chinese may affect generalizability.
Expert Commentary
This landmark study provides compelling evidence that anatomical features such as AChA dilation markedly influence the risk of recurrent hemorrhage in hMMD. The confirmation that female sex and bilateral lesions adversely affect outcomes contributes important nuance to patient risk stratification. Notably, EDAS as an indirect revascularization strategy appears to confer significant benefit in reducing rebleeding and improving prognosis, corroborating prior smaller studies but at an unprecedented scale.
Mechanistically, the improvement with EDAS can be attributed to enhanced collateral circulation reducing stress on fragile moyamoya vessels and abnormal collaterals like AChA, thereby lowering hemorrhagic risk. Since direct revascularization techniques carry technical challenges and risk, especially in hemorrhagic presentations, EDAS offers a safer and effective alternative.
Caveats include the retrospective nature and unmeasured confounders such as medical management variations and hemorrhage severity. Nevertheless, this work sets the stage for prospective, multicenter randomized trials to definitively establish treatment guidelines. Future studies could also explore the utility of vessel imaging biomarkers like AChA dilation in guiding individualized interventions.
Conclusion
In this comprehensive cohort of hemorrhagic Moyamoya patients, anterior choroidal artery dilation is a critical predictor of rebleeding, while female sex and bilateral lesions signify poor functional outcomes. Indirect revascularization with EDAS significantly reduces rebleeding incidence and improves prognosis compared to conservative management. These findings highlight the importance of vascular imaging evaluation and support EDAS as an effective therapeutic option to alter the natural history of hMMD. Prospective studies are warranted to confirm these observations and refine patient selection criteria for surgical intervention.
Funding and ClinicalTrials.gov
The original study did not report specific funding sources or clinical trial registration information.
References
Chen C, Gao G, Wang H, et al. Natural Course and Clinical Outcomes of Patients With Hemorrhagic Moyamoya Disease: A Large Cohort Study. Neurology. 2026;107(7):e218493. doi:10.1212/WNL.0000000000002184
Suzuki J, Takaku A. Cerebrovascular “moyamoya” disease: disease showing abnormal net-like vessels in base of brain. Arch Neurol. 1969;20(3):288-299.
Kuroda S, Houkin K. Moyamoya disease: current concepts and future perspectives. Lancet Neurol. 2008;7(11):1056-1066.
Miyatake S, Houkin K, Karasawa J, et al. Outcomes of surgical revascularization for hemorrhagic moyamoya disease: a single-center experience. J Neurosurg. 2021;134(4):1156-1162.
Kim SK, Kim JE, Phi JH, et al. Risk factors for rebleeding after hemorrhagic moyamoya disease surgery. J Neurosurg. 2017;126(3):720-727.


