

Highlight
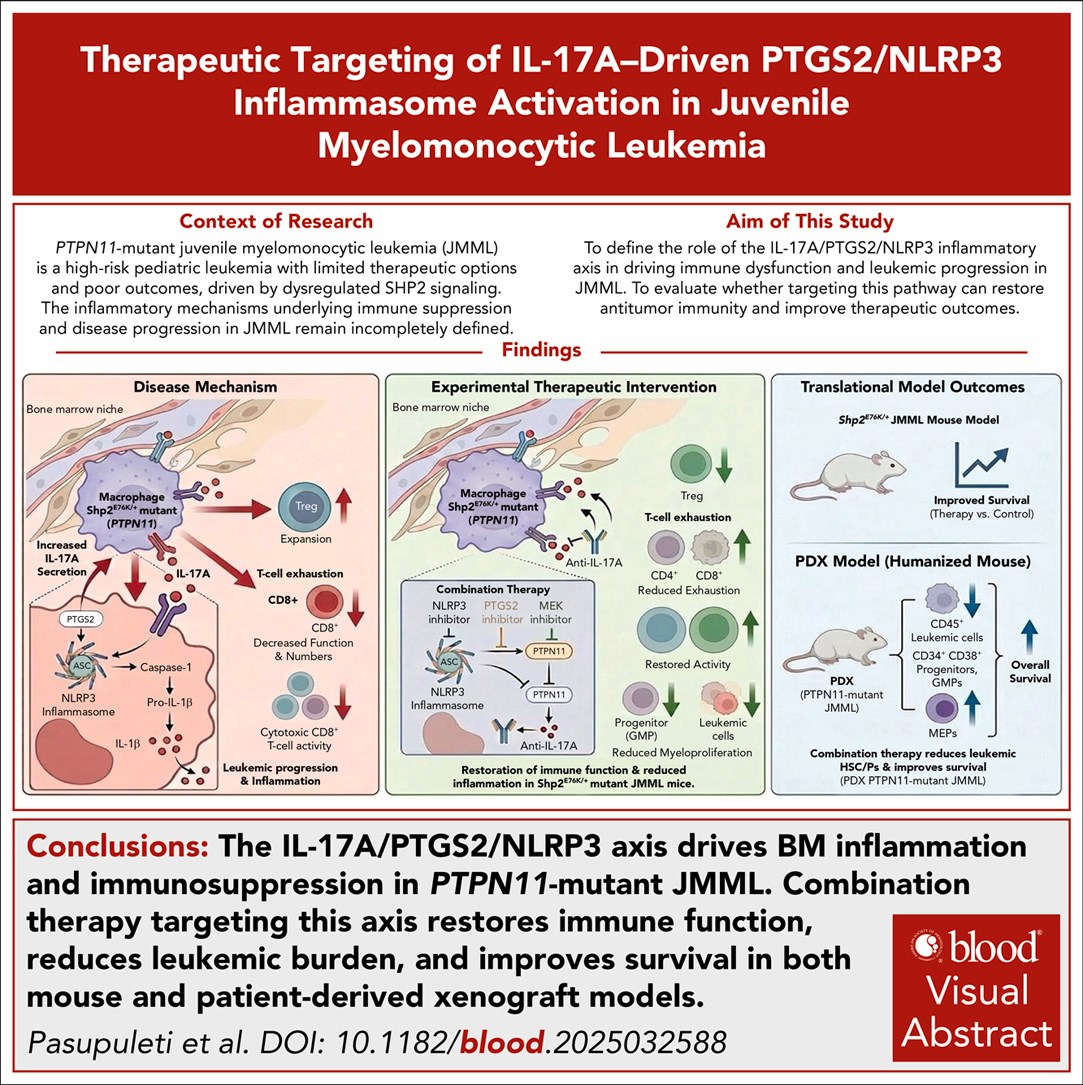
• Identification of an IL-17A-driven PTGS2/NLRP3 inflammasome axis as a central mediator of inflammation and immune evasion in PTPN11-mutant JMML.
• Demonstration that IL-17A neutralization, combined NLRP3 and PTGS2 inhibition, and MEK blockade restores T-cell cytotoxicity and reduces leukemic progenitor expansion.
• Primary JMML patient samples and xenograft models validate the translational relevance of targeting inflammatory pathways alongside MAPK inhibition.
• Combined anti-inflammatory and targeted therapy significantly prolongs survival and normalizes hematopoietic progenitor populations in preclinical JMML models.
Study Background
Juvenile myelomonocytic leukemia (JMML) is a rare, aggressive myelodysplastic/myeloproliferative neoplasm primarily affecting young children. It is characterized by clonal proliferation of myelomonocytic cells and profound hematopoietic dysregulation. Hematopoietic stem cell transplantation (HSCT) is currently the only curative treatment; however, outcomes remain poor for patients harboring mutations in PTPN11, which encodes the SHP2 phosphatase—a crucial regulator in the RAS/MAPK signaling pathway. Limited targeted therapies have been effective due to the complex inflammatory and immunosuppressive bone marrow microenvironment that fosters leukemic progression and inhibits normal hematopoiesis. Thus, there is an urgent unmet need to elucidate the pathogenic mechanisms underlying PTPN11-mutant JMML and to develop rational combinatorial strategies that can improve patient outcomes.
Study Design
This investigation employed a murine model harboring the Shp2E76K/+ mutation replicating PTPN11-mutant JMML to dissect the inflammatory and immune pathways contributing to disease progression. Multiparameter flow cytometry and molecular analyses characterized immune cell subset alterations, signaling pathway activation, and inflammasome components in bone marrow. Therapeutic interventions included IL-17A neutralizing antibodies, pharmacological inhibitors targeting NLRP3 inflammasome and PTGS2 (prostaglandin-endoperoxide synthase 2), as well as MEK inhibitors targeting downstream MAPK signaling. Functional assays evaluated T-cell cytotoxicity, leukemic progenitor colony formation, and survival outcomes. Human relevance was investigated through ex vivo treatment of primary JMML patient samples and patient-derived xenograft (PDX) models with combinatorial NLRP3/PTGS2 inhibition and MEK blockade.
Key Findings
Immune Dysregulation in Shp2E76K/+ Mice: The PTPN11-mutant mouse model showed pronounced expansion of regulatory T cells (Tregs) and increased T-cell exhaustion markers accompanied by diminished frequencies of CD4+ and CD8+ T cells with impaired cytotoxic function. This immune dysregulation correlated with an inflammatory marrow milieu sustaining leukemic proliferation.
IL-17A/PTGS2/NLRP3 Inflammasome Axis Activation: Mutant macrophages upregulated IL-17A secretion, which in turn activated the NLRP3 inflammasome pathway, indicated by increased caspase-1 cleavage and IL-1β maturation. This cascade induced PTGS2 expression, amplifying bone marrow inflammation and fostering immune suppression.
Therapeutic Impact of Targeting IL-17A and Inflammasome Components: IL-17A neutralization markedly decreased inflammasome activation and inflammatory cytokine production. More notably, combined inhibition of NLRP3 and PTGS2 restored CD8+ and CD4+ T-cell cytotoxicity, reduced systemic and marrow inflammation, reversed the myeloproliferative phenotype, and significantly prolonged survival in Shp2E76K/+ mice.
Translational Relevance in Human JMML: Ex vivo treatments of primary JMML patient samples with dual NLRP3/PTGS2 inhibitors plus MEK blockade substantially diminished leukemic progenitor colony formation. PDX models treated with this combination showed reduced human CD45+ leukemic engraftment, depletion of leukemic CD34+CD38+ progenitors and granulocyte-macrophage progenitors, and partial restoration of normal megakaryocyte-erythroid progenitors. This combinatorial regimen resulted in significantly improved overall survival in PDX models.
Expert Commentary
This study elegantly identifies a pathological IL-17A-driven inflammatory cascade contributing to immune evasion and leukemic proliferation in PTPN11-mutant JMML. The integration of genetic models, primary patient samples, and humanized xenografts strengthens the translational potential of inflammasome and PTGS2 as therapeutic targets. The authors provide compelling evidence that inflammation-directed therapies combined with MEK inhibition can overcome leukemic immune suppression and malignant expansion, potentially transforming clinical strategies for this high-risk JMML subset.
However, limitations include the need for further validation in clinical trials to assess safety, efficacy, and optimal combinatorial dosing in pediatric patients. Additional research is warranted to understand long-term impacts on normal hematopoiesis and immune reconstitution post-therapy.
Conclusion
This comprehensive work establishes that the IL-17A/PTGS2/NLRP3 inflammasome signaling axis is a critical driver of immune dysfunction and myeloid proliferation in PTPN11-mutant JMML. Targeting this inflammatory pathway alongside MEK inhibition offers a promising therapeutic approach to enhance antileukemic immunity, reduce leukemic burden, and extend survival. These findings support advancing combinatorial anti-inflammatory and targeted therapies into clinical evaluation to improve outcomes in children afflicted with this aggressive form of leukemia.
Funding and ClinicalTrials.gov
The study was funded by relevant research grants as acknowledged by the original publication. No clinical trials have yet been registered for this combinatorial approach; forthcoming clinical studies are necessary to establish feasibility and efficacy in JMML patients.
References
Pasupuleti SK, Ramdas B, Ram Padam KS, Kanumuri R, Palam LR, Kumar R, Ho TC, Lee AG, Clapp WD, Qu CK, Stieglitz E, Yang K, Kapur R. Therapeutic targeting of IL-17A-driven PTGS2/NLRP3 inflammasome activation in juvenile myelomonocytic leukemia. Blood. 2026 Sep 17;148(12):1605-1620. PMID: 42233403.
Further contextual references include:
- Flotho C, et al. Juvenile myelomonocytic leukemia: biology, clinical features and treatment approaches. Expert Rev Hematol. 2020;13(3):279-292.
- Stieglitz E, et al. Genomic alterations in juvenile myelomonocytic leukemia. Blood. 2015;126(8):893-902.
- Dinarello CA. Immunological and inflammatory functions of the interleukin-1 family. Annu Rev Immunol. 2009;27:519-550.
- Chen GY, Nunez G. Inflammasomes in intestinal inflammation and cancer. Gastroenterology. 2011;141(6):1986-1999.
- Tarapore RS, et al. Targeting the NLRP3 inflammasome and COX-2 in cancer. Trends Mol Med. 2022;28(7):558-571.


