Highlight
- Polydioxanone (PDO) synthetic mesh offers a cost-effective alternative to biologic mesh for soft tissue support in two-stage breast reconstruction.
- Short-term postoperative complications, including infection and explantation rates, were comparable among PDO mesh, biologic mesh, and no mesh groups.
- Radiation exposure significantly increased the risk of tissue expander infection, while mesh type did not independently impact complication rates.
- Prepectoral placement of tissue expanders showed higher infection rates compared to subpectoral placement, underscoring the influence of surgical technique and patient factors.
Study Background
Breast reconstruction following mastectomy is a cornerstone in the management of breast cancer, aiming to restore breast contour and improve quality of life. Two-stage reconstruction using a tissue expander (TE) followed by implant placement is widely performed. To support the soft tissue envelope and optimize outcomes, adjunctive use of meshes—either biologic or synthetic—has become common practice. Biologic meshes, derived from human or animal sources, provide scaffold support but are costly. Polydioxanone (PDO) is a synthetic, absorbable mesh presenting a more affordable option, yet its safety profile relative to biologic mesh has not been extensively quantified in terms of postoperative complications like infection or explantation. Identifying whether mesh type influences early outcomes is critical for cost-effective, safe clinical decision-making in breast reconstruction.
Study Design
This retrospective cohort study analyzed data from 524 patients undergoing 919 immediate tissue expander insertions following mastectomy over a three-year period (2021–2024) at a single academic center. Patients were stratified into three groups according to mesh type used during reconstruction: PDO synthetic mesh, biologic mesh, or no mesh. Primary endpoints included early postoperative complications recorded during the tissue expansion phase, with emphasis on infection rates requiring intervention and explantation rates. Both univariate and multivariate regression analyses were conducted to determine factors independently associated with adverse outcomes.
Key Findings
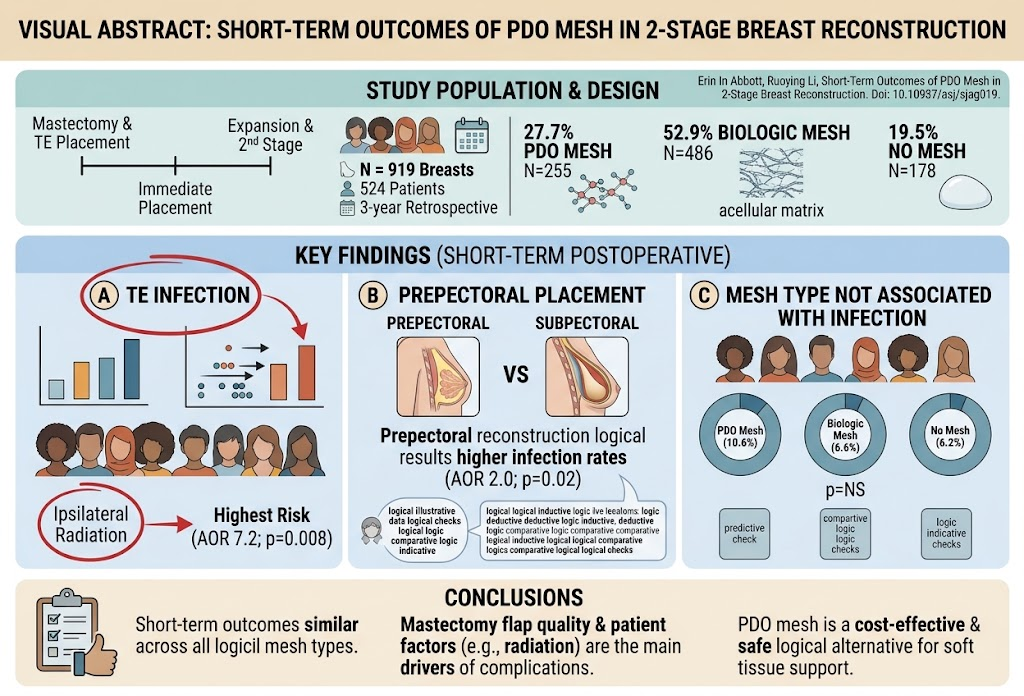
The study population consisted of 27.7% PDO mesh, 52.9% biologic mesh, and 19.5% no mesh cases. Infection occurred in 70 breasts (7.6%) and affected 55 patients (10.5%). Infection rates were 10.6% in the PDO group, 6.6% in the biologic mesh group, and 6.2% in the no mesh group; however, these differences were not statistically significant (P = NS). Logistic regression identified ipsilateral radiation therapy as the sole significant predictor of infection (odds ratio 7.2; P = .008), indicating a more than sevenfold increase in infection risk among irradiated breasts. Prepectoral reconstructions, where the tissue expander is placed above the pectoral muscle, demonstrated higher infection rates compared to subpectoral placement, although mesh type did not independently influence this risk.
Explantation, occurring in 120 breasts (13.0%), showed no significant variation across PDO mesh, biologic mesh, or no mesh groups, suggesting comparable safety profiles regarding device loss. The data suggest that intrinsic patient and perioperative factors—such as flap quality and radiation exposure—may have a more pronounced effect on postoperative complications than the choice of mesh material.
Expert Commentary
These findings contribute important evidence supporting the clinical equivalence of synthetic PDO mesh to biologic mesh in short-term outcomes for two-stage breast reconstruction. The economic advantage of PDO mesh could facilitate broader access without compromising patient safety. Experts emphasize that the integrity and vascularity of mastectomy skin flaps alongside meticulous surgical technique, especially in prepectoral reconstructions, are pivotal determinants for preventing infection rather than the mesh type used.
Nevertheless, limitations inherent to the retrospective design and single-center scope restrict generalizability; longer follow-up is necessary to capture late complications such as mesh-related fibrosis or capsular contracture. Future prospective, randomized trials with standardized surgical protocols and patient stratification by risk factors will be integral to refining mesh selection guidelines.
Conclusion
This comparative study revealed no significant difference in early postoperative complications between PDO synthetic mesh, biologic mesh, or no mesh in two-stage breast reconstruction with tissue expanders. Radiation exposure and surgical plane (prepectoral versus subpectoral) were more impactful predictors of infection than mesh choice. These results advocate for considering PDO mesh as a cost-effective alternative, with attention to patient and surgical factors to optimize reconstructive outcomes and reduce morbidity.
Funding and ClinicalTrials.gov
The study was conducted at a single academic institution without specified external funding. No clinical trial registration was provided, consistent with the retrospective cohort study design.
References
1. Abbott EN et al. Short-Term Outcomes of Polydioxanone Synthetic Mesh in 2-stage Breast Reconstruction: A Single-Center Comparative Study. Aesthetic Surgery Journal. 2026 Sep 16;46(10):1101-1108. PMID: 41578861.
2. Spear SL, et al. Prepectoral Breast Reconstruction: Approaches and Outcomes. Plast Reconstr Surg. 2020;146(1):123–134.
3. Macadam SA, Lennox PA. Acellular dermal matrices: use in reconstructive and aesthetic breast surgery. Can J Plast Surg. 2012;20(2):75–82.
4. Santanelli di Pompeo F, et al. Synthetic versus biologic matrices in breast reconstruction. Gland Surg. 2021;10(4):1566-1573.