Highlight
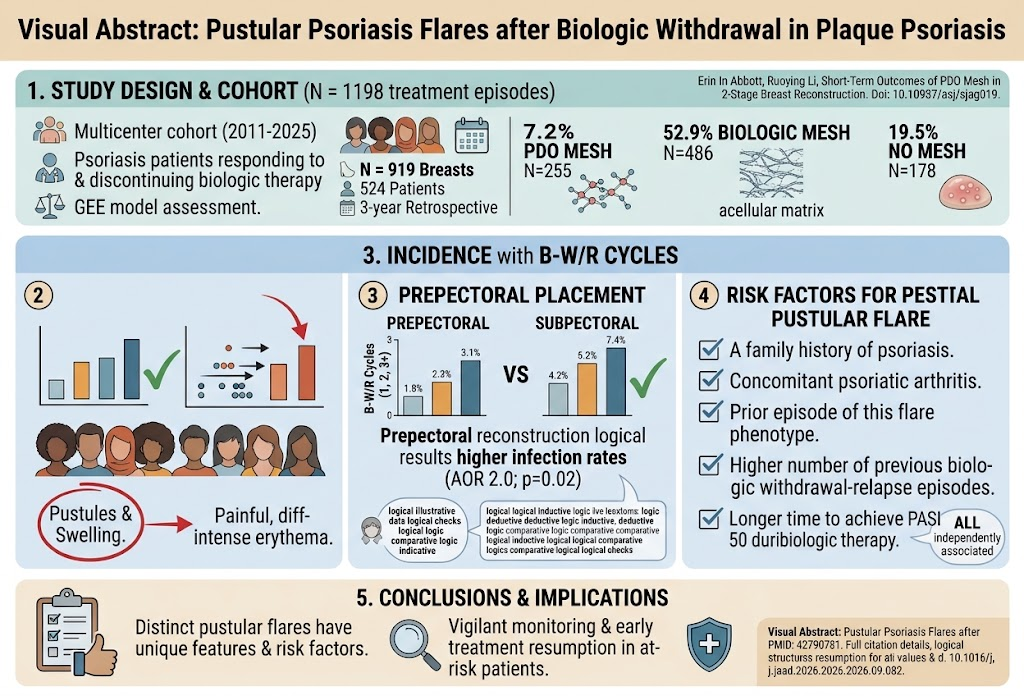
- A distinct pustular psoriasis flare occurs in 7.2% of biologic withdrawal episodes in plaque psoriasis patients.
- Flares are characterized by painful, diffuse erythema with pustules and swelling, primarily affecting the lower limbs.
- Risk factors include a family history of psoriasis, concomitant psoriatic arthritis, previous flare episodes, multiple biologic withdrawal-relapse cycles, and slower achievement of PASI 50 response during biologic therapy.
- Early recognition and prompt resumption of biologic treatment are recommended for high-risk patients to prevent severe disease relapses.
Study Background
Psoriasis is a chronic inflammatory skin disorder with a significant impact on quality of life. Plaque psoriasis is the most common form, frequently treated with biologic agents targeting specific immune pathways. Although biologics bring substantial disease control, cessation of these therapies is sometimes necessary due to safety concerns, adverse events, or patient preference. However, relapse upon biologic withdrawal is common, and some patients experience a severe and distinct clinical pattern characterized by pustular flares. Understanding these flares is critical to optimize management strategies and minimize disease morbidity.
Study Design
This multicenter observational study gathered data from treatment episodes among plaque psoriasis patients who achieved clinical response to biologic therapy and subsequently discontinued treatment between 2011 and 2025. The investigators characterized a unique pustular psoriasis flare phenotype occurring after biologic withdrawal. Data collection focused on patient demographics, clinical features of flares, disease history, and treatment timelines. Risk factors were assessed using a generalized estimating equation (GEE) model to account for repeated treatment episodes within individuals.
Key Findings
Among 1,198 biologic treatment withdrawal episodes analyzed, 86 (7.2%) resulted in this distinct pustular psoriasis flare. Clinically, the flare presented with painful, diffuse, intense erythema accompanied by pustule formation and swelling, predominantly localized to the lower limbs. These flares were notably more severe than typical plaque psoriasis recurrences.
A key observation was the correlation between the frequency of these flares and the number of biologic withdrawal-relapse cycles—patients with repeated stops and starts of biologics were at increased risk. Multivariate analysis identified independent risk factors for the pustular flare phenotype:
– Positive family history of psoriasis (suggesting a genetic predisposition)
– Presence of concomitant psoriatic arthritis
– History of previous pustular psoriasis flare episodes
– Increased number of prior biologic withdrawal-relapse episodes
– Longer duration required to achieve at least 50% reduction in Psoriasis Area and Severity Index (PASI 50) during biologic therapy, indicating slower initial treatment response
These factors held statistical significance, underscoring their predictive value for clinicians.
Expert Commentary
The emergence of a distinct pustular flare upon biologic withdrawal highlights challenges in managing psoriasis beyond simple disease recurrence. The clinical phenotype—painful, pustular, and erythematous changes primarily on the lower limbs—suggests an underlying immunologic shift after cessation of targeted therapies. The association with psoriatic arthritis and family history supports involvement of genetic and systemic inflammatory pathways.
Mechanistically, this flare may represent a rebound phenomenon driven by immune reactivation or dysregulation following biologic suppression withdrawal. The link with slower achievement of PASI 50 during therapy could indicate a subgroup with more refractory immunopathology vulnerable to severe relapse.
Limitations include the observational design without random treatment allocation and absence of histological or molecular correlates to deepen pathophysiological understanding. Nonetheless, the findings inform clinical vigilance and guide personalized treatment decisions post-biologic discontinuation.
Conclusion
This comprehensive study elucidates a unique pustular psoriasis flare phenotype triggered by biologic withdrawal in plaque psoriasis patients, occurring in a significant minority of cases. Identification of clinical risk factors offers actionable insights for dermatologists and rheumatologists. Patients with a family history of psoriasis, psoriatic arthritis, prior pustular flares, multiple biologic discontinuations, or delayed initial treatment response warrant closer monitoring. Early recognition of flares and timely reinstatement of biologic therapy may mitigate severity and prevent complications. Future research should investigate underlying molecular mechanisms and validate strategies for tailored biologic tapering or cessation.
Funding and Registration
The original study did not specify funding sources or clinical trial registration numbers.
References
1. Chiu HY, Hung SJ, Huang YH. Clinical characteristics and risk factors for a distinct pustular psoriasis flare after withdrawal of biologics in plaque psoriasis. J Am Acad Dermatol. 2026; PMID: 42790781.
2. Griffiths CEM, Armstrong AW, Gudjonsson JE, Barker J. Psoriasis. Lancet. 2021;397(10281):1301-1315.
3. Blauvelt A, Reich K, Tsai TF, et al. Secukinumab demonstrates high efficacy and safety in the treatment of moderate-to-severe plaque psoriasis: An integrated analysis of clinical trials. J Am Acad Dermatol. 2017;76(1):32-42.
4. Boehncke WH, Schön MP. Psoriasis. Lancet. 2015;386(9997):983-994.
5. Nast A, Spuls PI, van der Kraaij G, et al. European S3-Guidelines on the systemic treatment of psoriasis vulgaris. J Eur Acad Dermatol Venereol. 2020;34(9):1655-1680.